
Suicide Statistics UK: 2026 Facts, Data & Key Insights
Suicide statistics UK
Understanding the latest figures, the differences between them, and the people behind every number.

Suicides registered in England and Wales in 2025.
England and Wales · including non-residentsPublished 13 October 2026.
Registered suicides per 100,000 people, after accounting for population age structure.
England and Wales · ages 10+ · 2025A population rate, not individual risk.
Median time from death to registration among the deaths registered in 2025.
England and Wales · 2025 registrationsAn administrative delay, not a healthcare wait.
What do suicide statistics measure?
Suicide statistics describe deaths and experiences across populations. They can help identify patterns and inform prevention, but they do not predict what will happen to an individual. Behind every number are people, families and communities affected by loss.
Registration year
The year a death enters the official register. The death itself may have occurred earlier, because an investigation or inquest can take time.
Occurrence year
The year the person died. Recent occurrence totals can be incomplete while investigations are still in progress, and later releases can revise them.
Count
The number registered under the publication’s definition. Larger populations can have more deaths without having a higher population rate.
Rate
A rate relates deaths to population size. Age-standardised rates also account for different age structures; age-specific rates describe one age group.
A count, an age-standardised rate and a survey response are different measures. They should retain their own denominators when quoted. A death-registration trend cannot be substituted for a trend in suicidal thoughts or attempts.
Age-standardised, age-specific and crude rates
A crude rate divides the recorded deaths by the population. An age-standardised rate applies a common age structure, making comparisons less affected by one population being older than another. An age-specific rate uses the population in a particular age band.
The sex, trend and English-region charts below use age-standardised rates. The age chart uses age-specific rates. They are labelled separately and should not be treated as interchangeable measures.
The ONS definition includes deaths classified as intentional self-harm from age 10 and deaths of undetermined intent from age 15. The age-standardised rates shown here use the population aged 10 and over and the 2013 European Standard Population.
Deaths registered, and deaths occurring.
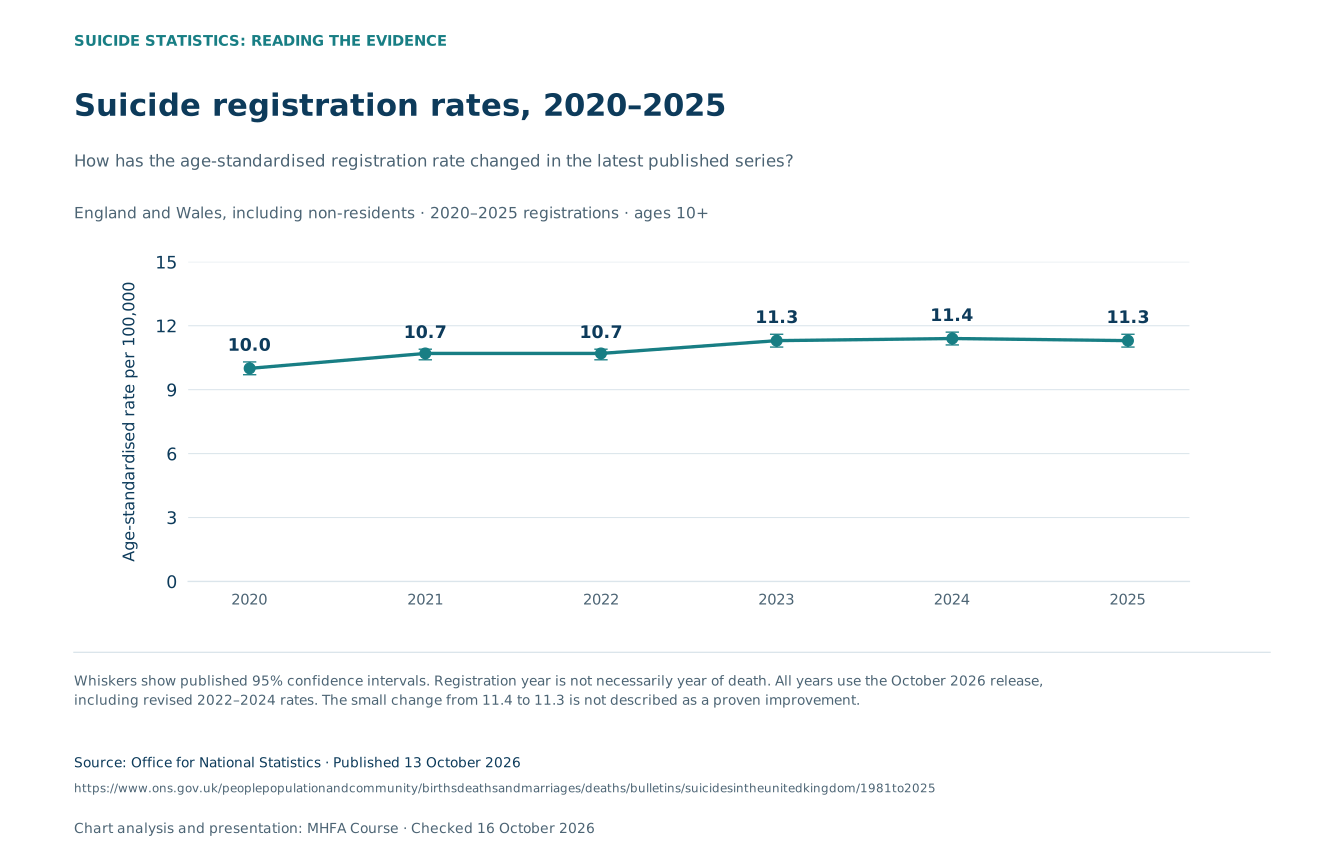
In England and Wales, 6,162 suicides were registered in 2025. The age-standardised rate was 11.3 per 100,000, similar to 11.4 in 2024.
The registration chart uses the latest published series, with its confidence intervals. Small movements in a rate should be interpreted alongside this uncertainty, rather than automatically described as a meaningful rise or fall.
The median time from death to registration was 192 days among the deaths registered in 2025. This helps explain why registration year and occurrence year can differ. It is not a waiting time for mental health care.
Suicide registration rates, 2020–2025
How has the age-standardised registration rate changed in the latest published series?
| Group / measure | per 100,000 people aged 10+ | 95% interval |
|---|---|---|
| 2020 | 10 | 9.7–10.3 |
| 2021 | 10.7 | 10.4–10.9 |
| 2022 | 10.7 | 10.4–10.9 |
| 2023 | 11.3 | 11–11.6 |
| 2024 | 11.4 | 11.1–11.7 |
| 2025 | 11.3 | 11–11.6 |
Whiskers show published 95% confidence intervals. Registration year is not necessarily year of death. All years use the October 2026 release, including revised 2022–2024 rates. The small change from 11.4 to 11.3 is not described as a proven improvement.
Occurrence rates with equal registration follow-up
Deaths occurring in each year, registered within 18 months after the end of that year.
| Group / measure | per 100,000 people aged 10+ |
|---|---|
| 2019 | 10.6 |
| 2020 | 10.6 |
| 2021 | 10.5 |
| 2022 | 10.7 |
| 2023 | 10.7 |
| 2024 | 10.4 |
The 2024 point includes provisional January–June 2026 registrations. Equal follow-up improves comparability but does not capture every eventual registration. No confidence limits are supplied for this series.
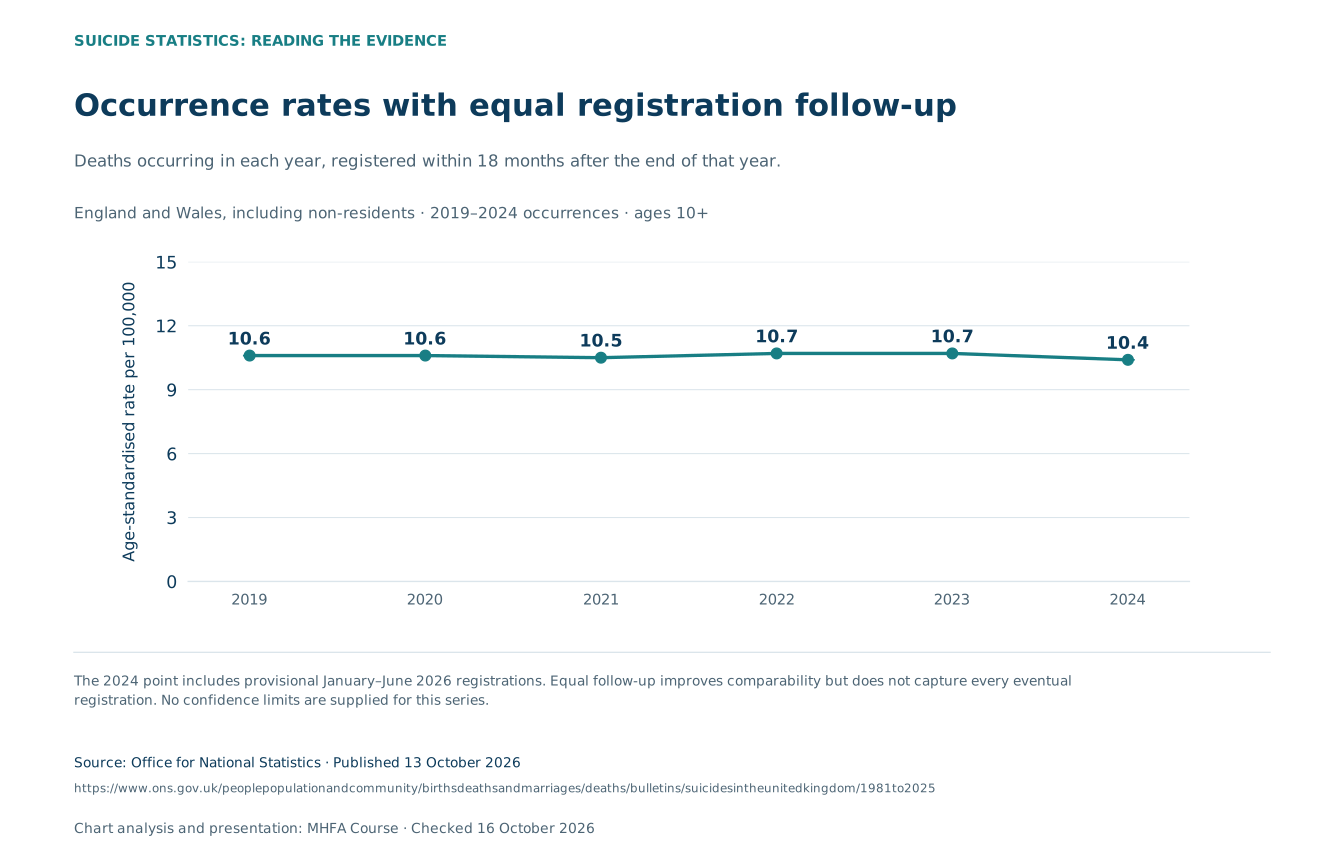
The occurrence chart answers a different question: when did the deaths happen? Using a consistent follow-up window helps reduce the distortion that would arise from giving older years much more time to accumulate registrations. It still does not guarantee that every death from each occurrence year has been registered.
ONS describes the occurrence-based trend as fairly stable since 2018. Recent occurrence estimates and the registration series should be read together, with their different clocks clearly identified.
Why can an earlier year’s figures change?
Deaths can be registered after investigations are complete. Later publications can also incorporate revisions to population estimates or other source data. This guide uses the latest available version of each selected series, rather than mixing values copied from different releases.
Revisions are part of interpreting official statistics. The downloadable data preserve the source release and the measure used, so a later update can be compared on the same basis.
What a registration trend can tell us
Consistent definitions and the latest published version of a series help show how registration rates have changed. They do not establish the reasons for a change. Registration delays, uncertainty and changes in the population all matter when reading a year-to-year movement.
It is particularly important not to compare a UK count in one year with an England and Wales count in another and describe the difference as an increase or decrease.
How rates differ by sex and age.
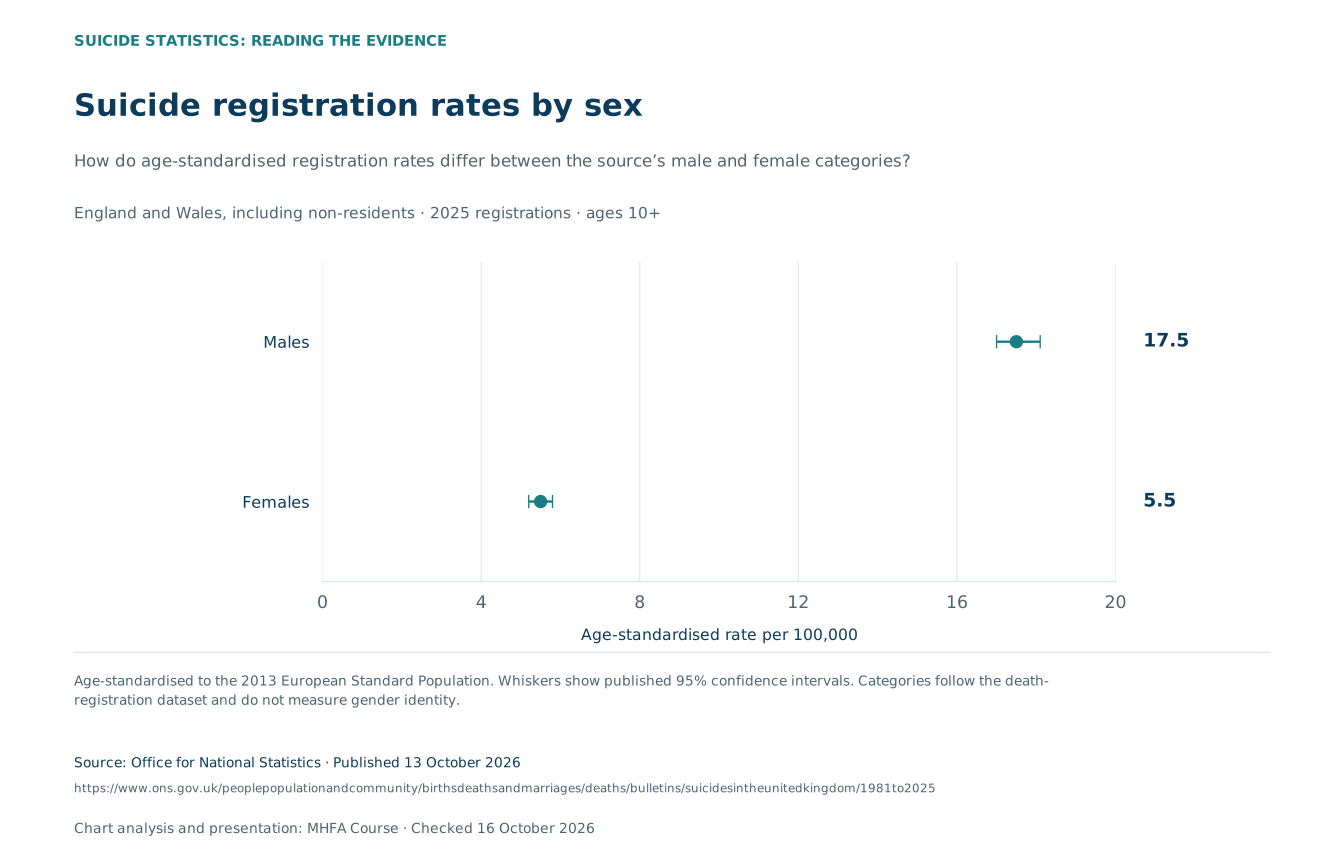
The 2025 age-standardised registration rate was 17.5 per 100,000 males and 5.5 per 100,000 females in England and Wales. Males accounted for around three-quarters of registered suicides.
The chart uses the source’s male and female categories. Death-registration statistics do not by themselves establish the biological, social or service-related reasons for the difference.
Suicide registration rates by sex
How do age-standardised registration rates differ between the source’s male and female categories?
| Group / measure | per 100,000 people aged 10+ | 95% interval |
|---|---|---|
| Males | 17.5 | 17–18.1 |
| Females | 5.5 | 5.2–5.8 |
Age-standardised to the 2013 European Standard Population. Whiskers show published 95% confidence intervals. Categories follow the death-registration dataset and do not measure gender identity.
Age-specific rates answer a different question
The following chart uses published broad age groups. These rates relate deaths to the population within each age band; they are not age-standardised comparisons between otherwise equivalent groups.
Suicide registration rates by age
Registered deaths relative to the population within each published broad age group.
| Group / measure | per 100,000 people in the age group | 95% interval |
|---|---|---|
| 10 to 24 | 5.1 | 4.7–5.6 |
| 25 to 44 | 12.5 | 12–13 |
| 45 to 64 | 15.2 | 14.6–15.8 |
| 65 to 74 | 9.7 | 8.9–10.5 |
| 75 and over | 9.3 | 8.5–10.1 |
These are age-specific, not age-standardised, rates. Whiskers show published 95% confidence intervals. Broad groups can conceal differences within them; a narrower age band can have a different highest rate.
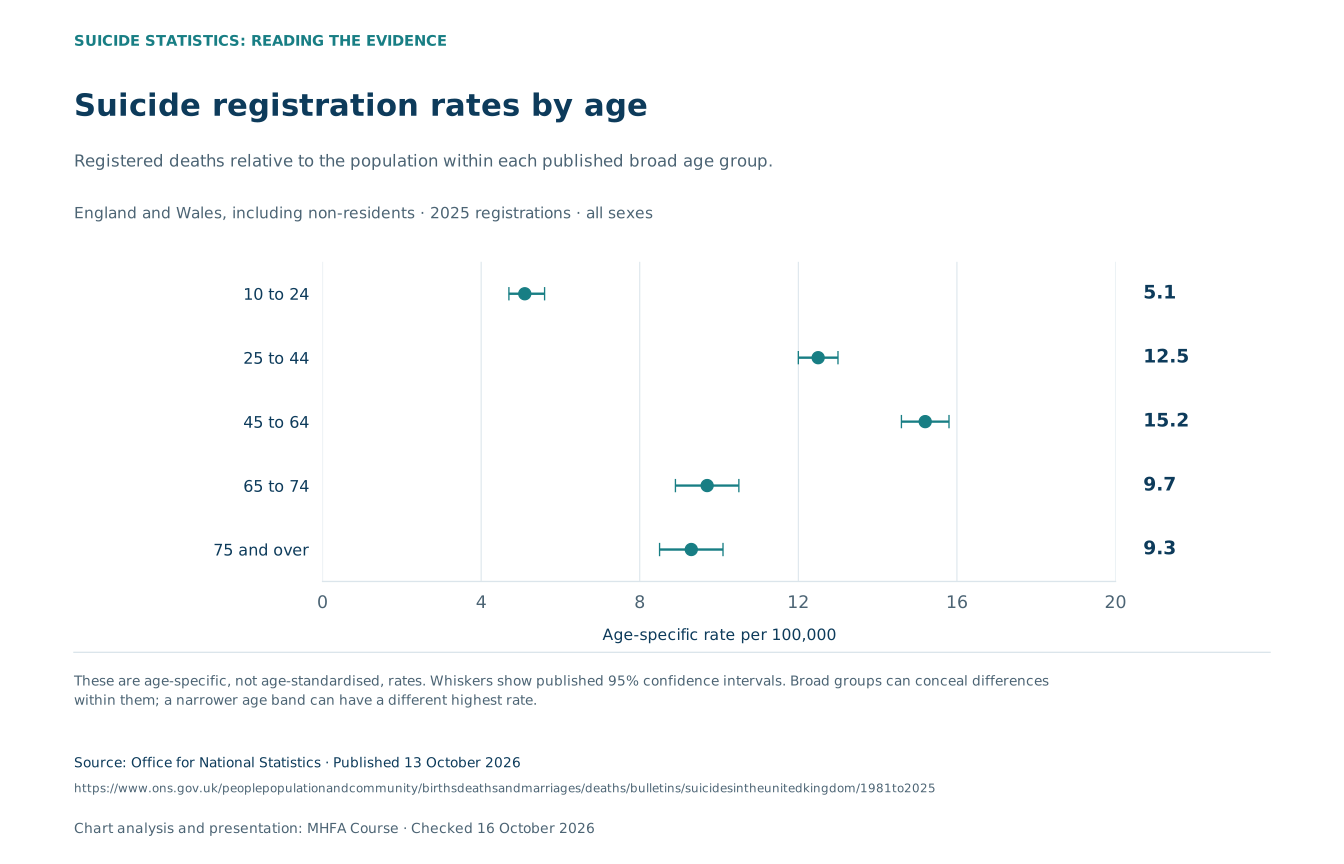
More detailed age bands in the same publication show that ages 50–54 had the highest all-person age-specific registration rate in 2025, at 17.4 per 100,000. Males aged 50–54 had the highest male rate, at 28.0. The highest female rate was at ages 45–49, at 7.7.
Those detailed bands are not the same as the broader groups drawn in the chart. Keeping the band width and sex definition attached to a quoted rate avoids an apparent contradiction between two valid summaries.
These are population patterns, not an assessment of a particular person’s safety. A lower rate in a group does not make an individual’s suicidal thoughts less serious. Support should respond to the person’s current circumstances, rather than to a statistical category.
Regional differences need context.
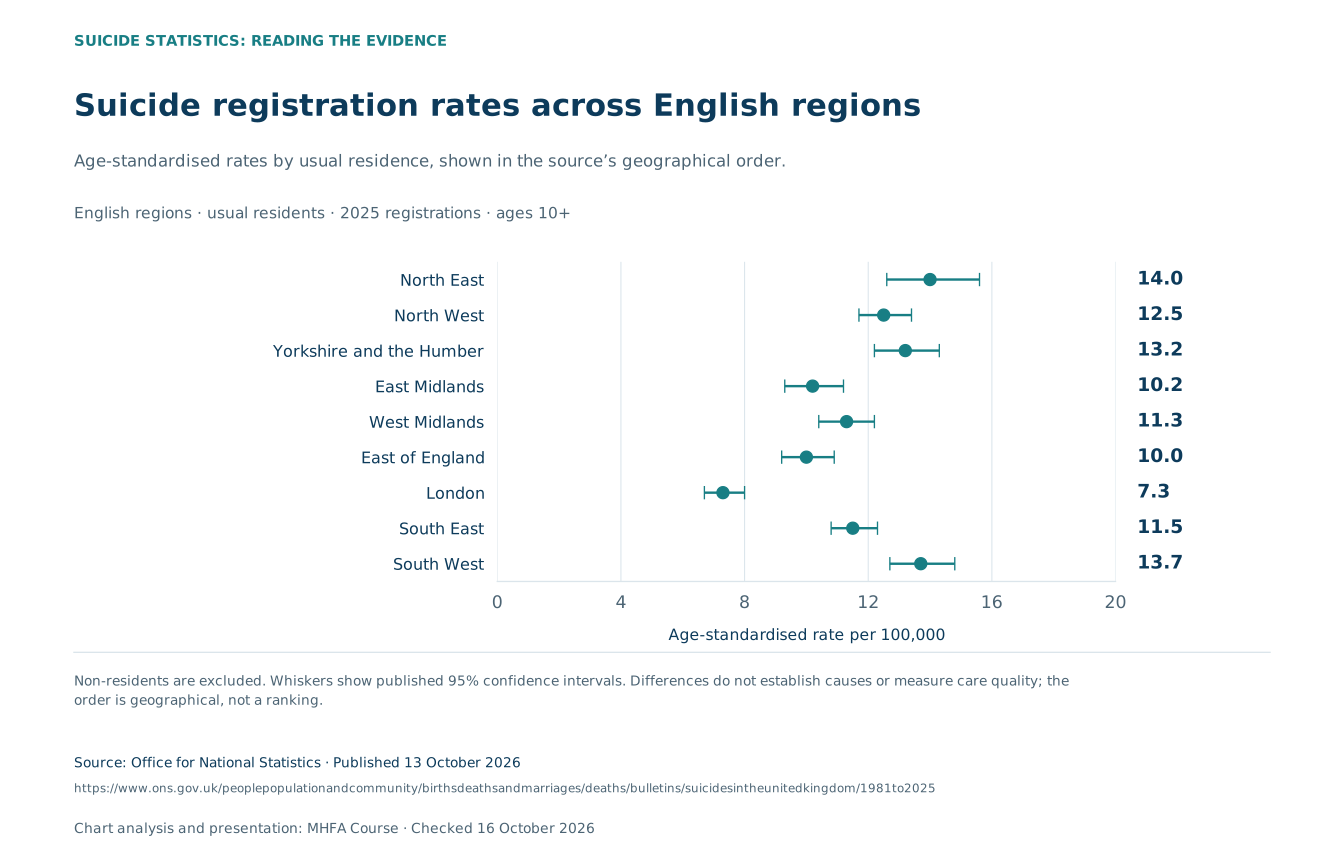
Among English regions, the North East had the highest age-standardised suicide registration rate in 2025, at 14.0 per 100,000. London had the lowest, at 7.3.
The confidence intervals show the uncertainty around each rate. The chart is a descriptive comparison, not proof that every neighbouring pair of regions differs meaningfully.
Suicide registration rates across English regions
Age-standardised rates by usual residence, shown in the source’s geographical order.
| Group / measure | per 100,000 people aged 10+ | 95% interval |
|---|---|---|
| North East | 14 | 12.6–15.6 |
| North West | 12.5 | 11.7–13.4 |
| Yorkshire and the Humber | 13.2 | 12.2–14.3 |
| East Midlands | 10.2 | 9.3–11.2 |
| West Midlands | 11.3 | 10.4–12.2 |
| East of England | 10 | 9.2–10.9 |
| London | 7.3 | 6.7–8 |
| South East | 11.5 | 10.8–12.3 |
| South West | 13.7 | 12.7–14.8 |
Non-residents are excluded. Whiskers show published 95% confidence intervals. Differences do not establish causes or measure care quality; the order is geographical, not a ranking.
England, Wales and the wider UK
England’s age-standardised rate was 11.1 per 100,000 in 2025; Wales’s was 14.3, under the ONS publication’s definitions. The separate UK total of 7,147 registrations in 2024 comes from the House of Commons Library’s January 2026 briefing.
The latest final annual publications available on 16 October 2026 reported 704 probable suicides registered in Scotland in 2024 and 290 suicides registered in Northern Ireland in 2024. These were published on 16 September 2025 and 20 November 2025, respectively. Scotland’s 2025 edition was scheduled for 3 November 2026 and was not yet available.
The Commons UK total is reproduced by combining the England- and Wales-resident counts with the Scotland and Northern Ireland counts. The England and Wales headline also includes non-residents, so adding that headline to the Scotland and Northern Ireland counts would not reproduce the same UK total.
Country releases differ in timing and rate definitions. Scotland’s forthcoming edition also changes its age definition and revises the historical series. This guide does not construct a country ranking from unmatched rates.
Regional figures can inform local prevention planning, but they do not explain why an individual died. Economic hardship, isolation, physical and mental ill health, abuse and difficulties accessing support can be relevant to prevention without any one of them being established as the cause of a region’s rate.
Local services and communities can use the evidence alongside information about need and access to care. Differences between areas should not be treated as a judgement on the people who live there or a ranking of the quality of all local support.
What surveys tell us about suicidal thoughts.
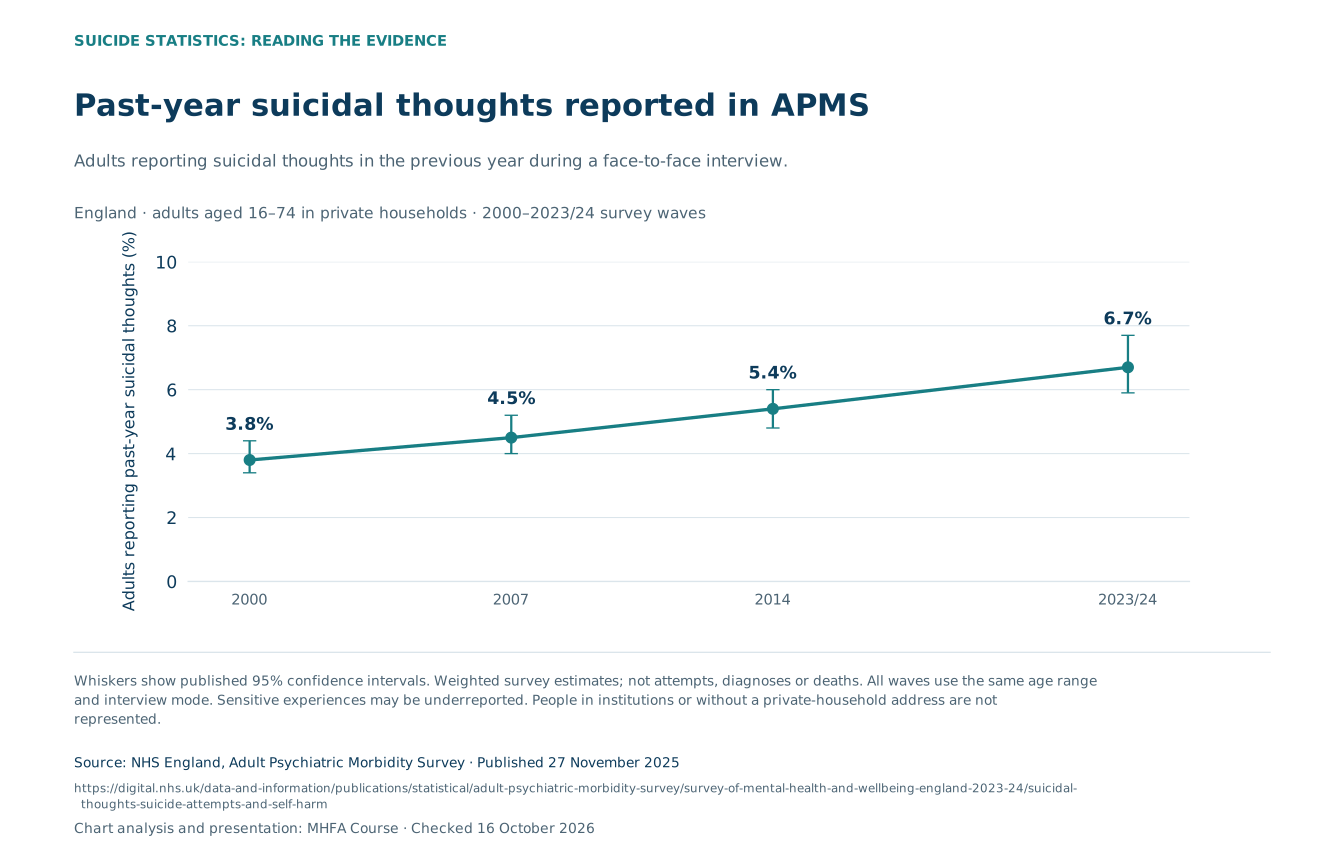
In the Adult Psychiatric Morbidity Survey (APMS) 2023/24, 6.7% of adults aged 16–74 in England reported suicidal thoughts in the previous year during the face-to-face interview.
This is a household-survey estimate, not a count of suicide deaths or a UK-wide estimate. The trend keeps the age range, question and interview mode consistent.
Past-year suicidal thoughts reported in APMS
Adults reporting suicidal thoughts in the previous year during a face-to-face interview.
| Group / measure | percent | 95% interval |
|---|---|---|
| 2000 | 3.8% | 3.4–4.4% |
| 2007 | 4.5% | 4–5.2% |
| 2014 | 5.4% | 4.8–6% |
| 2023/24 | 6.7% | 5.9–7.7% |
Whiskers show published 95% confidence intervals. Weighted survey estimates; not attempts, diagnoses or deaths. All waves use the same age range and interview mode. Sensitive experiences may be underreported. People in institutions or without a private-household address are not represented.
Past-year and lifetime experiences use different time windows. The 25.2% lifetime figure for adults aged 16 and over in APMS 2023/24 combines positive reports in either the face-to-face or self-completion interview. It has a different age base and interview-mode definition from the 16–74 face-to-face past-year series. Neither percentage is an estimate of how many people will die by suicide.
Survey participation, recall and how a sensitive question is asked can affect reporting. Face-to-face and self-completion results should not be combined into one trend unless the source supports that comparison.
Survey answers and death registrations answer different questions. Not everyone who experiences suicidal thoughts attempts suicide. Any disclosure should nevertheless be taken seriously and met with compassionate support.
Keeping specific-group evidence in context
Occupational evidence: a clearly dated finding
ONS’s analysis of deaths registered in England in 2011–15 found a suicide risk 3.7 times the male average among men aged 20–64 in elementary construction occupations. This is a historical occupational result, not a current-year estimate for every construction worker.
Occupation recorded at death does not establish that work caused the death. Prevention should use evidence for the relevant workforce and period, alongside attention to harmful working conditions, accessible support and routes to professional care.
LGBT survey evidence and veteran studies
Stonewall’s 2018 report, based on a 2017 Great Britain survey, found that 13% of LGBT respondents aged 18–24 reported a suicide attempt in the previous year. This historical survey finding is not a current population death rate.
Veteran studies also require careful separation of age, sex, service history, departure circumstances and follow-up period. A finding about young service leavers cannot be applied to all veterans or serving personnel. Support can address both mental health needs and practical difficulties during transition to civilian life.
People can experience several sources of distress at once, including discrimination, unemployment, physical illness or mental ill health. Support should recognise the whole person and their circumstances. A group-level association is not a prediction that an outcome is inevitable.
Prevention centres on people.
Suicidal feelings can change, and support is available. Immediate safety, current circumstances and access to help matter more than any single population statistic.
England’s suicide prevention strategy for 2023–28 combines population-wide action, tailored support for priority groups and help for people in crisis. It considers factors including financial difficulty, isolation, abuse, physical and mental ill health and access to care.
There is no single explanation for every death, and different forms of support may be needed for different people. Local planning can draw on national evidence while involving healthcare services, local authorities, employers and community organisations.
Respond to the person, not the percentage
Take a person’s distress seriously. Listen without judgement, ask directly about suicidal thoughts and help them reach professional support. If there is immediate danger, seek emergency assistance.
Talking about wanting to die, feeling like a burden, withdrawing from others or changes in behaviour can be reasons to check in. A list of signs cannot reliably identify everyone who needs help, and the absence of an obvious sign does not establish that someone is safe.
Reading and sharing the figures carefully.
How many suicides were registered in the UK?
The separately compiled UK figure was 7,147 registrations in 2024. The newer ONS headline of 6,162 covers England and Wales in 2025. They differ in both year and geography, so they cannot be used as a direct year-on-year comparison.
Did all the deaths registered in 2025 happen in 2025?
No. Some occurred earlier. Registration can follow an investigation or inquest, which is why ONS also publishes occurrence-based analysis with its own completeness limits.
Why use a rate instead of just a count?
A rate takes population size into account. Age-standardisation also accounts for differences in age structure. The count remains important, but it answers a different question from a population rate.
Why do the age and sex charts use different rate types?
The sex comparison uses age-standardised rates to account for different age structures. The age chart uses age-specific rates within each band. A broad age band can contain substantial variation, so it should not replace a detailed age-specific finding.
Are suicidal thoughts and suicide attempts the same measure?
No. They describe different experiences, and neither is the same as registered deaths. Survey figures need their own question, reference period, population and interview mode. Any disclosure of suicidal thoughts should be met with support.
Can these statistics predict an individual’s suicide risk?
No. Population patterns help inform prevention but cannot determine what will happen to one person. Immediate safety, the person’s circumstances and access to support require individual attention.
Methods, uncertainty and responsible reuse
This guide is an original visual presentation of published evidence, not a new survey. It keeps death registrations, occurrence-based analysis and household-survey results separate. It does not estimate unreported deaths or create a new UK series.
All charts start at zero. Published confidence intervals are shown where available; where they are not supplied, none are invented. Exact source values and locators are retained in the CSVs, while chart labels may round for readability.
A difference in point estimates does not by itself establish a statistically significant difference, and an association does not establish a cause. Comparisons need matching ages, geography, definition and period. Keep those details with the figure when sharing it.
Suicide statistics charts.
With the context to use them.
Download the charts, source data and methodology. Keep the geography, period, measure and uncertainty with each figure. Use sensitive language and remember that population statistics cannot predict an individual outcome.
Mental Health First Aid Course (2026). Suicide Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/suicide-statistics
Understanding the scale of suicide is the first step in prevention. Mental Health First Aid training teaches people to recognise warning signs of suicide risk, have supportive conversations with those experiencing suicidal thoughts, and help them access professional support. With 25.2% of adults aged 16 and over in England reporting lifetime suicidal thoughts in APMS 2023/24, widespread public awareness and frontline worker training are essential.
Mental Health First Aid for Suicide Prevention
Mental Health First Aid (MHFA) training includes specific modules on recognising and responding to suicide risk. MHFA-trained individuals learn to: recognise warning signs of suicide risk, start supportive conversations about suicide, listen without judgment or trying to fix the problem, validate the person's feelings while keeping them safe, encourage professional help-seeking, and know about local and national crisis resources. MHFA training emphasises that asking someone if they're thinking about suicide does not increase risk but rather demonstrates caring and opens the door to support. Training covers how different occupational groups experience suicide risk and tailored approaches for construction workers, healthcare workers, and other professionals. With high suicide rates across the UK, having more MHFA-trained supporters in workplaces, schools, and communities could help identify at-risk individuals and facilitate early intervention.
Sources
Primary evidence and methodology. Checked 16 October 2026.
- ONS: Suicides in England and Wales, 1981–2025Published 13 October 2026.
- ONS: Suicide registration reference tablesPublished 13 October 2026.
- ONS: Suicide occurrence reference tablesPublished 13 October 2026.
- ONS: Suicide rates quality and methodologyPublished 3 October 2025.
- NHS England: APMS suicidal thoughts, attempts and self-harmPublished 27 November 2025.
- House of Commons Library: Suicide statisticsPublished 8 January 2026.
- ONS: Suicide by occupation, England 2011–2015Published 17 March 2017.
- Stonewall: LGBT in Britain — Health (2018)
- NHS: Help for suicidal thoughts
- DHSC: Suicide prevention strategy for England, 2023–2028Published 11 September 2023.
- NHS England: APMS source tables
- National Records of Scotland: Probable Suicides 2024
- NISRA: Suicide Statistics 2024