
Depression Statistics UK: 2026 Facts, Data & Key Insights
Depression statistics UK
A closer look at depression, depressive symptoms and treatment — with the definitions behind the numbers.

Met the survey criteria for a depressive episode in the past week.
England · adults aged 16+ · APMS 2023/24Reported medication, psychological therapy, or both, among adults identified with depression.
England · adults aged 16+ · APMS 2023/24Treatment may concern any mental or emotional problem.
Reported moderate to severe depressive symptoms over the previous two weeks.
Great Britain · adults aged 16+ · ONS April 2025Depression and symptoms are not the same statistic.
There is no single percentage that answers every question about depression. A structured survey assessment, a symptom questionnaire and a service record measure different things. Reading the definition first makes the statistics more useful.
A depressive episode
The Adult Psychiatric Morbidity Survey uses the Clinical Interview Schedule–Revised (CIS-R) and an ICD-10 algorithm to identify depressive episode. The prevalence estimate concerns the past week. It is a survey assessment, not a count of diagnoses recorded by GPs.
Depressive symptoms
The Opinions and Lifestyle Survey uses the eight-item Patient Health Questionnaire (PHQ-8). A score of 10 or above indicates moderate to severe symptoms over the previous two weeks. This questionnaire threshold is not interchangeable with an APMS depressive episode.
Care and treatment
Prescribing and talking-therapy records describe contact with services. They do not count every person experiencing depression. Medicines can be prescribed for other conditions, while referrals and patients are different units.
The APMS all-adult estimate is 3.8%, with a 95% confidence interval of 3.3%–4.5%. The ONS symptom estimate is 18%. Subtracting one from the other would not reveal a group with “undiagnosed depression”: the instruments, reference periods, geography and survey design differ.
These studies also describe populations rather than individuals. A person’s symptoms, circumstances and support needs cannot be inferred from their age, gender or neighbourhood. Persistent difficulties deserve attention regardless of whether someone resembles the group with the highest estimate.
Five survey waves. One comparable age range.
The comparable APMS series follows adults aged 16–64 in England across five survey waves. This common age range avoids comparing the earliest working-age survey with a later survey that also includes older adults.
The latest point is 4.4% in 2023/24, compared with 2.2% in 1993. These are separate population samples, not the same people followed over three decades. The chart does not supply values for the years between surveys.
Past-week depressive episode among adults aged 16–64 in England, 2023/24.
The all-adult figure of 3.8% uses a different age range.
Depression across five survey waves
CIS-R survey-assessed depressive episode in the past week
| Group / response | Estimate | 95% interval | Sample |
|---|---|---|---|
| 1993 | 2.2% | 1.9–2.5% | 8,903 |
| 2000 | 2.8% | 2.4–3.2% | 6,175 |
| 2007 | 2.6% | 2.2–3.1% | 5,425 |
| 2014 | 3.8% | 3.2–4.4% | 5,295 |
| 2023/24 | 4.4% | 3.8–5.2% | 4,520 |
Five separate England surveys, all restricted to ages 16–64. Whiskers show published 95% confidence intervals. The intervals describe sampling uncertainty, not every possible bias; no annual estimates have been interpolated.
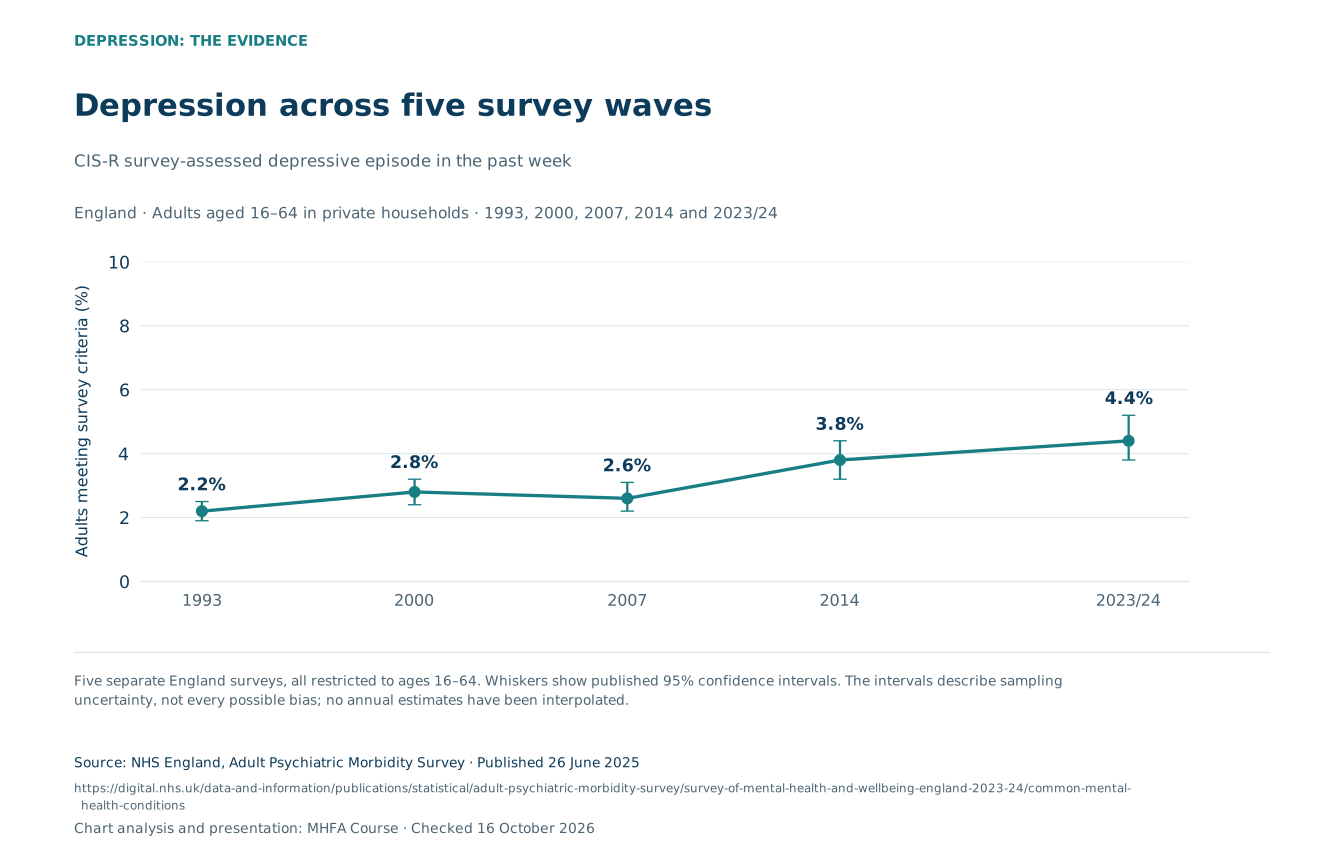
The series gives a longer view than a single year’s headlines. It should not be used to claim a new rise during 2026 or a smooth annual increase. Changes in the estimates can reflect many influences, and the survey alone does not identify the cause of a trend.
Why the trend uses ages 16–64
The earliest APMS wave covered adults aged 16–64. Later surveys included older age groups, so the long-term comparison restricts every wave to the same age range and England geography. The 2023/24 estimate for ages 16–64 should not be substituted for the 3.8% all-adult headline.
The five columns represent separate surveys at unequal time intervals. The download chart uses calendar-year spacing, and both versions retain the exact published estimates and confidence intervals. No annual values have been interpolated.
Depression across age and gender.
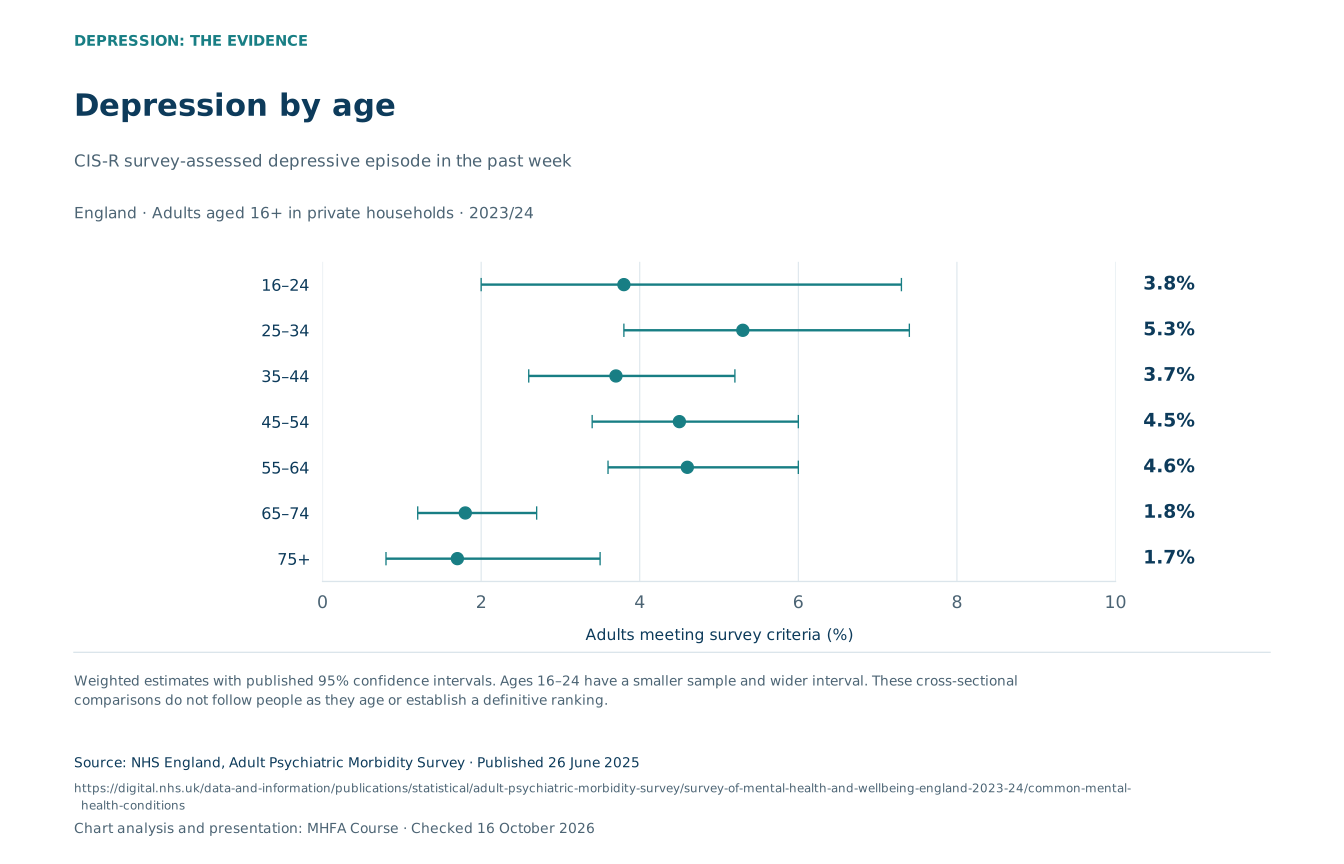
APMS provides detailed comparisons within its latest survey. The charts below retain published confidence intervals so the uncertainty is visible alongside the headline estimates. A higher point estimate does not by itself establish a statistically significant difference.
Depression by age
CIS-R survey-assessed depressive episode in the past week
Whiskers show 95% confidence intervals.
| Group / response | Estimate | 95% interval | Sample |
|---|---|---|---|
| 16–24 | 3.8% | 2–7.3% | 316 |
| 25–34 | 5.3% | 3.8–7.4% | 842 |
| 35–44 | 3.7% | 2.6–5.2% | 1,074 |
| 45–54 | 4.5% | 3.4–6% | 1,047 |
| 55–64 | 4.6% | 3.6–6% | 1,241 |
| 65–74 | 1.8% | 1.2–2.7% | 1,234 |
| 75+ | 1.7% | 0.8–3.5% | 1,146 |
Weighted estimates with published 95% confidence intervals. Ages 16–24 have a smaller sample and wider interval. These cross-sectional comparisons do not follow people as they age or establish a definitive ranking.
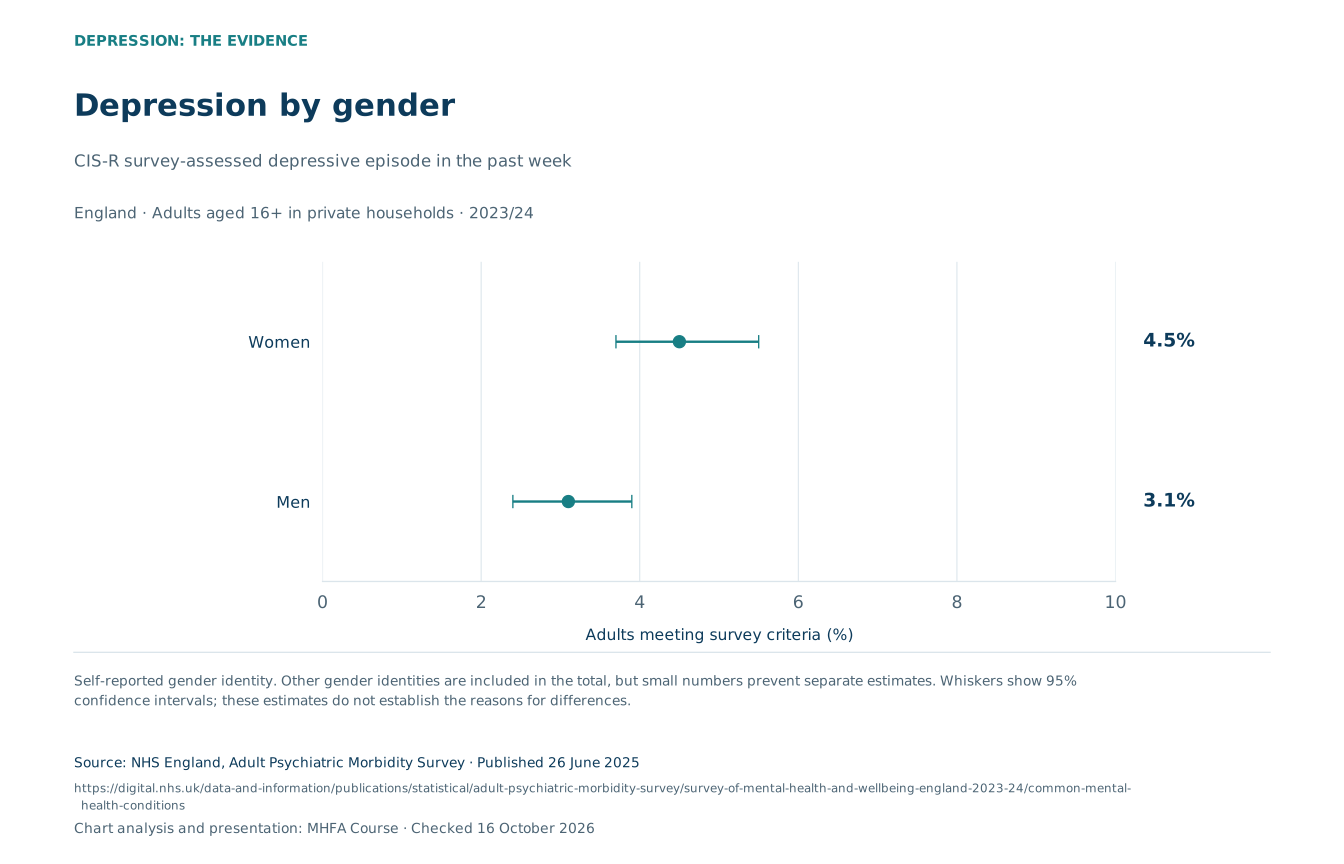
Depression by gender
CIS-R survey-assessed depressive episode in the past week
Whiskers show 95% confidence intervals.
| Group / response | Estimate | 95% interval | Sample |
|---|---|---|---|
| Women | 4.5% | 3.7–5.5% | 3,972 |
| Men | 3.1% | 2.4–3.9% | 2,930 |
Self-reported gender identity. Other gender identities are included in the total, but small numbers prevent separate estimates. Whiskers show 95% confidence intervals; these estimates do not establish the reasons for differences.
Gender, with its source definition
The reported prevalence was 4.5% among women and 3.1% among men. APMS uses self-reported gender identity for these results. People with other gender identities contribute to the total, but separate estimates are not published because the sample is too small.
These figures describe survey groups. They do not establish why the estimates differ, or imply that depression looks the same in every person within a group.
Age comparisons are a snapshot. They do not show that a person’s depression will improve or worsen simply as they get older. The survey covers private households, so these estimates do not describe everyone in care homes, hospitals or other communal settings.
Intervals are particularly useful when comparing smaller groups. Their width describes sampling uncertainty; it does not include every possible source of error, such as non-response or how people understand and answer the questions.
How the estimates vary across neighbourhoods.
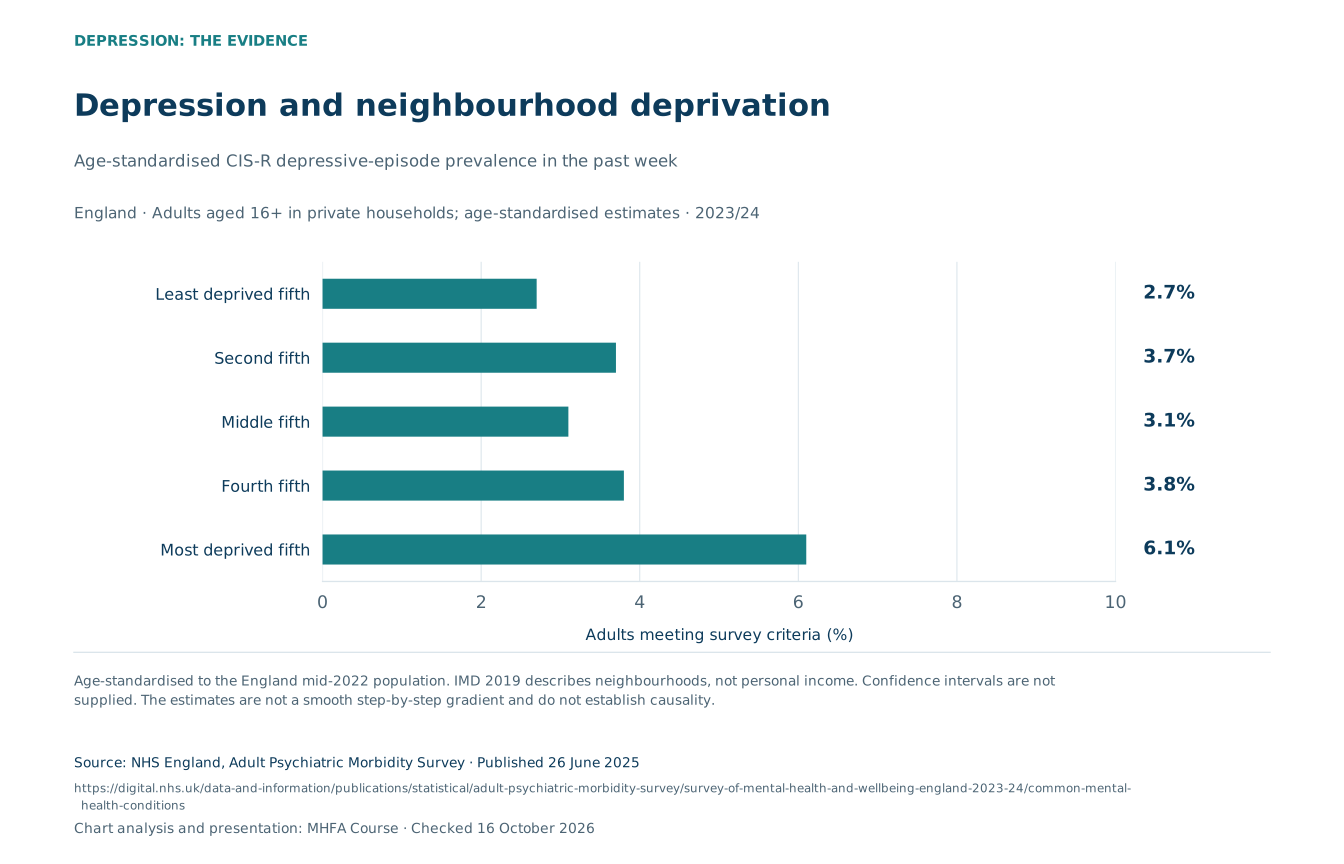
Depression and neighbourhood deprivation
Age-standardised CIS-R depressive-episode prevalence in the past week
| Group / response | Estimate | 95% interval | Sample |
|---|---|---|---|
| Least deprived fifth | 2.7% | Not supplied | 1,204 |
| Second fifth | 3.7% | Not supplied | 1,208 |
| Middle fifth | 3.1% | Not supplied | 1,242 |
| Fourth fifth | 3.8% | Not supplied | 1,059 |
| Most deprived fifth | 6.1% | Not supplied | 2,180 |
Age-standardised to the England mid-2022 population. IMD 2019 describes neighbourhoods, not personal income. Confidence intervals are not supplied. The estimates are not a smooth step-by-step gradient and do not establish causality.
Neighbourhoods, rather than personal income
The age-standardised estimates are 2.7% in the least deprived fifth of neighbourhoods and 6.1% in the most deprived fifth. The categories use the English Index of Multiple Deprivation 2019. The values do not increase at every step between those endpoints.
Age standardisation allows for the different age profiles of people living in these groups of areas. It does not remove every difference in their circumstances, and the measure describes a neighbourhood rather than an individual’s income.
This association can help describe where needs may differ. It cannot establish that a particular address caused depression or that moving would resolve it. Health, work, finances and social circumstances can be connected in more than one direction.
The published table does not supply confidence intervals for these age-standardised depression estimates. No intervals have been calculated or invented for this chart.
What does treatment receipt tell us?
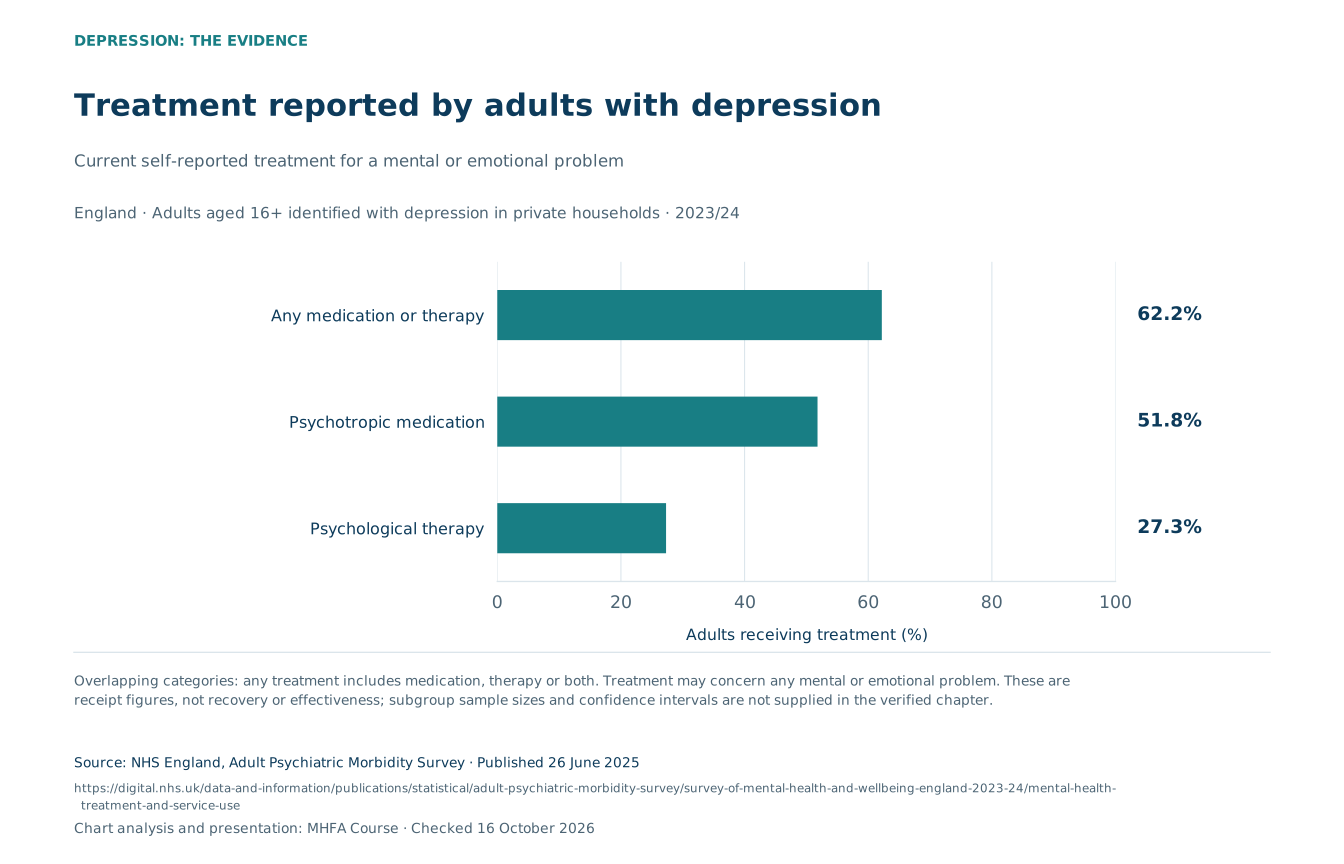
Among adults identified with depression in APMS, 62.2% reported receiving psychotropic medication, psychological therapy, or both. The questions concern treatment for any mental or emotional problem; they do not establish that every treatment was specifically for depression.
Treatment reported by adults with depression
Current self-reported treatment for a mental or emotional problem
| Group / response | Estimate | 95% interval |
|---|---|---|
| Any medication or therapy | 62.2% | Not supplied |
| Psychotropic medication | 51.8% | Not supplied |
| Psychological therapy | 27.3% | Not supplied |
Overlapping categories: any treatment includes medication, therapy or both. Treatment may concern any mental or emotional problem. These are receipt figures, not recovery or effectiveness; subgroup sample sizes and confidence intervals are not supplied in the verified chapter.
Overlapping forms of care
51.8% reported medication and 27.3% reported psychological therapy. Some received both. The categories overlap, so the two percentages should not be added or drawn as slices of a whole.
Treatment receipt is different from treatment effectiveness. These findings do not tell us whether care matched a person’s needs, whether they were waiting for another service, or whether symptoms had improved. The percentage outside the “any treatment” category is not automatically an estimate of unmet clinical need.
The treatment figures describe adults who still met the survey criteria at the time they were interviewed. They should not be read as the outcome of following everyone who started treatment.
Service and prescribing context: England, 2025/26
NHS Talking Therapies recorded 1.81 million referrals, 1.17 million accessing services and 674,683 completing treatment in 2025/26. These are not one common cohort or necessarily unique people. Among eligible completed referrals, 50.1% moved below the service’s clinical symptom thresholds; this covers anxiety and depression, not depression alone or permanent cure.
89.1% of referrals completing treatment had started within six weeks. That is not the percentage of everyone currently waiting. The annual report was published on 24 September 2026.
NHSBSA reported 9.1 million identified patients prescribed antidepressants in England in 2025/26, subsequently dispensed in the community. The release was published on 23 July 2026. Antidepressants have other uses, so this is not a count of people with depression; secondary-care, prison and private-prescriber data are excluded.
What treatment can involve
NHS guidance describes several approaches, including talking therapies and medicines, chosen according to symptoms, severity, preferences and circumstances. Care may involve more than one approach. A survey average cannot identify the best option for a particular person.
Seeking an assessment
If symptoms persist or affect daily life, a GP can help assess what is happening and discuss support. Adults in England can also self-refer to NHS Talking Therapies for anxiety and depression. A questionnaire score is a starting point for understanding symptoms, not a substitute for a clinical assessment.
Importantly, treatment is most effective when started early. People who wait months or years before seeking help for depression often experience more entrenched, difficult-to-treat symptoms. Early identification and intervention, ideally by someone trained in Mental Health First Aid, can make a critical difference in outcomes. MHFA training equips people to recognise depression in friends, family, colleagues, and themselves, and to gently encourage help-seeking at an earlier stage when treatment is typically more effective.
How did people feel in April 2025?
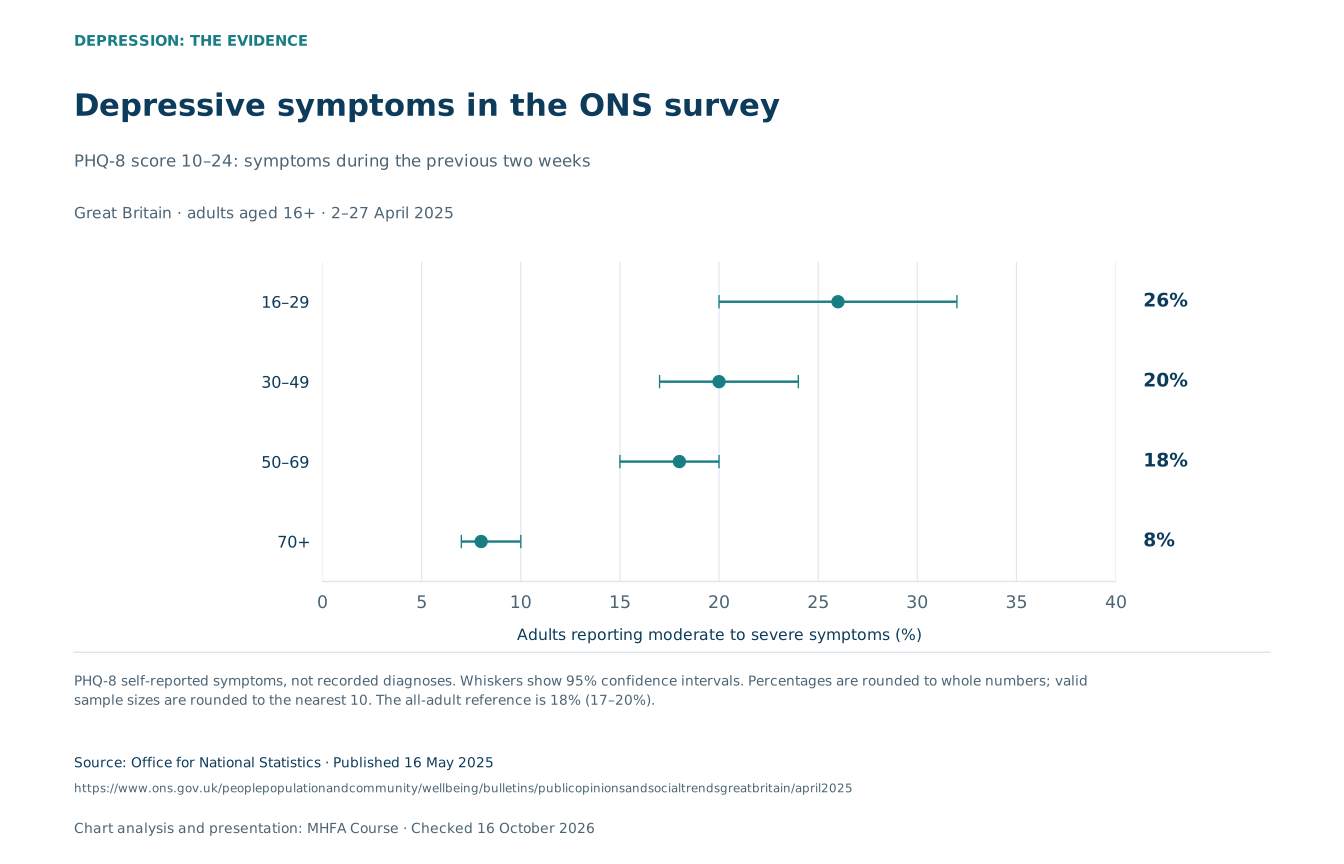
ONS offers a more recent but different view: 18% of adults aged 16+ in Great Britain reported moderate to severe depressive symptoms in April 2025. The 95% confidence interval is 17%–20%. This is the latest published edition of this PHQ-8 dataset at the check date; its next release is not yet announced.
Depressive symptoms in the ONS survey
PHQ-8 score 10–24: symptoms during the previous two weeks
Whiskers show 95% confidence intervals.
Reference: All adults aged 16+ 18% (95% confidence interval 17–20%). This total includes the age groups above.
| Group / response | Estimate | 95% interval | Sample |
|---|---|---|---|
| 16–29 | 26% | 20–32% | 260 |
| 30–49 | 20% | 17–24% | 660 |
| 50–69 | 18% | 15–20% | 1,710 |
| 70+ | 8% | 7–10% | 1,960 |
| All adults aged 16+ (reference) | 18% | 17–20% | 4,600 |
PHQ-8 self-reported symptoms, not recorded diagnoses. Whiskers show 95% confidence intervals. Percentages are rounded to whole numbers; valid sample sizes are rounded to the nearest 10. The all-adult reference is 18% (17–20%).
A separate view of symptoms
The estimate was 26% among adults aged 16–29, compared with 8% among those aged 70 and over. The younger group has a much smaller sample and a wider interval. The different age bands cannot be lined up directly with the APMS age chart.
Respondents answered questions about symptoms during the previous two weeks. ONS classified scores of 10–24 on the PHQ-8 as moderate to severe. The result is neither a record of diagnosed depression nor the proportion newly developing depression during that fortnight.
Great Britain includes England, Scotland and Wales, but excludes Northern Ireland. This source therefore does not supply an interchangeable UK-wide clinical prevalence rate.
Sample size and uncertainty in the ONS results
The April 2025 Opinions and Lifestyle Survey had 4,617 responding adults and a 48% response rate. The valid PHQ-8 sample was 4,600, rounded to the nearest 10; missing or invalid symptom scores were excluded. These figures should not be treated as identical denominators.
The published valid sample for ages 16–29 is 260, compared with 1,960 for ages 70+. These are rounded respondent counts, not the number with symptoms. Weighting adjusts for observed demographic differences and non-response, but cannot remove every possible source of bias. The confidence intervals remain visible in the chart and CSV.
Specific groups: students and new mothers, with dates retained
In the ONS survey of foundation and first-year undergraduates at participating universities in England, 37% reported moderate to severe depressive symptoms and 39% screened positive for likely anxiety. Fieldwork was 4–11 October 2021. This low-response, pandemic-period survey is historical context, not a current estimate for all students.
England’s 2024 National Maternity Survey found 22.5% screened positive for depressive symptoms on the EPDS around six months after birth (95% interval 21.0%–24.2%). The 2026 NPEU report (version dated 3 March 2026) covers women who gave birth in May 2024. A screening result is not a clinical diagnosis, and this different instrument is not plotted against APMS or PHQ-8.
Keep the instrument with the number. “18% with moderate to severe depressive symptoms in the April 2025 ONS survey” preserves the meaning. Simply saying “18% had diagnosed depression in 2026” changes both the measure and the period.
Workplace statistics need their own boundaries.
Depression can affect concentration, energy and everyday functioning. Population statistics can help organisations understand why support matters, but they cannot determine an individual employee’s diagnosis or what adjustments they need.
HSE estimated 964,000 workers with work-related stress, depression or anxiety and 22.1 million working days lost in Great Britain in 2024/25. This combined category is useful workplace context, but it does not identify a depression-only total. It also has a different population and question from the household surveys above.
Creating supportive workplaces where depression is recognised and accommodated requires mental health literacy among managers and colleagues. Training programmes like workplace mental health awareness are critical in helping organisations identify struggling employees, offer appropriate support, and implement workplace changes that reduce depression risk factors such as excessive workload and lack of control.
Reading depression statistics with care.
How common is depression in the UK?
The latest APMS estimate is 3.8% for a past-week depressive episode among adults aged 16+ in England. A separate ONS survey found moderate to severe depressive symptoms in 18% of adults aged 16+ in Great Britain in April 2025. They answer different questions; neither should be relabelled as a UK-wide diagnosis rate.
Why are the figures so different?
APMS uses a structured assessment and ICD-10 algorithm for depressive episode. ONS uses a PHQ-8 symptom-score threshold. They also cover different places and reference periods. The gap between them is not a measurement of undiagnosed cases.
Does “past week” mean symptoms lasted only a week?
No. It describes the prevalence reference period used by APMS. The assessment also considers the features and duration of symptoms needed for its classification. It should not be interpreted as saying depression begins and ends within one week.
Do antidepressant prescriptions measure depression prevalence?
No. Antidepressants can be used for conditions other than depression, some people with depression receive other treatment or no treatment, and prescription items are not the same as individual people. Prescribing statistics need their own definition and denominator.
Can these charts show which treatment works best?
No. The treatment chart describes reported receipt among people identified with depression. It does not compare clinical effectiveness. Differences in needs and circumstances mean a simple comparison of service percentages would not establish the best treatment for an individual.
Why are older survey years still used in a 2026 guide?
Large population surveys take time to collect, analyse and publish. These are the latest verified editions at 16 October 2026. The dates stay visible so a current evidence review is not mistaken for new fieldwork in 2026.
How the evidence was selected and presented
The main charts use the latest APMS prevalence and treatment tables, with a separate chart from the latest ONS depressive-symptom module. Different instruments, age ranges and geographical coverage are never joined into one series.
APMS interviewed 6,912 adults in its first phase. Its household response rate was 29.4%, compared with 57% in 2014. Weighting adjusts for selection and non-response, but cannot remove all potential bias. Its private-household sampling frame excludes many people in communal or institutional accommodation and those sleeping rough.
Published confidence intervals describe sampling uncertainty. They do not capture every possible measurement error. Where an interval is not supplied, none is invented. Values retain the published display precision; download files include source locators and underlying precision where available.
Group differences and associations are descriptive. They do not establish causes, predict an individual’s future or demonstrate the effect of a treatment. These charts are an original presentation of published evidence, not a new population survey.
Useful charts.
Definitions included.
Download six charts as SVG and PNG, with the underlying CSV data, published confidence intervals and methodology notes. Keep the measure, geography, age range and period with each figure when sharing it.
Mental Health First Aid Course (2026). Depression Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/depression-statistics
Supporting Those with Depression: The Role of Mental Health First Aid
The April 2025 ONS survey found moderate to severe depressive symptoms in 18% of adults in Great Britain. Supporting a person with depression requires compassion, patience, and accurate knowledge about the condition. This is where Mental Health First Aid (MHFA) training becomes invaluable. MHFA training teaches people to recognise signs of depression, start conversations about mental health, and guide people toward professional help. MHFA responders are trained to avoid judgement, understand that depression is a medical condition not a character flaw, and provide practical support that reduces isolation and increases help-seeking likelihood.
In the context of depression specifically, MHFA training covers understanding the condition's symptoms and impacts, recognising that depression can present differently in different people, appreciating the biological, psychological, and social factors that contribute to depression, and knowing what professional treatments are available. MHFA responders learn not to "talk someone out of" depression through positive thinking or logical argument, but instead to listen, validate the person's experience, and encourage professional help. This approach respects the real, biological nature of depression whilst maintaining hope in recovery.
By equipping individuals, workplaces, schools, and communities with MHFA knowledge, we create an invisible infrastructure of support that surrounds people with depression before they reach crisis point. Friends notice early signs and gently suggest professional help. Managers provide workplace flexibility and access to occupational health services. Family members avoid inadvertently worsening depression through criticism or unrealistic expectations. Colleagues provide social connection and normalise help-seeking. This multiplier effect makes MHFA training a public health intervention of considerable importance in addressing the depression epidemic.
Sources
Primary evidence and methodology. Checked 16 October 2026.
- NHS England: APMS common mental health conditionsEngland private-household adults, 2023/24. Prevalence published 26 June 2025.
- APMS Chapter 1 published data tablesTables 1.3, 1.4, 1.9, A2 and B2: estimates, confidence intervals and sample bases.
- NHS England: APMS treatment and service useCurrent treatment among adults identified with depression; overlapping categories.
- APMS MethodsFieldwork March 2023–July 2024; sampling, response rates and weighting.
- APMS How to interpret the findingsDefinitions, uncertainty and limits on interpreting differences.
- Official APMS Part 1 release announcementConfirms the first release date of 26 June 2025.
- ONS April 2025 bulletinGreat Britain adults aged 16+, fieldwork 2–27 April 2025; published 16 May 2025.
- ONS mental-health dataset and latest-edition listingLatest PHQ-8 edition checked 16 October 2026; next release to be announced.
- ONS April 2025 mental-health workbookTable 1: PHQ-8 symptoms, confidence intervals and rounded valid sample sizes.
- ONS Opinions and Lifestyle Survey quality and methodsSurvey design, weighting, non-response and interpretation.
- NHS Talking Therapies annual report 2025/262025/26 annual results, published 24 September 2026; referral-based measures.
- NHSBSA Medicines used in mental health 2016/17–2025/26Community antidepressant prescribing in England; people and prescription items are distinct.
- NPEU You & Your Baby 2024 reportEngland 2024 National Maternity Survey; EPDS screening around six months after birth; report version dated 3 March 2026.
- HSE Work-related stress, depression or anxiety 2025Great Britain, 2024/25; combined work-related stress, depression or anxiety.
- NHS: Depression in adults overviewRecognising symptoms and seeking an assessment.
- NHS: Treatment for depression in adultsTreatment choices and self-referral to NHS Talking Therapies in England.
- ONS: first-year higher education students, October 2021Historical England foundation/first-year sample, fieldwork 4–11 October 2021; published 27 October 2021.