
Student Mental Health Statistics UK: 2026 Facts, Data & Key Insights
Student mental health statistics UK
What students report about their mental health, loneliness and everyday pressures—and how to read the evidence without confusing different measures.

Reported a mental-health difficulty in the 2025 survey.
UK full-time undergraduatesTASO analysis published August 2026
Agreed that they felt a sense of belonging at their institution.
UK full-time undergraduatesStudent Academic Experience Survey 2026
Cited mental or emotional health among those who had considered leaving.
UK full-time undergraduates considering withdrawal2026 survey · conditional denominator
There is more than one measure of student mental health.
University can bring new relationships, independence and opportunities alongside academic, financial and personal pressures. Students’ experiences differ. A national survey helps describe patterns, but it cannot tell us how a particular student feels or what support they need.
The most useful starting point is the question being asked. Low wellbeing, symptoms on a questionnaire, a reported difficulty and a condition disclosed to a university are different outcomes. Treating them as one prevalence rate can create a misleading picture of both the scale of need and the support available.
This guide keeps the dates and populations attached to each finding. UK full-time undergraduates, first-year students at universities in England, and all higher-education students in England and Wales are not interchangeable groups.
Wellbeing and symptoms
A wellbeing question describes how someone feels. A symptom questionnaire can identify a threshold for further assessment. Neither automatically establishes a clinical diagnosis.
What students report
Students may say that they have a mental-health difficulty. The wording and available responses matter, including whether a professional diagnosis is required.
What students disclose
A condition recorded by a university depends on disclosure and recording. It cannot count every student experiencing difficulties or tell us how many receive appropriate support.
What a survey can—and cannot—establish
Survey results describe the responding population using the study’s questions and methods. Even a large survey can have limitations from who responds, the wording of questions and the representation of smaller groups.
A difference between groups does not establish its cause. Financial pressures, academic demands, relationships, discrimination and existing difficulties may intersect, but a single survey comparison cannot separate all those influences.
A newer publication does not necessarily update every older question. We keep historical findings where they answer a distinct question, and avoid joining different populations or measures into an artificial trend.
Who is represented in the main surveys?
SAES covers full-time undergraduates at UK higher-education institutions. It does not represent every postgraduate, part-time student or further-education learner.
The 2025 survey included 10,232 respondents; the 2026 survey included 10,065. These are overall samples, not automatically the valid-answer base for each question or subgroup.
TASO describes online panel recruitment and an approximately 10% response rate. Survey weights improve representation on specified characteristics, but cannot remove every source of response bias. Each annual survey uses a different sample; the trend does not follow the same students through their degrees.
Wellbeing and a sense of belonging.
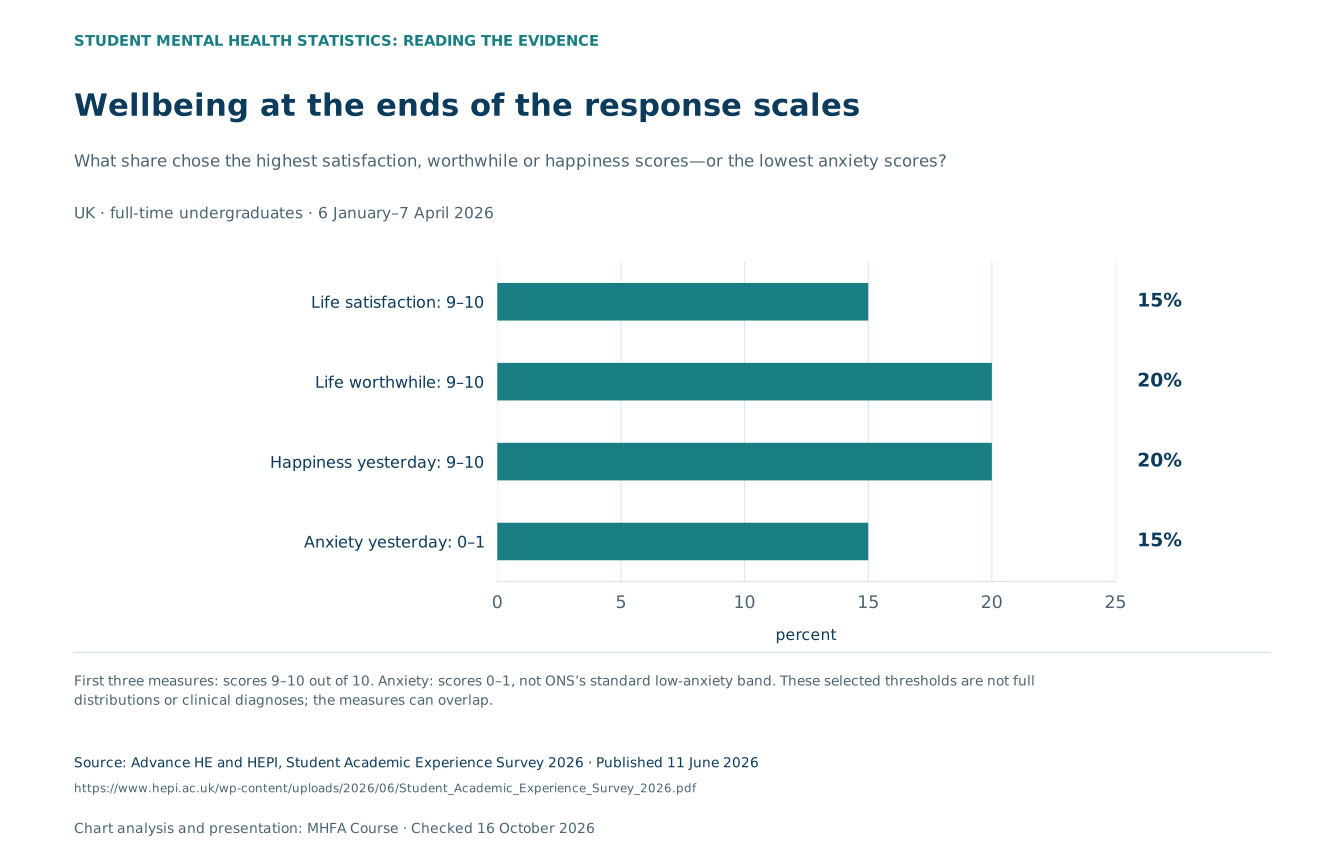
The 2026 Student Academic Experience Survey asked 10,065 UK full-time undergraduates about their experience. Its wellbeing questions cover life satisfaction, whether life feels worthwhile, and happiness and anxiety yesterday.
The chart shows selected ends of the response scales: scores of 9–10 out of 10 for the first three measures and 0–1 out of 10 for anxiety. It does not show the full distribution or the share with a mental-health condition.
For example, 15% gave the highest life-satisfaction ratings. That does not mean everyone else was dissatisfied: the remaining students could choose any of the other scores. The anxiety threshold here is also more restrictive than ONS’s usual low-anxiety band of 0–3, so those percentages should not be compared directly.
Wellbeing at the ends of the response scales
What share chose the highest satisfaction, worthwhile or happiness scores—or the lowest anxiety scores?
| Group / measure | percent |
|---|---|
| Life satisfaction: 9–10 | 15% |
| Life worthwhile: 9–10 | 20% |
| Happiness yesterday: 9–10 | 20% |
| Anxiety yesterday: 0–1 | 15% |
First three measures: scores 9–10 out of 10. Anxiety: scores 0–1, not ONS’s standard low-anxiety band. These selected thresholds are not full distributions or clinical diagnoses; the measures can overlap.
Feeling a sense of belonging
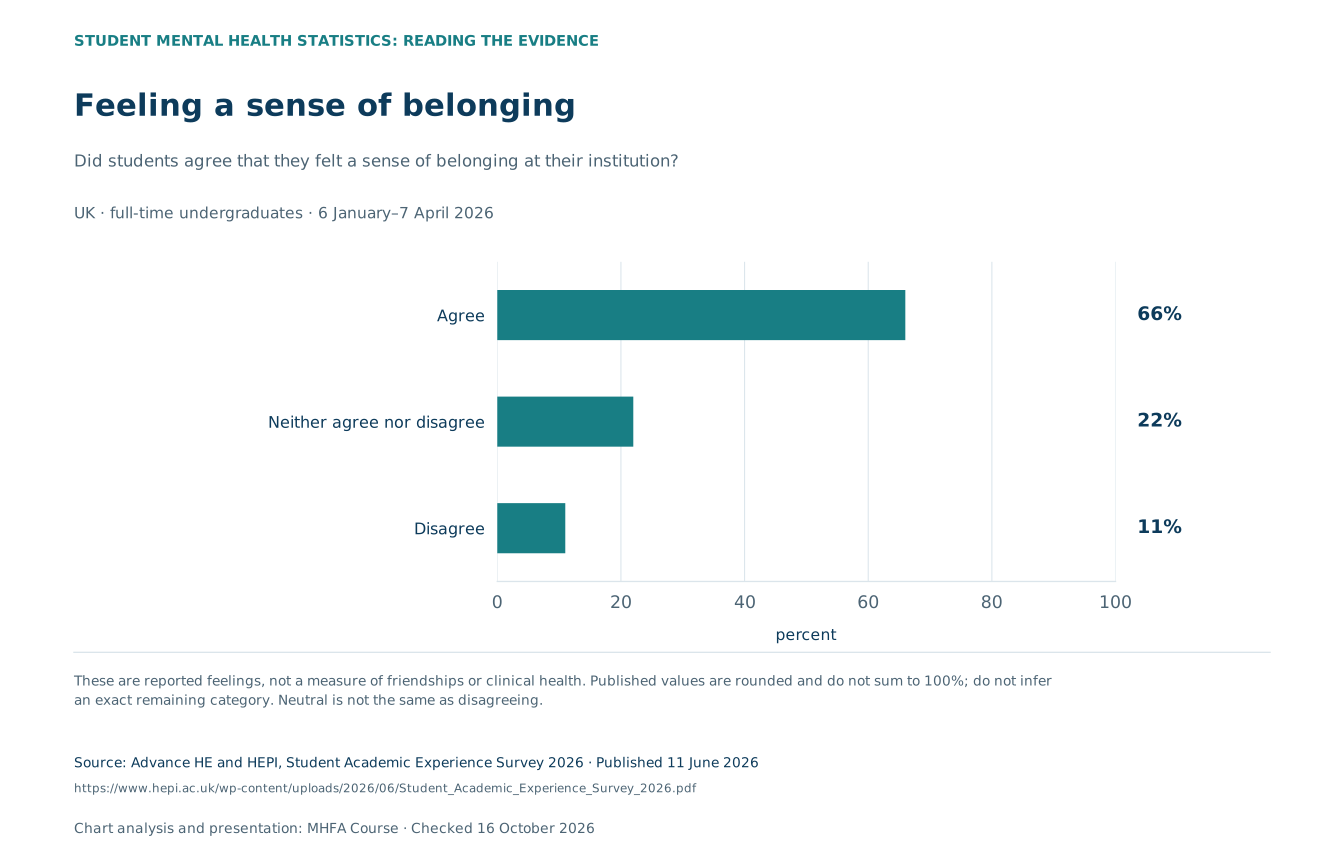
Did students agree that they felt a sense of belonging at their institution?
| Group / measure | percent |
|---|---|
| Agree | 66% |
| Neither agree nor disagree | 22% |
| Disagree | 11% |
These are reported feelings, not a measure of friendships or clinical health. Published values are rounded and do not sum to 100%; do not infer an exact remaining category. Neutral is not the same as disagreeing.
Belonging is a different part of the picture.
66% agreed that they felt a sense of belonging at their institution. 22% gave a neutral response and 11% disagreed.
These published rounded figures are not a complete set from which to calculate an exact remainder. Neutral responses should not be described as rejection or isolation. Feeling that you belong is also different from how often you feel lonely or how many friends you have.
Students may find connection through their course, accommodation, societies or other communities. The survey does not show that one particular activity caused better wellbeing or that everyone with a lower belonging score needs the same response.
Who reports difficulties—and what does that mean?
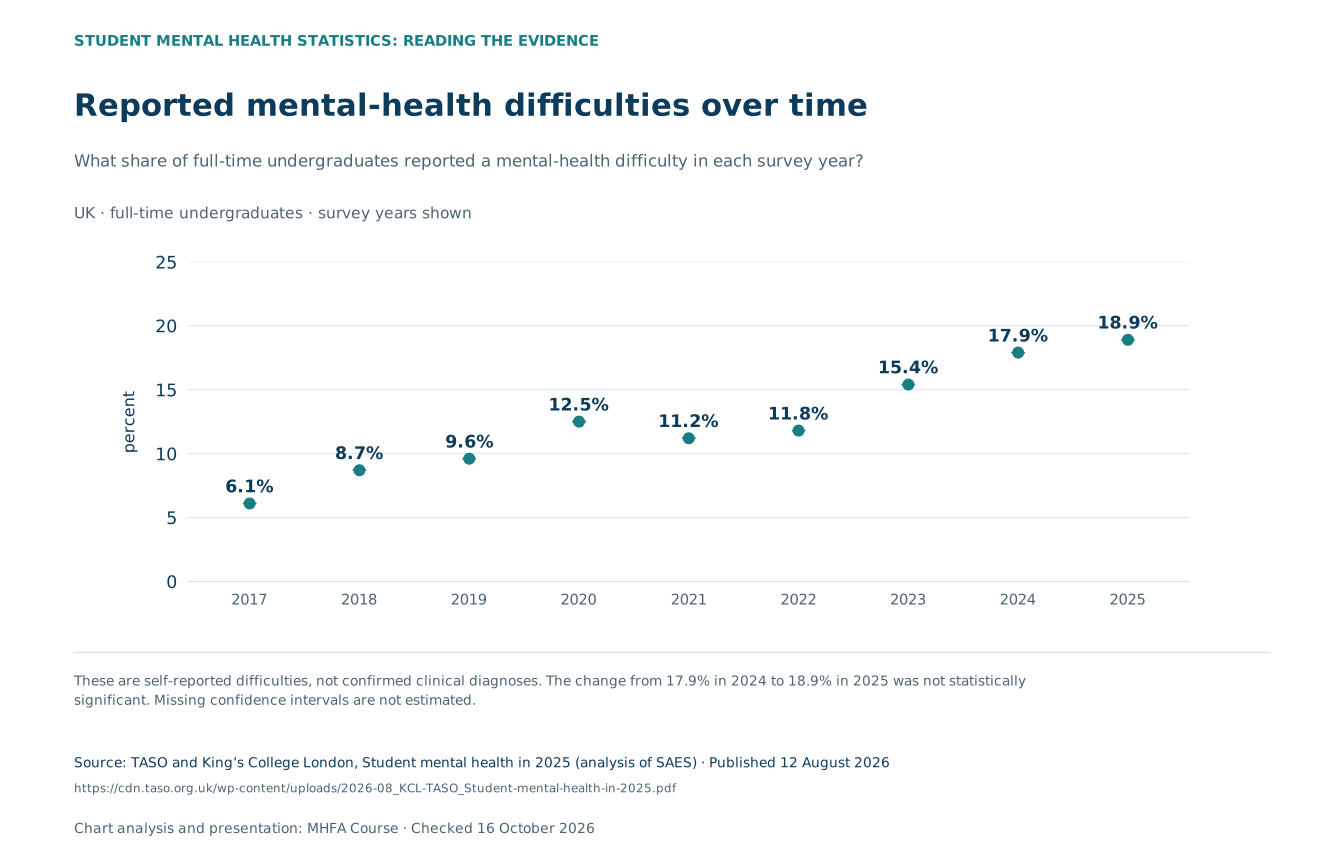
TASO’s analysis of the 2025 survey found that 18.9% of full-time undergraduates reported a mental-health difficulty, compared with 17.9% in 2024. The report did not find this latest change statistically significant.
The longer series describes reported difficulties under the survey question. It should not be presented as a trend in clinically diagnosed illness or used to infer how many students were receiving treatment.
The group comparisons below show differences in what respondents reported. Gender and sexual orientation are separate characteristics; the categories in the two charts must not be added or collapsed into a single LGBTQ+ risk multiplier.
Reported mental-health difficulties over time
What share of full-time undergraduates reported a mental-health difficulty in each survey year?
| Group / measure | percent |
|---|---|
| 2017 | 6.1% |
| 2018 | 8.7% |
| 2019 | 9.6% |
| 2020 | 12.5% |
| 2021 | 11.2% |
| 2022 | 11.8% |
| 2023 | 15.4% |
| 2024 | 17.9% |
| 2025 | 18.9% |
These are self-reported difficulties, not confirmed clinical diagnoses. The change from 17.9% in 2024 to 18.9% in 2025 was not statistically significant. Missing confidence intervals are not estimated.
Reported difficulties by gender
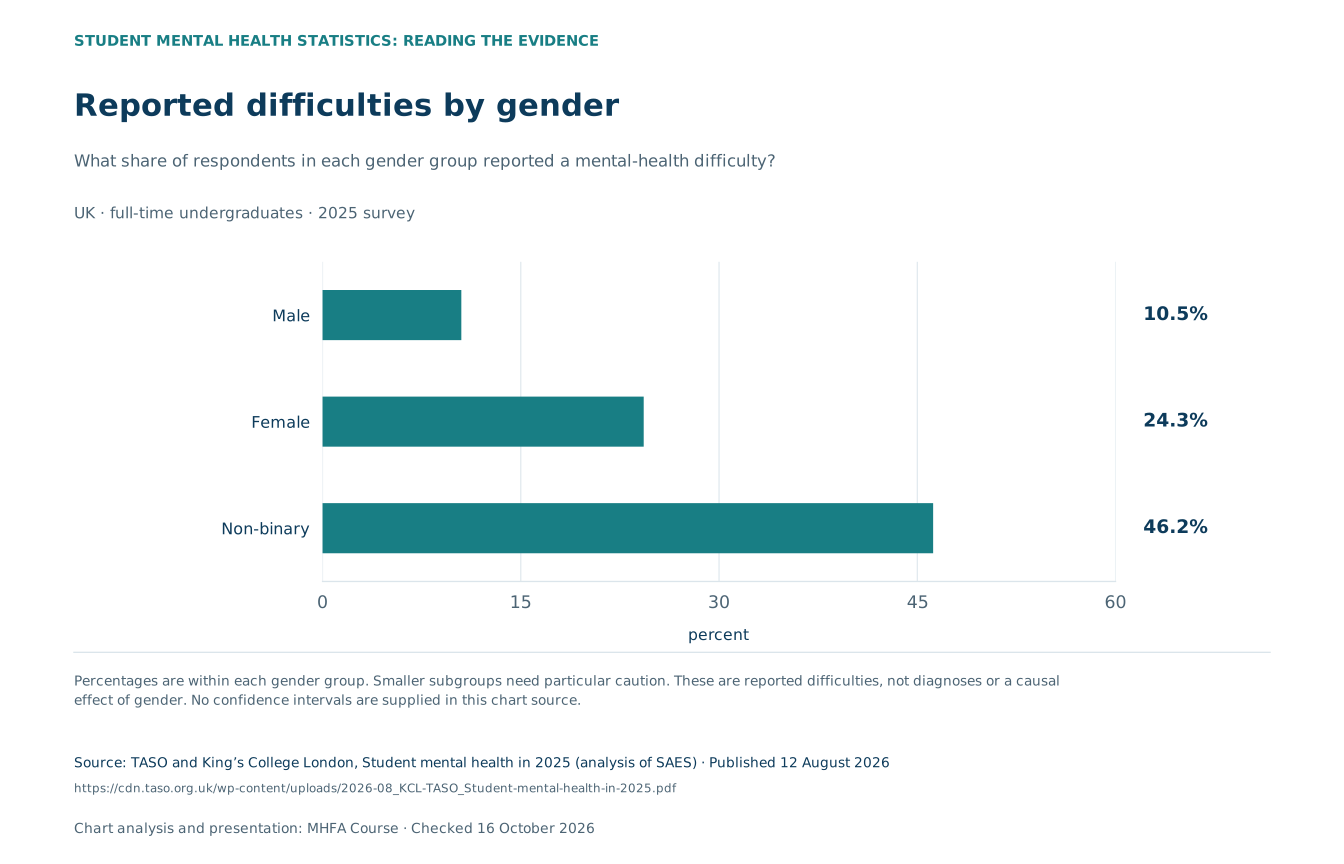
What share of respondents in each gender group reported a mental-health difficulty?
| Group / measure | percent |
|---|---|
| Male | 10.5% |
| Female | 24.3% |
| Non-binary | 46.2% |
Percentages are within each gender group. Smaller subgroups need particular caution. These are reported difficulties, not diagnoses or a causal effect of gender. No confidence intervals are supplied in this chart source.
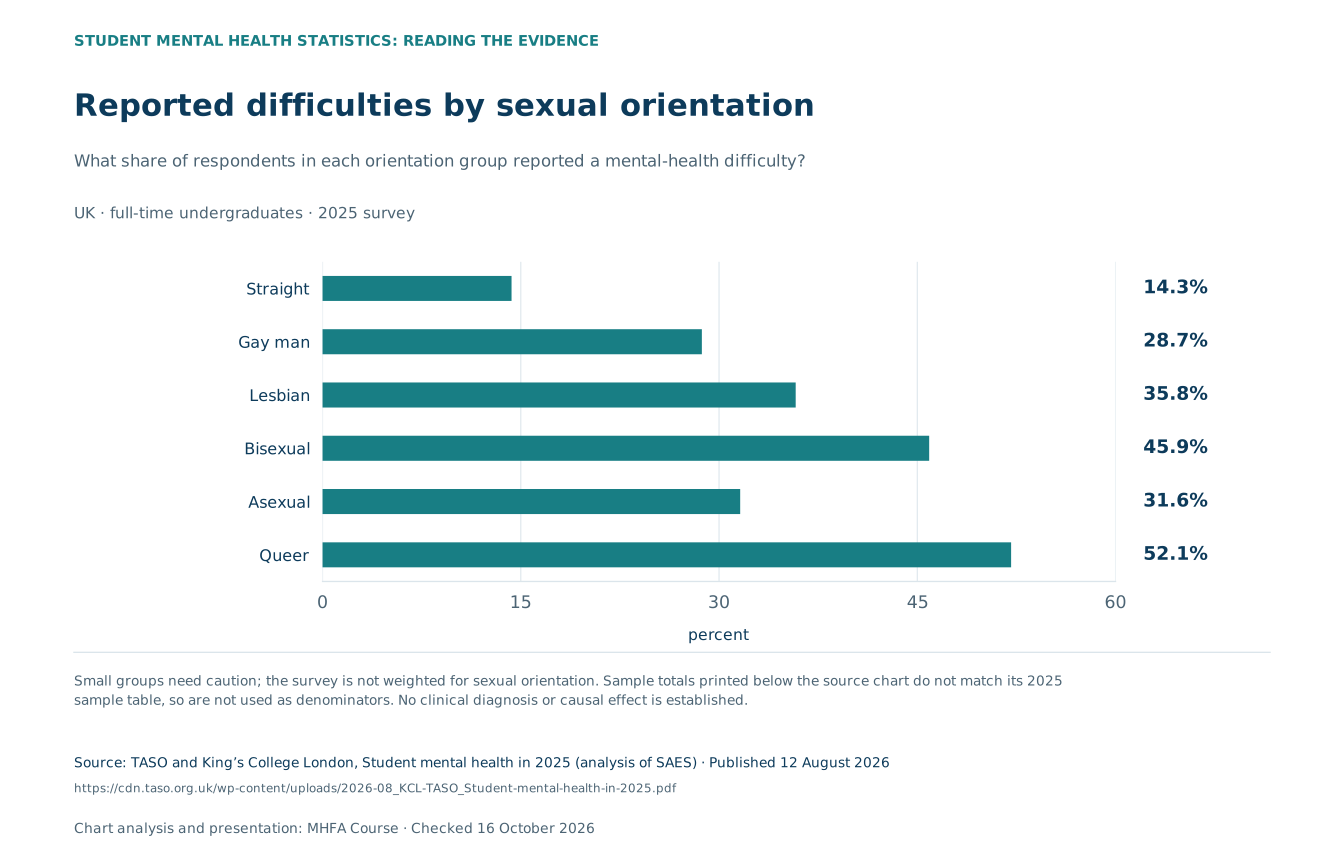
Reported difficulties by sexual orientation
What share of respondents in each orientation group reported a mental-health difficulty?
| Group / measure | percent |
|---|---|
| Straight | 14.3% |
| Gay man | 28.7% |
| Lesbian | 35.8% |
| Bisexual | 45.9% |
| Asexual | 31.6% |
| Queer | 52.1% |
Small groups need caution; the survey is not weighted for sexual orientation. Sample totals printed below the source chart do not match its 2025 sample table, so are not used as denominators. No clinical diagnosis or causal effect is established.
In 2025, reported difficulties were 24.3% among female respondents, 10.5% among male respondents and 46.2% among non-binary respondents. Some subgroups are much smaller than others, so the apparent precision of a percentage should not obscure uncertainty.
By sexual orientation, the reported figures ranged from 14.3% among straight respondents to 52.1% among queer respondents. These comparisons describe survey groups, not inevitable outcomes for individuals. They do not establish that an identity itself causes a mental-health difficulty.
The source’s group categories and published precision are retained in the charts and downloads. Missing confidence intervals are not evidence that an estimate is exact.
Disclosure to a university is a separate measure
In February 2026, the Office for Students reported that more than 85,500 UK full-time undergraduates had a mental-health condition recorded as a disability on their HESA record in 2024/25.
This is an administrative count, not the prevalence of every mental-health difficulty. It has a different definition from the survey’s self-reported difficulty question, and should not be used to calculate how many students’ needs are unmet.
The House of Commons Library’s historical England series reported that the share disclosing a mental-health condition rose from under 1% in 2010/11 to 5.8% in 2022/23.
Disclosure and recording can change alongside students’ experiences. The newer UK count and the older England percentage have different coverage and should not be joined as though they were points in the same series.
Small groups and the published orientation chart
TASO labels the orientation estimates as 2025. Sample totals printed below its chart do not match its 2025 sample table, so they are not used as denominators here.
Some groups are small, and the survey is not weighted for sexual orientation. The report’s 2025 sample table includes 73 queer respondents; that sample count is not assumed to be the exact valid-answer base for the plotted percentage.
The downloads keep the source’s point estimates but leave unverified item bases and numerical confidence intervals blank. The comparison should not be treated as a precise ranking of individual risk.
Everyday pressures need their own context.
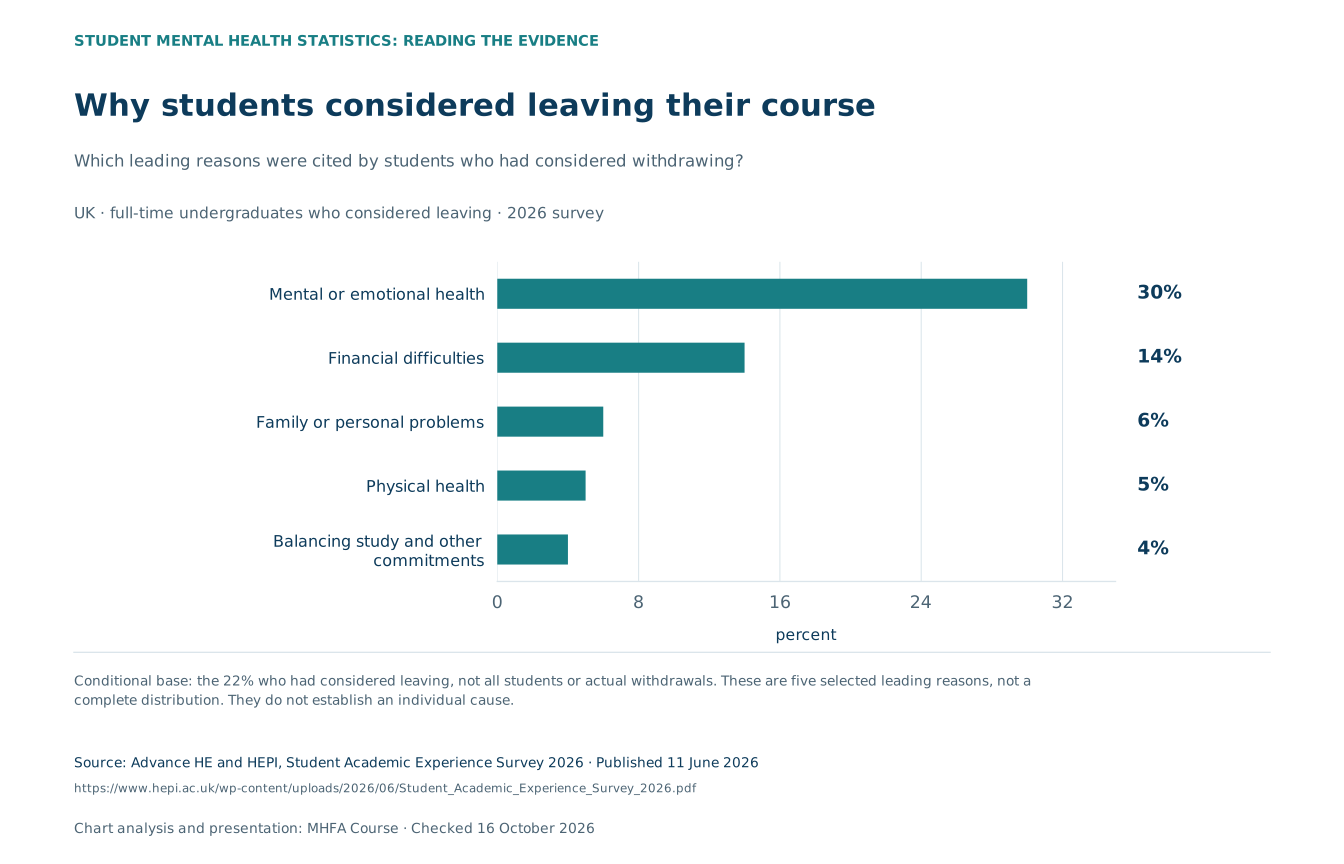
In the 2026 survey, 22% of students had considered leaving their course. The reasons below apply only to those who had considered leaving, not to all students and not to people who actually withdrew.
Mental or emotional health was cited by 30% of this group, followed by financial difficulties at 14%. These are reported reasons for considering withdrawal. They are not a count of diagnosed conditions or a causal estimate of how many students left because of their mental health.
Why students considered leaving their course
Which leading reasons were cited by students who had considered withdrawing?
| Group / measure | percent |
|---|---|
| Mental or emotional health | 30% |
| Financial difficulties | 14% |
| Family or personal problems | 6% |
| Physical health | 5% |
| Balancing study and other commitments | 4% |
Conditional base: the 22% who had considered leaving, not all students or actual withdrawals. These are five selected leading reasons, not a complete distribution. They do not establish an individual cause.
Considering leaving is not the same as leaving.
The five leading reasons shown are a selection, not an exhaustive distribution. Other reasons and response categories are not plotted. Keep the conditional denominator with the chart when reusing it.
A student’s decision can involve several aspects of their life. The findings do not isolate the effect of money, health or family circumstances, and they should not be multiplied by other rounded survey percentages to invent an exact national count.
Practical pressures also matter for students who have not considered leaving. The earlier ONS cost-of-living survey below provides a separate, clearly dated perspective on financial difficulty and perceived changes in wellbeing.
Why familiar student statistics have older dates.
Some widely quoted student mental-health figures come from specific earlier surveys. They remain useful when their dates and limits are visible. They should not be relabelled as current UK student prevalence.
Depression and anxiety screening: first-year students in October 2021
ONS’s experimental survey ran on 4–11 October 2021 among first-year and foundation-year students at universities in England. It found 37% had moderate to severe depressive symptoms and, separately, 39% screened as likely to have an anxiety disorder.
These are two screening results, not a combined depression-or-anxiety percentage and not two groups that can be added. The depression comparison was 22% among adults aged 16–29 in the comparison survey.
The survey took place during the pandemic and had a low response rate. Its findings are not a current estimate for all students or every UK university. They also differ from a reported difficulty or a condition recorded by an institution.
Financial difficulty and wellbeing: January–February 2023
ONS surveyed students at participating universities in England from 30 January to 13 February 2023. 49% reported financial difficulties. Separately, 46% said their mental health and wellbeing had worsened since the start of autumn term 2022.
These are historical experimental findings with a low response rate. They do not establish that money caused poor mental health in a particular share of all students.
Fees, rent and living costs can put pressure on students’ budgets and participation in university life. Fee limits vary with the academic year, provider and course; students should check the applicable fee with their provider. This survey does not, by itself, provide a national count or trend in student food-bank use.
The earlier TASO analysis of LGBTQ+ students
TASO’s report published in February 2025 analysed the 2024 Student Academic Experience Survey. It found that 18% of surveyed UK undergraduates reported a mental-health difficulty.
For the 2023/24 wave, the earlier report found that over half of non-binary respondents and around 40% of trans respondents reported difficulties; these were small subgroups requiring caution. It reported 22% for female respondents and 11% for male respondents in that wave.
Its separate figures of 30% among bisexual respondents and 29% among lesbian respondents pooled survey years 2016/17–2023/24. Those pooled percentages are not single-year 2024 estimates and cannot be compared with the 2025 chart as a like-for-like annual change.
Sexual orientation and gender identity are distinct categories. The findings should not be reduced to one risk multiplier for all LGBTQ+ students, or treated as clinical diagnoses. The survey does not establish the cause of an individual’s difficulties.
Loneliness and depressive symptoms in the wider adult population
In ONS’s April 2025 Great Britain survey, 55% of adults with moderate to severe depressive symptoms felt lonely often, always or some of the time, compared with 16% of those with no or mild symptoms.
This is an adult-population comparison, not a student estimate. The loneliness definition includes “some of the time” but excludes the separate “occasionally” response. The association does not establish which experience caused the other.
Our loneliness statistics guide explains how the different measures relate.
Read the evidence without losing sight of the student.
Student mental-health data can help universities consider support, inclusion and the learning environment. It should complement listening to students rather than replace it.
Making support routes understandable and responding to individual circumstances matter across the range of experiences described here. A student who has not disclosed a condition may still need support; a survey percentage cannot decide what is appropriate for them.
Student suicide: the latest linked-data analysis has a reporting lag
ONS’s analysis published on 9 September 2025 identified 1,108 student suicides in England and Wales from August 2016 to July 2023. For the academic year ending July 2023, it identified 155 deaths, a crude rate of 6.0 per 100,000 higher-education students aged 17 and over.
These are occurrence-period estimates using deaths registered by 31 December 2023. Registration delays mean the most recent occurrence year is incomplete. ONS changed its record-linkage method, so these estimates should not be spliced into older releases as though they form an unchanged series.
Small counts and reporting delays require care when interpreting year-to-year differences. These figures describe a separate outcome; they should not be used to infer an individual student’s risk from a wellbeing score or disclosure status.
The Abrahart judgment and reasonable adjustments
On 14 February 2024, the High Court dismissed the University of Bristol’s appeal in the Abrahart case concerning disability discrimination and reasonable adjustments under the Equality Act 2010.
This was a High Court appeal, not a Court of Appeal ruling. It did not establish a general negligence duty of care. Universities’ legal obligations depend on the relevant law and circumstances; the judgment should not be reduced to a blanket legal claim about every student mental-health situation.
Using student mental health statistics carefully.
How common are mental-health difficulties among UK students?
TASO’s analysis of the 2025 survey found 18.9% of UK full-time undergraduates reported a mental-health difficulty. That is distinct from wellbeing scores, symptom-screening results and conditions disclosed to universities. No single percentage captures all those measures.
Does a reported mental-health difficulty mean a clinical diagnosis?
Not necessarily. The source question determines what counts. A self-report, a questionnaire threshold and an administrative record are different forms of evidence. Read the definition beside each figure.
Why are the depression and anxiety figures still from 2021?
The 37% and 39% findings come from a particular ONS survey of first-year and foundation-year students in England during the pandemic. They are included as historical context, not labelled as the current experience of all students.
Can loneliness or financial pressure be said to cause the reported difficulties?
These surveys can identify reported experiences and associations. They do not establish the direction of causation or explain every individual experience. Nor does occasional loneliness mean someone has no friends.
Why do the student-suicide figures end in 2023?
The latest ONS linked-data analysis was published in September 2025 and covers academic years ending July 2017 to July 2023. Matching education and death records, together with registration delays, creates a reporting lag. The newest occurrence year is incomplete.
Can these figures describe every university or individual student?
No. National findings are useful context, not an assessment of a particular university or student. Different providers and student groups have different circumstances. Individual concerns still need to be heard and addressed.
Methods, uncertainty and reuse
This guide is an original visual presentation of published evidence, not a new survey. The charts retain their source questions, dates and student populations. The downloadable data include source locations and item bases where supplied.
Wellbeing scores, self-reported difficulties, symptom screening and administrative disclosure are kept separate. Multiple responses and overlapping groups are not added. A numerical difference is not automatically statistically significant, and an association is not evidence of causation.
All chart axes begin at zero. Where a source supplies no confidence interval, none is invented. Detailed notes travel with each export so the population and limitations remain available when the chart is reused.
Student mental health charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the question, student population, period and limitations with every figure.
Mental Health First Aid Course (2026). Student Mental Health Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/student-mental-health-statistics
Sources
Primary evidence and methodology. Checked 16 October 2026.
- TASO: Student mental health in 2025 — report and release date
- TASO and King’s College London: Student mental health in 2025 — full report
- TASO: Student mental health in 2024 — historical report and pooled subgroup analysis
- Advance HE and HEPI: Student Academic Experience Survey 2026 — release and methods
- Advance HE and HEPI: Student Academic Experience Survey 2026 — full report
- House of Commons Library: Student mental health in England, April 2025 briefing
- Office for Students: Mental health and disability — February 2026 statement
- HESA: Definitions of student disability and populations
- ONS: First-year students in England, 4–11 October 2021
- ONS: Student cost of living in England, 30 January–13 February 2023
- ONS: Public opinions and social trends in Great Britain, April 2025
- ONS: Suicide among higher education students, August 2016–July 2023
- Courts and Tribunals Judiciary: University of Bristol v Abrahart, February 2024
- Equality and Human Rights Commission: Advice to higher education following Abrahart
- NHS: Student stress