
Loneliness Statistics UK: 2026 Facts, Data & Key Insights
Loneliness statistics UK
Who feels lonely, how we measure it, and what the evidence can tell us about social connection.

Of adults in England said they felt lonely often or always.
England · adults aged 16+CES · May–June 2026
Of adults in Great Britain felt lonely often, always or some of the time.
Great Britain · adults aged 16+ONS · September 2026
Of adults were in the high group on England’s indirect loneliness scale.
England · adults aged 16+CES · May–June 2026 · score 8 or 9
What do loneliness statistics measure?
Loneliness is the distressing feeling that our relationships do not meet our needs. Someone can feel lonely in a busy household or with frequent social contact; another person can enjoy time alone without feeling lonely.
Feeling lonely
A subjective experience of the connection a person wants and the connection they feel they have. A direct survey question asks how often that feeling occurs.
Social isolation
A lack of social relationships, contact or support. It is related to loneliness, but the two are not interchangeable measures.
Being alone
A circumstance that can be chosen or unwanted. Time spent alone does not, by itself, establish that someone is lonely or isolated.
Direct frequency questions distinguish feeling lonely often or always from feeling lonely some of the time. Including the latter category creates a broader measure. Indirect questions ask about experiences such as lacking companionship, feeling left out and feeling isolated.
The question, threshold, population and dates belong with the percentage. A higher figure from a broader measure does not demonstrate that loneliness increased between the two surveys. Neither the England survey nor the Great Britain survey covers the whole UK.
How often do people feel lonely?
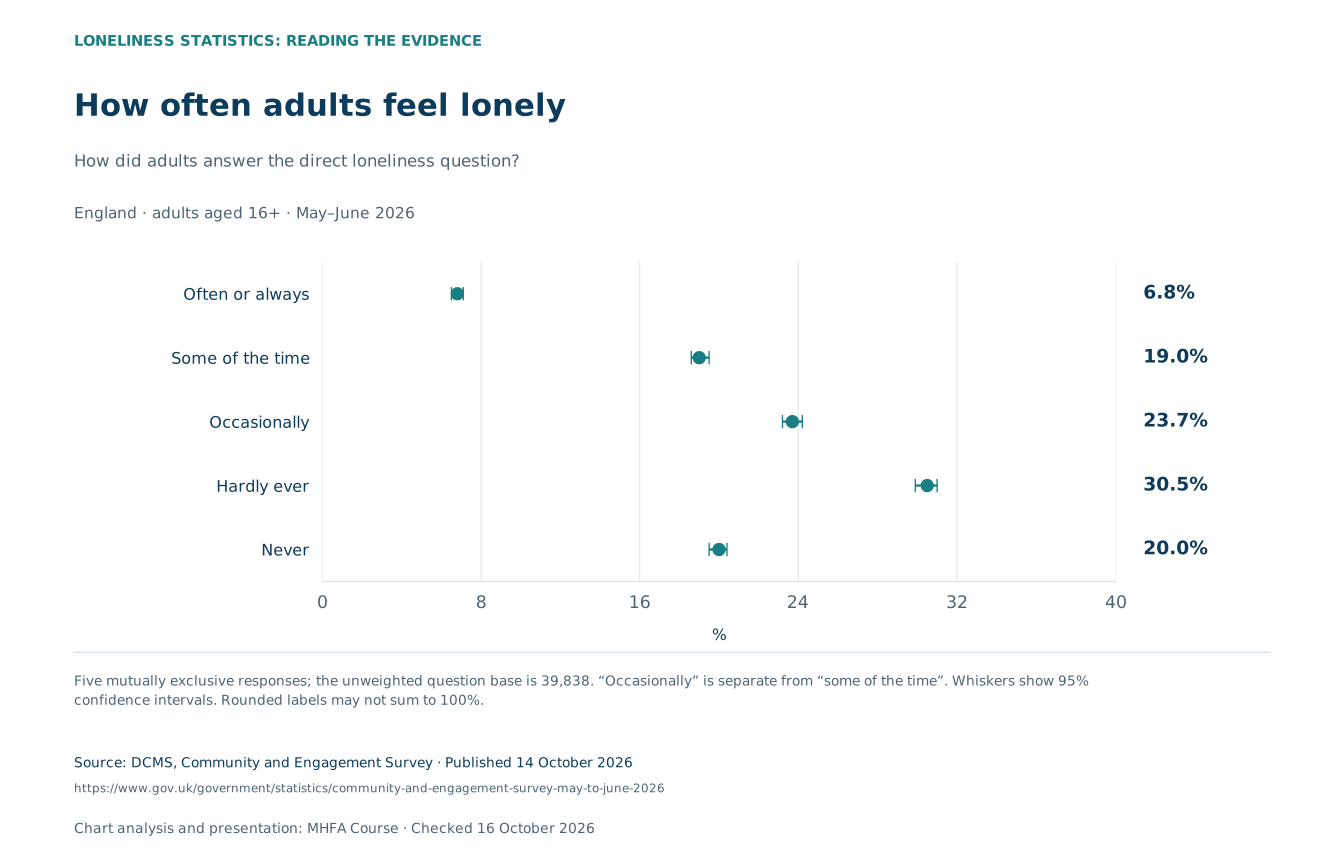
In England’s May–June 2026 Community and Engagement Survey, 6.8% of adults aged 16 and over said they felt lonely often or always. The question had an unweighted response base of 39,838.
The latest distribution below keeps each frequency response separate. The annual chart that follows uses its own periods; the May–June observation is not appended to that series as though it were a full year.
How often adults feel lonely
How did adults answer the direct loneliness question?
| Group / measure | % | 95% interval |
|---|---|---|
| Often or always | 6.8% | 6.5–7.1% |
| Some of the time | 19% | 18.6–19.5% |
| Occasionally | 23.7% | 23.2–24.2% |
| Hardly ever | 30.5% | 29.9–31% |
| Never | 20% | 19.5–20.4% |
Five mutually exclusive responses; the unweighted question base is 39,838. “Occasionally” is separate from “some of the time”. Whiskers show 95% confidence intervals. Rounded labels may not sum to 100%.
Frequent loneliness over time
What share of adults said they felt lonely often or always?
survey22/23
| Group / measure | % | 95% interval |
|---|---|---|
| 2018/19 | 6.1% | 5.6–6.7% |
| 2019/20 | 6.4% | 5.9–7% |
| 2020/21 | 6.5% | 5.9–7.1% |
| 2021/22 | 6.2% | 5.7–6.9% |
| 2023/24 | 7.1% | 6.9–7.3% |
| 2024/25 | 6.6% | 6.4–6.7% |
| 2025/26 | 6.7% | 6.6–6.9% |
No survey was conducted in 2022/23. CES succeeds CLS in 2025/26; DCMS retains the community methodology and considers the estimates comparable. Recent releases cover October–March; earlier fieldwork periods differ. Whiskers show 95% confidence intervals.
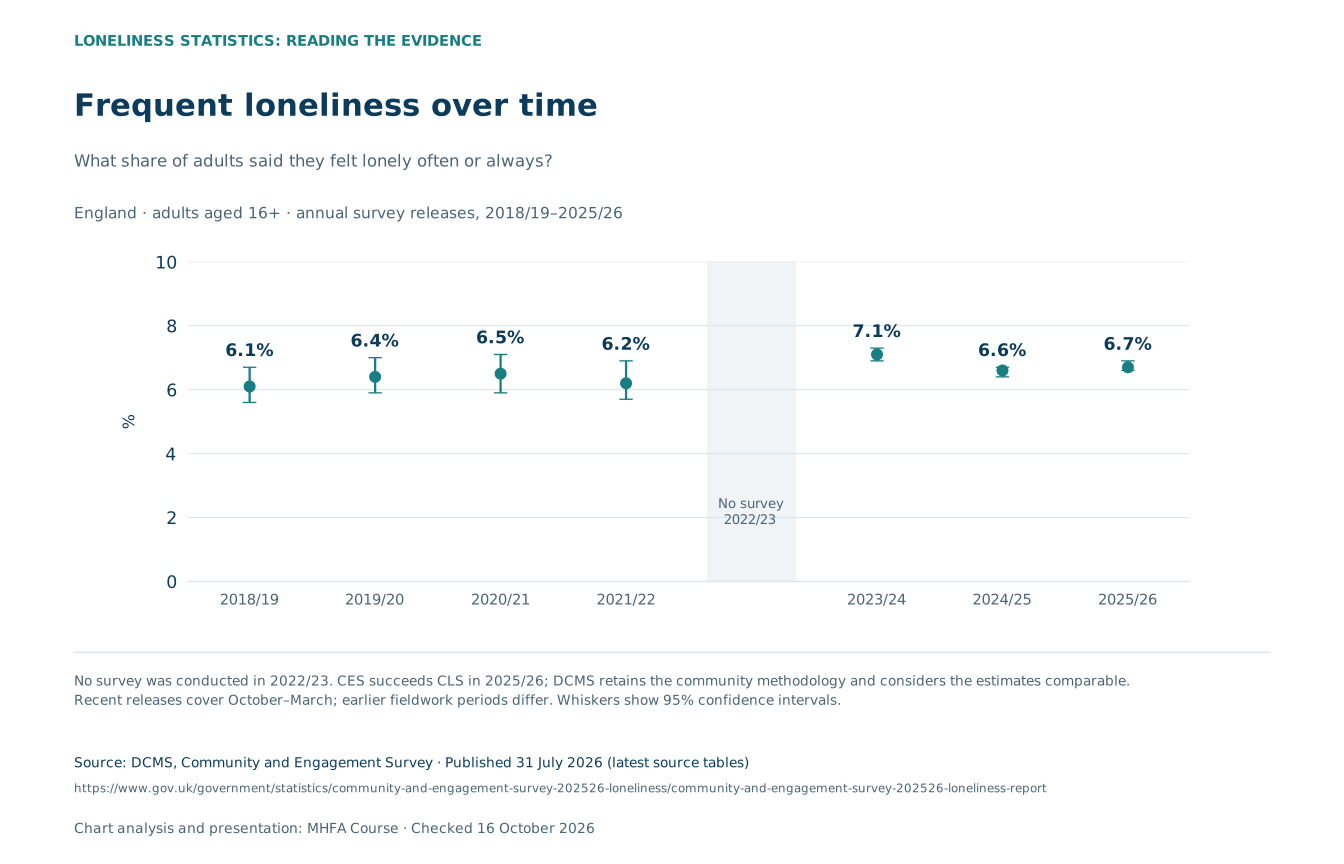
In the latest annual England survey, 7% felt lonely often or always, which was not statistically different from 7% in 2024/25. It also found that 20% said they never felt lonely. These are rounded annual headlines; chart labels use one decimal where supported.
A rounded percentage staying the same is not proof that every group or individual had the same experience. The release does not provide a comparable prior-year quarterly estimate.
The newer Great Britain figure uses a broader threshold
In the ONS September 2026 survey, 25% of adults felt lonely often, always or some of the time, with a 95% confidence interval of 23%–27%. Of all adults, 7% reported often or always and 18% reported some of the time. The broader measure does not include the separate “occasionally” response.
The question’s rounded unweighted base was 3,640. These are weighted estimates for adults aged 16+ in Great Britain, not a count of respondents or an England-only annual estimate.
The earlier April 2025 survey reported 24% on the broader measure. The two rounded headlines alone do not establish a statistically significant change.
Why the indirect scale gives a different result
England’s indirect loneliness scale combines three questions about companionship, exclusion and isolation. Scores range from 3 to 9. In May–June 2026, 8.6% were in the high-loneliness group, scoring 8 or 9. The latest annual 2025/26 release reported a rounded 9%.
The direct and indirect measures can describe some of the same people. Their percentages should not be added, subtracted to identify a hidden group, or treated as competing estimates using an identical definition.
Loneliness across adult age groups.
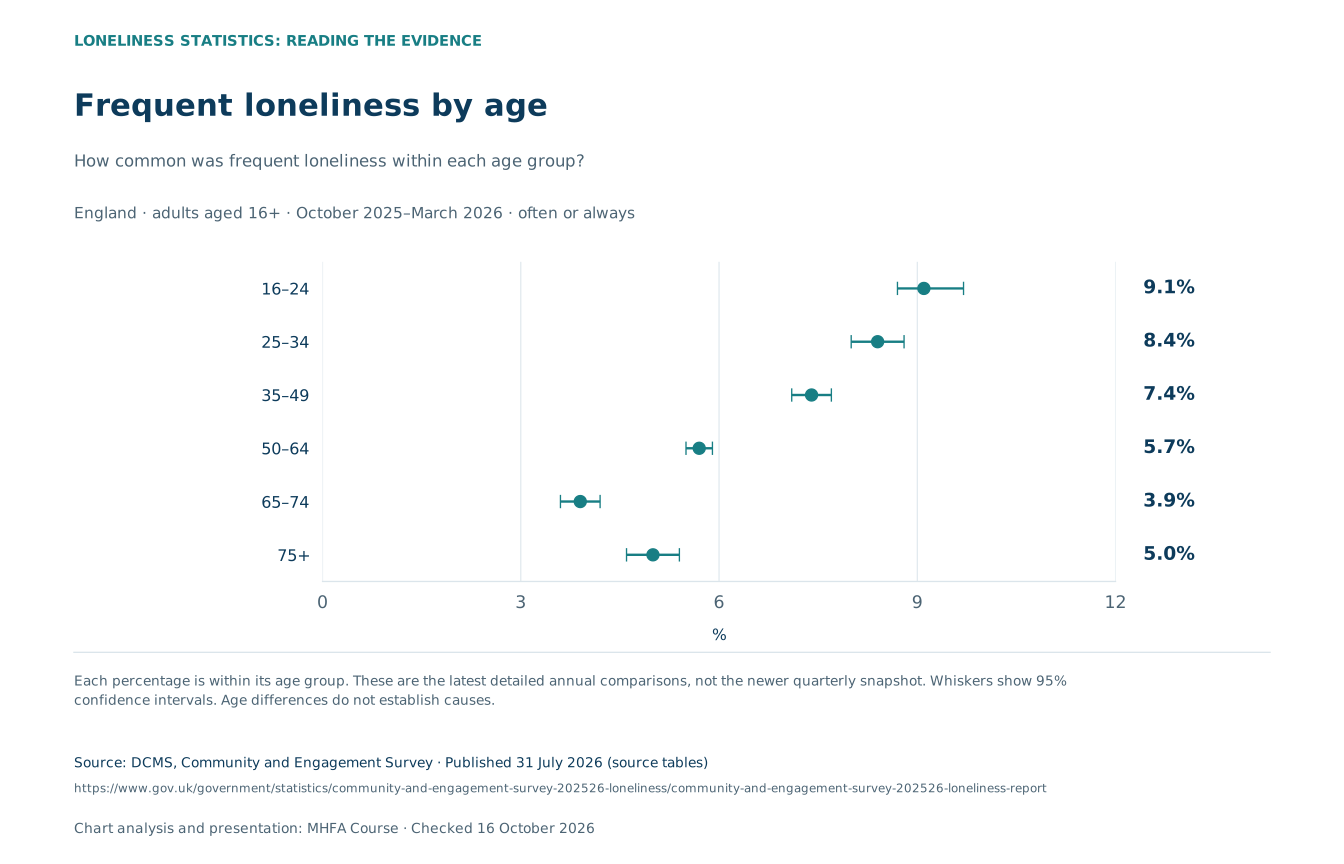
Loneliness is not confined to older people. In England’s 2025/26 survey, 9% of adults aged 16–24 felt lonely often or always, compared with 4% aged 65–74 and 5% aged 75 and over.
The chart compares the same frequency threshold within each age group. It does not show each group’s share of everyone who feels lonely.
Frequent loneliness by age
How common was frequent loneliness within each age group?
| Group / measure | % | 95% interval |
|---|---|---|
| 16–24 | 9.1% | 8.7–9.7% |
| 25–34 | 8.4% | 8–8.8% |
| 35–49 | 7.4% | 7.1–7.7% |
| 50–64 | 5.7% | 5.5–5.9% |
| 65–74 | 3.9% | 3.6–4.2% |
| 75+ | 5% | 4.6–5.4% |
Each percentage is within its age group. These are the latest detailed annual comparisons, not the newer quarterly snapshot. Whiskers show 95% confidence intervals. Age differences do not establish causes.
What the Great Britain age figures measure
The separate ONS September 2026 survey used the broader often, always or some-of-the-time threshold. It found 38% among adults aged 16–29, 24% aged 30–49, 23% aged 50–69 and 17% aged 70+.
The April 2025 survey had reported 31% among those aged 16–29 on that broader measure. These figures have different dates and age bands from the England chart. The estimates do not establish that social media or any single social change caused an age difference.
Loneliness can matter at any age
Leaving home, moving area, bereavement, illness or starting university can affect relationships. NHS guidance recognises these as circumstances in which people may experience loneliness.
Moving to university can bring loneliness even when a student has frequent contact with others. Student services or a students’ union may offer support. General population age-group percentages should not be relabelled as university-student prevalence.
Differences between population groups.
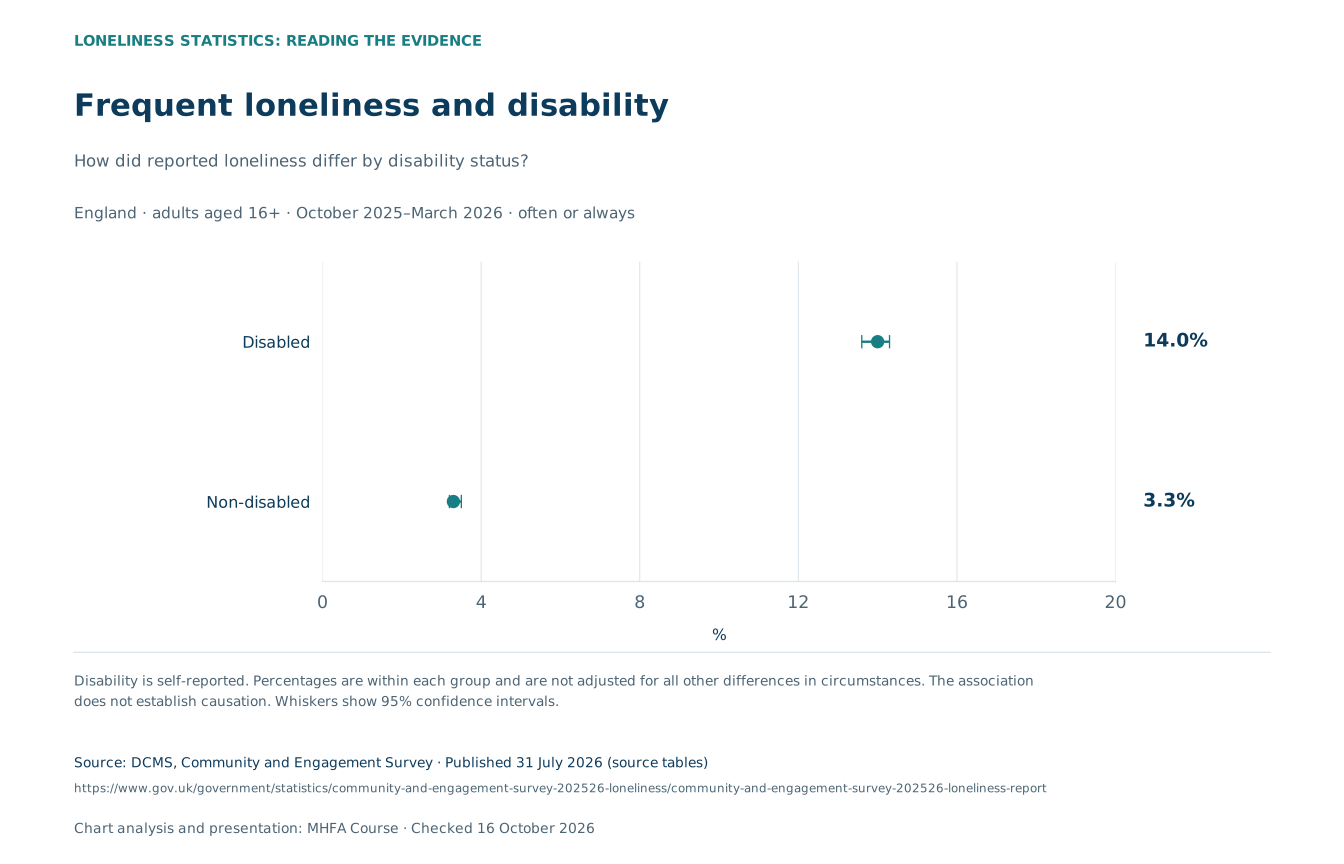
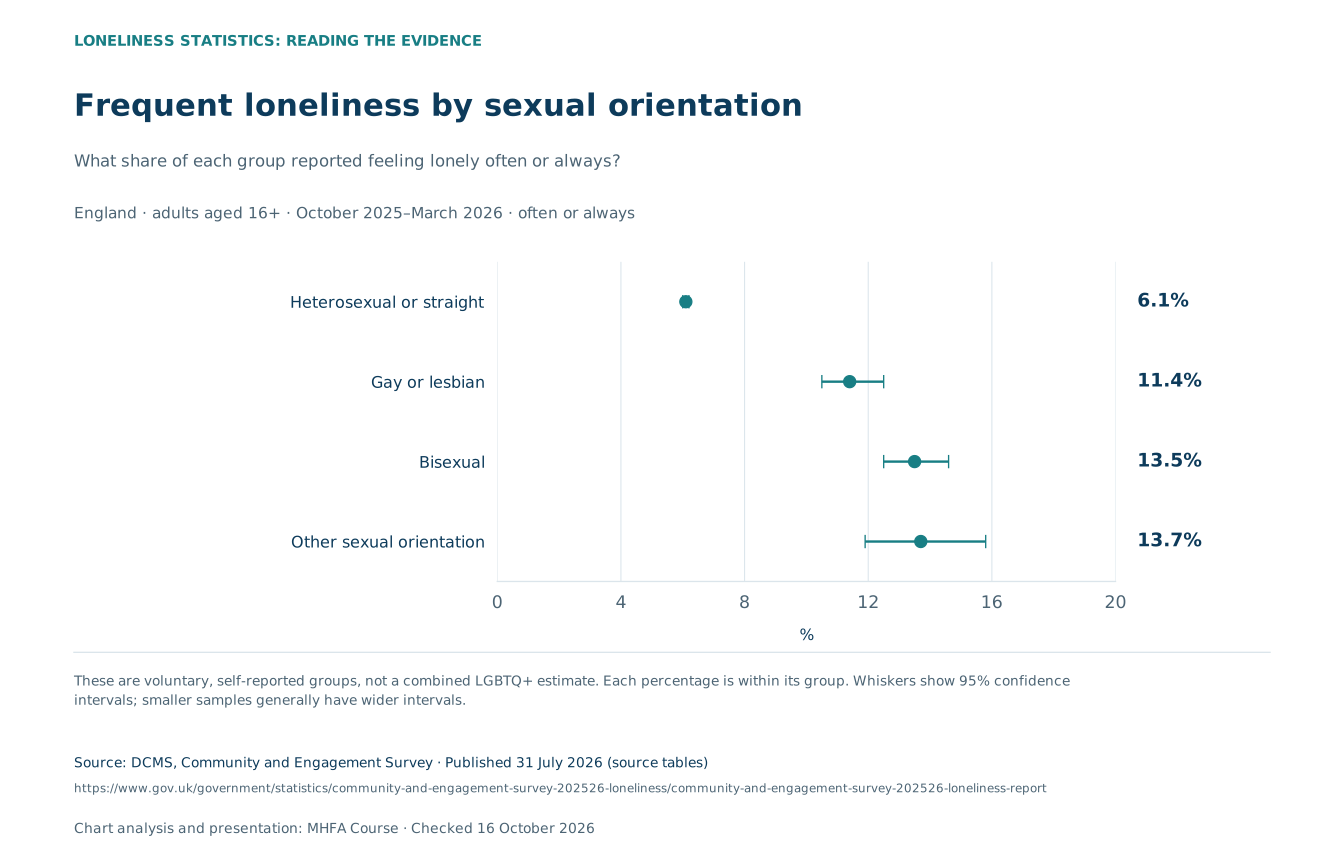
England’s survey shows differences in loneliness by disability and sexual orientation. These are population-level associations, not proof that a characteristic causes loneliness or a prediction about an individual.
Using the same question and reference period makes the comparisons easier to interpret. It does not remove the effects of other differences in circumstances, health or access to support.
Frequent loneliness and disability
How did reported loneliness differ by disability status?
| Group / measure | % | 95% interval |
|---|---|---|
| Disabled | 14% | 13.6–14.3% |
| Non-disabled | 3.3% | 3.2–3.5% |
Disability is self-reported. Percentages are within each group and are not adjusted for all other differences in circumstances. The association does not establish causation. Whiskers show 95% confidence intervals.
Frequent loneliness by sexual orientation
What share of each group reported feeling lonely often or always?
| Group / measure | % | 95% interval |
|---|---|---|
| Heterosexual or straight | 6.1% | 6–6.2% |
| Gay or lesbian | 11.4% | 10.5–12.5% |
| Bisexual | 13.5% | 12.5–14.6% |
| Other sexual orientation | 13.7% | 11.9–15.8% |
These are voluntary, self-reported groups, not a combined LGBTQ+ estimate. Each percentage is within its group. Whiskers show 95% confidence intervals; smaller samples generally have wider intervals.
14% of disabled adults reported feeling lonely often or always, compared with 3% of non-disabled adults. Barriers to social participation and support needs vary between individuals.
The corresponding estimates were 14% for bisexual adults, 11% for gay or lesbian adults and 6% for heterosexual adults. These describe reported loneliness, not a direct measure of access to community opportunities.
Caring responsibilities and opportunities for connection
Unpaid caring can limit the time and opportunities available for social participation and paid work. Carers UK’s State of Caring research describes how caring responsibilities can affect social connection.
A survey of carers provides useful accounts of their experiences, but it should not be treated as a representative prevalence estimate for all adults. Support needs depend on the person’s responsibilities, resources and preferences.
Domestic abuse can include controlling contact with friends and family, restricting access to support. A person’s safety and preferences should guide any attempt to help them reconnect. Simply encouraging more contact is not an adequate response to abuse.
Loneliness and depressive symptoms.
In the ONS survey for 2–27 April 2025, 55% of adults with moderate or severe depressive symptoms felt lonely often, always or some of the time. The estimate was 16% among those with no or mild symptoms.
This is a Great Britain comparison using a broader loneliness threshold than the England charts. The symptom categories come from a screening questionnaire, not a record of confirmed clinical diagnoses.
Loneliness and depressive symptoms
How common was loneliness within each symptom-screening group?
| Group / measure | % | 95% interval |
|---|---|---|
| Moderate or severe symptoms | 55% | 49–61% |
| No or mild symptoms | 16% | 15–18% |
The loneliness threshold excludes “occasionally”. PHQ-8 symptoms cover the previous two weeks; screening groups are not diagnoses. This association does not establish cause or direction. Whiskers show 95% confidence intervals.
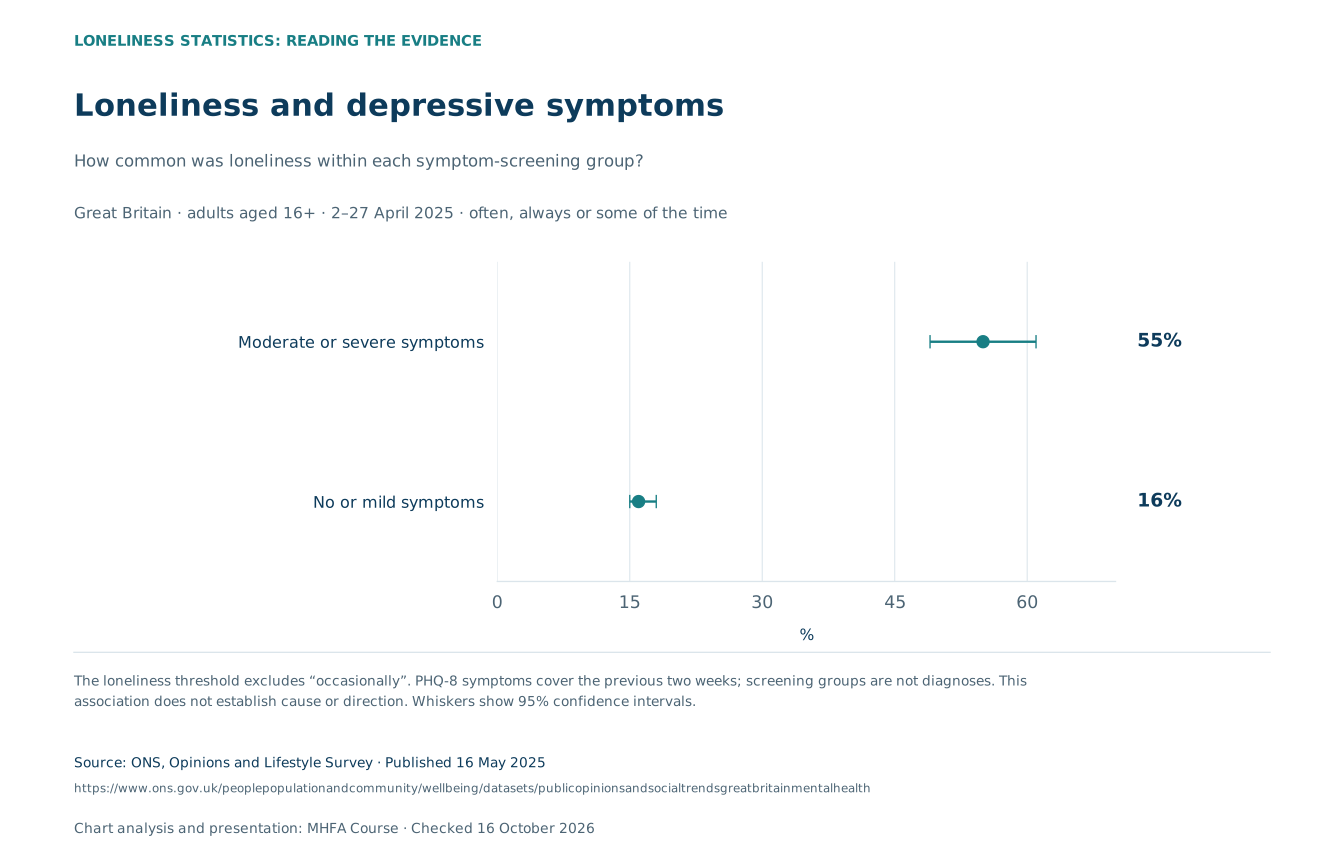
Loneliness and mental-health difficulties can reinforce one another. NHS and WHO guidance describe relationships with depression and anxiety, but this survey comparison cannot establish which came first or what caused either experience.
The percentages are the prevalence of reported loneliness within each depressive-symptom group. They are not the proportion of lonely adults with depression.
April 2025 remains the latest available dedicated ONS module linking loneliness with PHQ-8 depressive symptoms. Newer overall loneliness results cover September 2026, but do not replace this symptom-group comparison.
Persistent loneliness deserves attention at any age. Its effects depend on a person’s health, circumstances and available support. These national surveys do not provide a male-specific suicide-risk estimate or predict what will happen to an individual.
People experiencing trauma or other mental-health difficulties may find social contact harder. Support should fit the person rather than assume that everyone with a particular diagnosis is isolated or that social contact alone is sufficient treatment.
Connection, health and individual support.
WHO’s 2025 Commission on Social Connection report estimated that about one in six people globally experienced loneliness, using evidence from 2014–2023. This is international evidence across that period, not a current UK survey percentage.
The report links loneliness and social isolation with poorer health and premature mortality. These are related but distinct experiences. Comparing loneliness with a fixed number of cigarettes obscures differences in exposure and research methods and does not provide an individual health-risk calculation.
What the global estimate of 871,000 deaths means
WHO estimated 871,000 deaths a year attributable to loneliness worldwide using a population-level model for 2014–2019. It is not a count of death certificates identifying loneliness, a UK death count or an estimate of NHS costs.
The estimate depends on the underlying evidence and modelling assumptions. It supports attention to social connection as a public-health issue without predicting what will happen to any individual.
Support starts with the person’s experience
More contact is not automatically the same as a stronger sense of connection. Listening to what someone wants, recognising barriers and considering the support available can be more useful than assuming one activity will suit everyone.
Bereavement, illness, changes in mobility and relationships can matter at any age. NHS guidance on loneliness offers practical options, and people at university can also explore support through student services or their students’ union.
Reading and using loneliness statistics.
How many people in the UK are lonely?
The main datasets here cover England or Great Britain, with different questions and periods. They do not provide a single comparable UK total. The population and frequency threshold should always accompany a percentage.
Why do the headlines say both 6.8% and 25%?
The England figure is the share who felt lonely often or always in May–June 2026. The September 2026 Great Britain figure also includes people who felt lonely some of the time. The thresholds, geography and dates differ.
Does loneliness mostly affect older people?
Loneliness can affect people at any age. England’s 2025/26 survey recorded a higher often-or-always estimate among young adults than among the two oldest age groups. This does not mean older people’s needs are unimportant or that age alone explains the difference.
Is loneliness the same as social isolation?
No. Loneliness concerns how someone feels about the connection they have. Social isolation concerns a lack of relationships, contact or support. Someone may experience either, both or neither.
Does the mental-health comparison prove loneliness causes depression?
No. The April 2025 survey shows an association between loneliness and depressive-symptom screening groups. It does not establish the direction of the relationship, explain every influence or provide a clinical diagnosis.
Why are some figures older than the review date?
Publication dates, survey periods and the timing of individual questions differ. The latest ONS overall loneliness data cover September 2026, while April 2025 remains the latest available dedicated ONS module linking loneliness with PHQ-8 depressive symptoms. The England and global research use their own clearly stated periods.
Methods, uncertainty and reuse
This guide presents published evidence in a new visual format. It is not a new survey, a diagnostic tool or a calculation of an individual’s health risk.
Direct frequency questions and indirect scales measure related but different experiences. Comparisons should keep the question, threshold, geography, age group and period consistent. Different percentages must not be combined into a single loneliness total.
Published confidence intervals are shown where available. They describe sampling uncertainty; they do not capture every limitation of survey participation, recall, interpretation or design. A rounded difference is not automatically statistically significant.
Charts start at zero. Tables and CSV downloads preserve source values, periods, bases and locators. Keep the source definitions and limitations with the figures when sharing them.
Loneliness charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the question, threshold, population and period with every figure. Different loneliness measures answer different questions.
Mental Health First Aid Course (2026). Loneliness Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/loneliness-statistics-uk
Sources
Primary evidence and methodology. Checked 16 October 2026.
- DCMS: latest quarterly CES results, May–June 2026Published 14 October 2026.
- DCMS: quarterly source data tablesPublished 14 October 2026.
- DCMS: quarterly technical report and fieldwork datesPublished 14 October 2026.
- DCMS: annual loneliness results 2025/26Published 14 August 2026.
- DCMS: annual loneliness source data tablesPublished 31 July 2026.
- DCMS: Community Life Survey 2024/25 and historical trendPublished 10 December 2025.
- DCMS: Community Life Survey historical source tablesPublished 10 December 2025.
- DCMS: methodology and comparabilityPublished 11 August 2026.
- DCMS: interpreting the statisticsPublished 11 August 2026.
- ONS: latest GB loneliness, September 2026Published 16 October 2026.
- ONS: September 2026 source workbookPublished 16 October 2026.
- ONS: April 2025 mental-health and loneliness modulePublished 16 May 2025.
- ONS: April 2025 source workbookPublished 16 May 2025.
- ONS: national loneliness measurement guidance
- WHO: Commission on Social Connection reportPublished 30 June 2025.
- WHO: global report plain-language summaryPublished 30 June 2025.
- WHO: social connection questions and answersPublished 30 June 2025.
- NHS: dealing with loneliness
- NHS: feeling lonely and available support
- NHS: recognising domestic abuse and offering support
- Carers UK: original State of Caring 2025 researchPublished 21 October 2025.