
Veterans Mental Health Statistics UK: 2026 Facts, Data & Key Insights
Veterans mental health statistics UK
Understanding health after service, from cohort research to everyday support—and why the people behind each figure matter.

screened positive for probable PTSD
A defined Phase 4 cohort, not every UK veteran or a clinical diagnosis register.screened positive for common mental disorder
An overlapping symptom-screening measure. Different questionnaire items have different valid-response bases.veterans aged 16 or over in the ONS population estimate
Published 13 October 2026. Developing administrative statistics; this is not a mental-health count.Veterans are not one uniform group.
Veterans differ in age, service history, length of service, deployment experiences and the time since leaving. Most veterans do not have PTSD, while some groups have substantial needs for support.
The King’s Centre for Military Health Research (KCMHR) cohort includes serving and ex-serving respondents. It is not a random survey of every UK veteran. Findings for former Regular personnel should not be treated as estimates for all veterans, all former reservists or every service generation.
Probable PTSD and common mental-health conditions in cohort questionnaires are screening measures. A questionnaire threshold is different from a diagnosis made through clinical assessment, and different instruments can yield different estimates.
A defined group
A military cohort can include serving and ex-serving people with particular service histories. Its estimates do not automatically describe every UK veteran.
Screening and diagnosis
Symptoms meeting a questionnaire threshold are different from an individually assessed clinical diagnosis. Questionnaires and timeframes also differ between studies.
Different records
Population counts, deaths, healthcare contacts and treatment outcomes have separate definitions. They should not be combined into an unsupported rate.
What the new veteran population estimate counts
ONS estimated 1.481 million veterans aged 16 or over living in England and Wales at 30 June 2025. The release was published on 13 October 2026.
These are official statistics in development, based on linked census, service-leaver and population records. Coverage limitations probably underestimate the population. The estimates are not directly comparable with Census 2021 because of deaths, excluded imputed veteran status and incomplete linkage.
This is an England-and-Wales population estimate, not a UK total or a mental-health figure. Multiplying a selected cohort’s symptom percentage by this population count would not produce a defensible number of affected veterans.
Who took part in Phase 4?
The legacy cohort concerns the Iraq and Afghanistan service era and includes people who did not deploy. Phase 4 followed earlier participants who had consented to recontact; it did not add a new replenishment sample.
There were 4,104 responses, with a 54.6% response rate. Sampling and differential-response weights were applied. Loss to follow-up and selection still limit how far the results can be extended to other veterans.
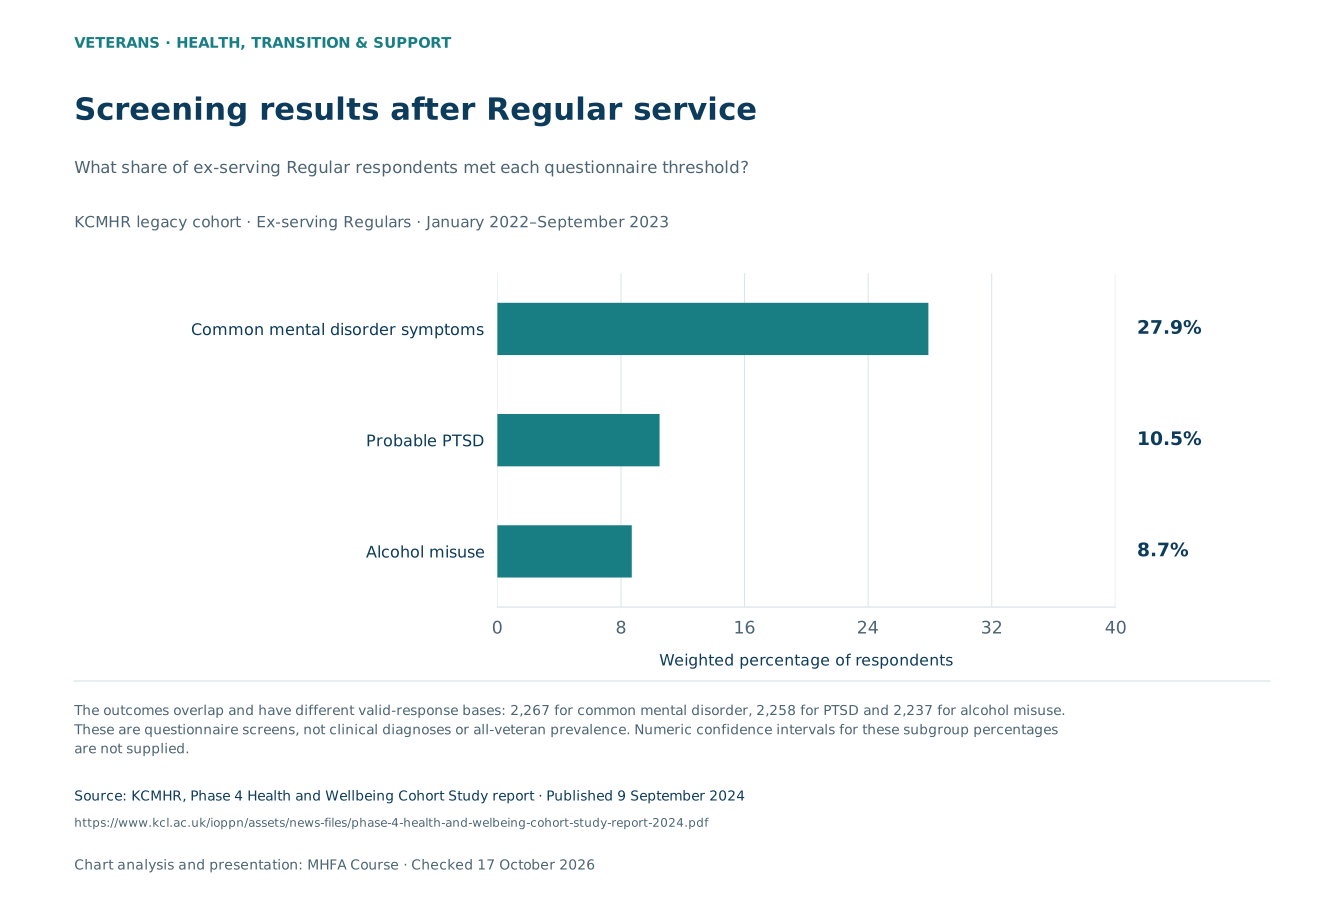
The whole cohort, including serving and ex-serving Regular and Reserve participants, had weighted estimates of 27.8% for common mental disorder symptoms, 9.4% for probable PTSD and 8.4% for alcohol misuse. These differ from the ex-serving Regular subgroup shown in the first chart.
What symptoms were measured after service?
The Phase 4 findings describe symptom patterns in a defined military cohort. They should be read with their service-status categories, questionnaires and survey dates.
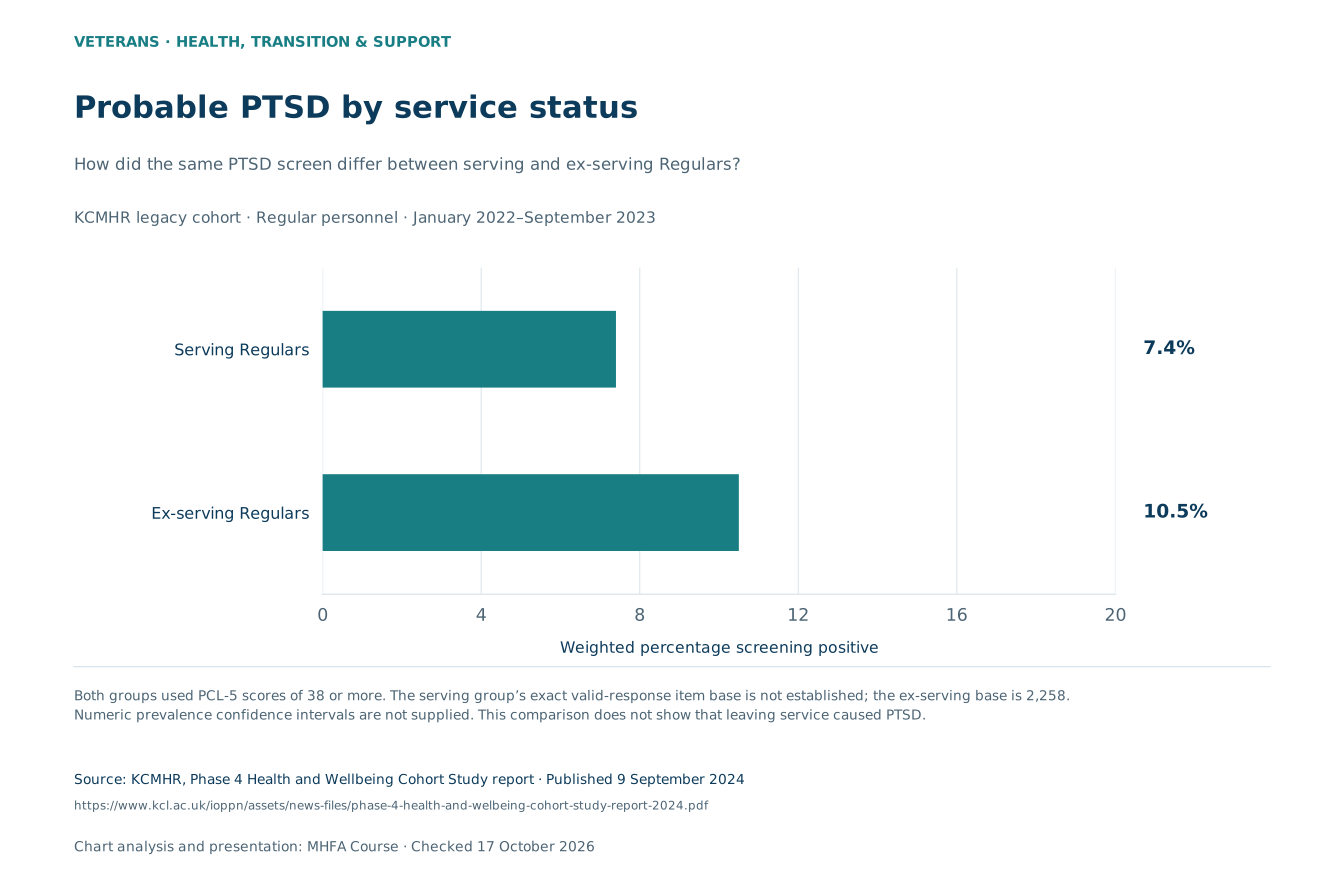
The earlier 2024 report described probable PTSD in around 9% of 4,104 serving and ex-serving respondents, with rounded figures of 11% for ex-serving Regular personnel and 7% for serving Regulars. It also reported symptoms of common mental disorder in around 28% of respondents.
The charts use exact table values from the Phase 4 report and the subsequent peer-reviewed analysis of that research wave. Rounded report figures and later table estimates should not be interpreted as a new annual change.
Screening results after Regular service
What share of ex-serving Regular respondents met each questionnaire threshold?
| Group / measure | percent |
|---|---|
| Common mental disorder symptoms | 27.9% |
| Probable PTSD | 10.5% |
| Alcohol misuse | 8.7% |
The outcomes overlap and have different valid-response bases: 2,267 for common mental disorder, 2,258 for PTSD and 2,237 for alcohol misuse. These are questionnaire screens, not clinical diagnoses or all-veteran prevalence. Numeric confidence intervals for these subgroup percentages are not supplied.
Probable PTSD by service status
How did the same PTSD screen differ between serving and ex-serving Regulars?
| Group / measure | percent |
|---|---|
| Serving Regulars | 7.4% |
| Ex-serving Regulars | 10.5% |
Both groups used PCL-5 scores of 38 or more. The serving group’s exact valid-response item base is not established; the ex-serving base is 2,258. Numeric prevalence confidence intervals are not supplied. This comparison does not show that leaving service caused PTSD.
Why a general-population comparison needs care
Military cohort participants and general-population household-survey respondents differ in recruitment, age, sex, service history and other characteristics. PTSD questionnaires, symptom thresholds and reference periods may also differ.
A simple ratio between the cohort result and an APMS screening percentage would therefore be misleading. Neither figure can establish whether a particular veteran has PTSD or should seek a clinical assessment.
Symptoms and functioning can change over time. Screening results are useful research measures, but they do not show that every person who crosses a threshold has a recorded diagnosis or that everyone below it is free of difficulty.
What each screening threshold means
The report uses a GHQ-12 score of 4 or more for common mental disorder symptoms, a PCL-5 score of 38 or more for probable PTSD and an AUDIT score of 16 or more for alcohol misuse. The alcohol threshold is higher than that used in many hazardous-drinking surveys.
The selected tables do not restate a single shared recall window for the three instruments. They should not be presented as three measures of past-year diagnosis. Outcomes can overlap, and the valid-response bases differ.
The percentages are weighted, while the reported numbers of respondents are unweighted. Dividing an unweighted numerator by its unweighted base will not necessarily reproduce the published percentage.
A comparison does not explain every individual outcome.
Serving status, deployment history and combat roles are associated with different experiences. Those associations do not by themselves show that leaving service or any single experience caused a mental-health condition.
The cohort report found higher probable PTSD among people who had deployed in combat roles than combat-support roles. Earlier 17% versus 6% figures came from previous research among ex-serving Regular personnel; they are not current rates for all veterans.
Potential influences include earlier vulnerability, age, service experiences and circumstances after leaving. The available measures do not capture every relevant difference between comparison groups.
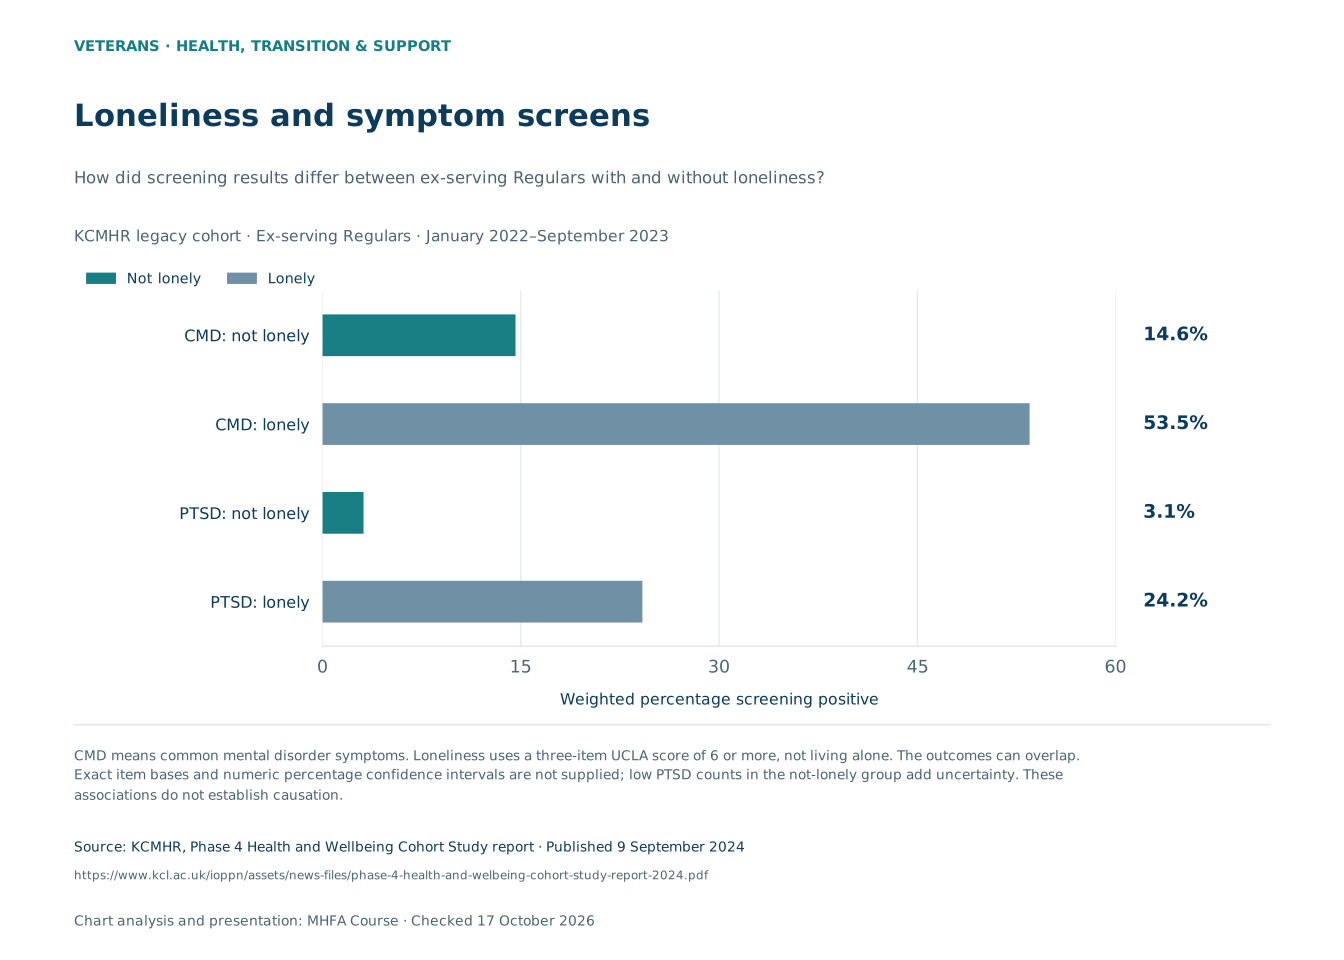
The cohort also asks about loneliness. The comparison below groups ex-serving Regulars by reported loneliness and shows the proportions screening positive for common mental disorder or probable PTSD. It is an association, not evidence that loneliness alone caused those symptoms or that one social intervention would remove them.
Loneliness and symptom screens
How did screening results differ between ex-serving Regulars with and without loneliness?
| Group / measure | percent |
|---|---|
| CMD: not lonely | 14.6% |
| CMD: lonely | 53.5% |
| PTSD: not lonely | 3.1% |
| PTSD: lonely | 24.2% |
CMD means common mental disorder symptoms. Loneliness uses a three-item UCLA score of 6 or more, not living alone. The outcomes can overlap. Exact item bases and numeric percentage confidence intervals are not supplied; low PTSD counts in the not-lonely group add uncertainty. These associations do not establish causation.
Selected groups are not all veterans.
A study of trauma-exposed people, deployed personnel or specialist-service patients describes that group. Its results should not be presented as the national prevalence of a condition among all former service personnel.
Association is not an individual prediction.
A group difference cannot determine a person’s future health or explain all their symptoms. Individual assessment should consider their current needs, functioning and circumstances.
What the loneliness comparison measures
The three-item UCLA scale asks about lack of companionship, feeling left out and feeling isolated. The report classifies scores of 6 or more as lonely. It is a different measure from a direct question about how often someone feels lonely.
The source lists 1,500 respondents in the not-lonely group and 683 in the lonely group. These are whole-group counts, not established valid-response denominators for every symptom item. The downloads keep them as separate sample context.
Mental-health difficulties and loneliness may influence one another and share other causes. The comparison cannot establish the direction of influence or estimate the effect of a support programme.
Reading veteran-suicide evidence carefully.
Suicide evidence requires a clear distinction between the population followed, deaths occurring in a year and deaths registered by a specified date.
The NCISH study published in August 2023 linked records for around 458,000 people who left the UK Regular Armed Forces during 1996–2018. It identified 1,086 subsequent suicide deaths during follow-up. The study linked deaths in England, Scotland and Wales; Northern Ireland was excluded because the necessary death data were not available. It does not represent every generation of veterans or all former reservists.
The overall male standardised mortality ratio was 93.5 (approximately 94) against a general-population reference of 100. That point estimate was slightly lower, but it does not mean every subgroup had low risk or prove that military service protects against suicide.
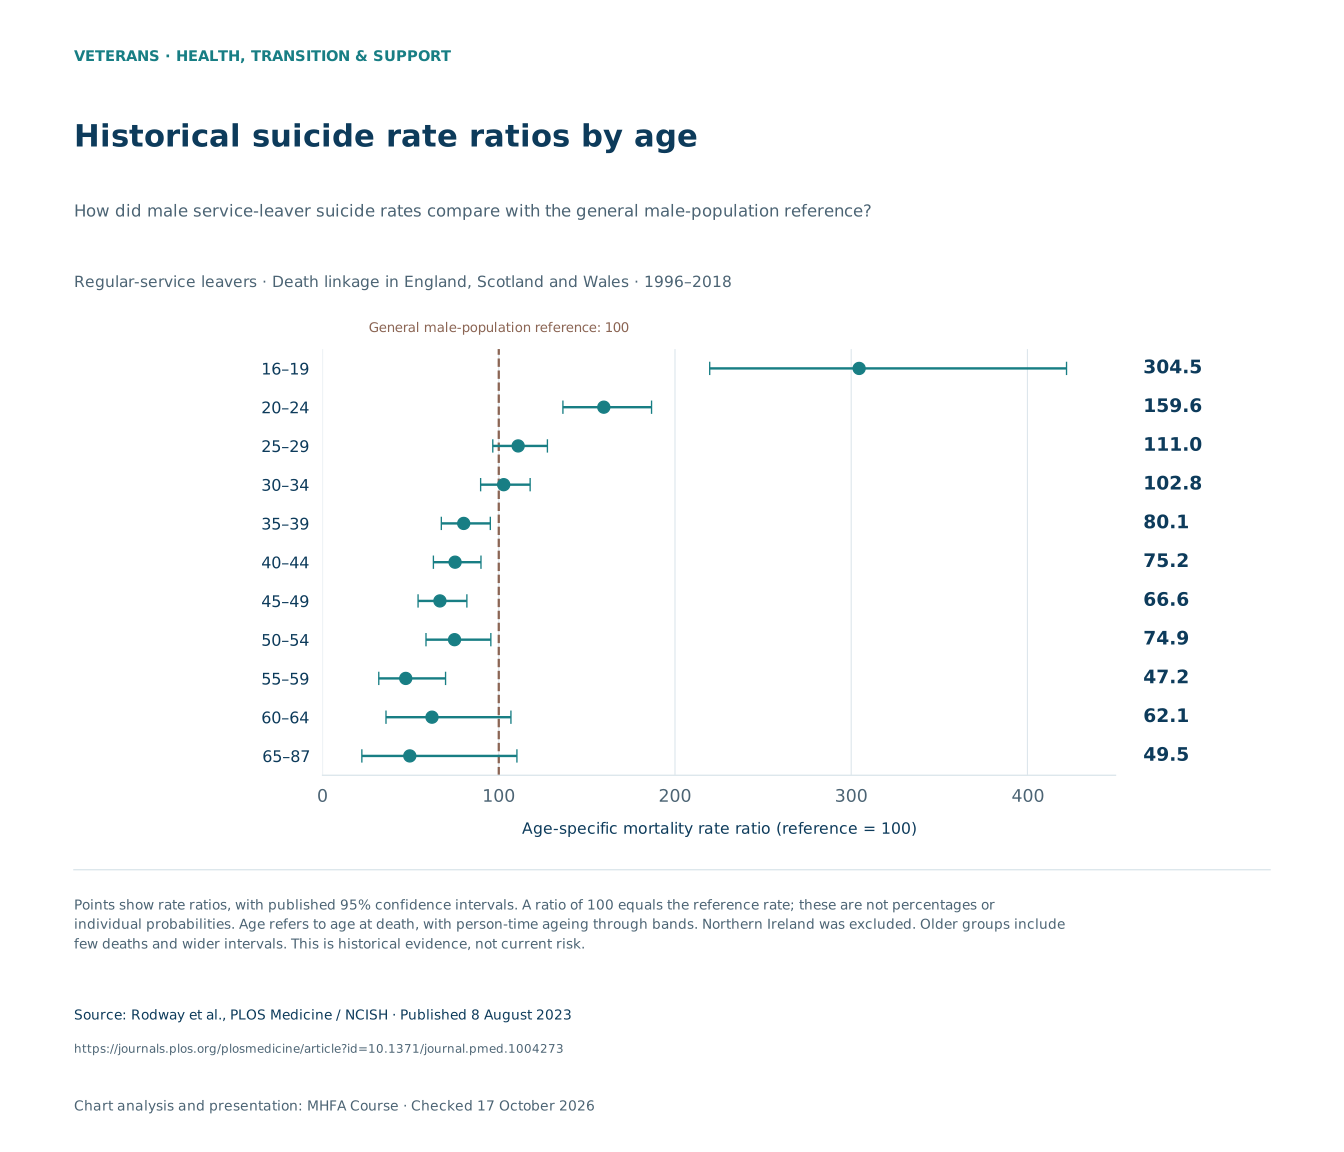
Among male veterans, the age-specific mortality rate ratio was 304.5 at ages 16–19 and 159.6 at ages 20–24, against a same-age population reference of 100. These historical estimates should not be described as one uniform current risk for everyone under 25.
The age-specific ratios below are not percentages of veterans. They compare rates on a scale where the study’s general male-population reference is 100. The overall age-standardised ratio is a different statistic and is not plotted as an age group.
Historical suicide rate ratios by age
How did male service-leaver suicide rates compare with the general male-population reference?
| Group / measure | rate ratio (general-population reference=100) | 95% interval |
|---|---|---|
| 16–19 | 304.5 | 219.7–422.2 |
| 20–24 | 159.6 | 136.4–186.7 |
| 25–29 | 111 | 96.6–127.6 |
| 30–34 | 102.8 | 89.7–117.8 |
| 35–39 | 80.1 | 67.4–95.2 |
| 40–44 | 75.2 | 62.9–89.9 |
| 45–49 | 66.6 | 54.2–81.9 |
| 50–54 | 74.9 | 58.7–95.5 |
| 55–59 | 47.2 | 31.9–69.8 |
| 60–64 | 62.1 | 36–106.9 |
| 65–87 | 49.5 | 22.3–110.3 |
Points show rate ratios, with published 95% confidence intervals. A ratio of 100 equals the reference rate; these are not percentages or individual probabilities. Age refers to age at death, with person-time ageing through bands. Northern Ireland was excluded. Older groups include few deaths and wider intervals. This is historical evidence, not current risk.
Risk factors and contact with services in the historical cohort
Higher risk was associated with being male, Army service, discharge at a younger age, being untrained at discharge and shorter service. The researchers could not directly examine all pre-service vulnerabilities. The study does not prove that adverse childhood experiences caused the observed pattern.
Among the 1,086 people in this cohort who died by suicide, 273 (25%) had contacted specialist NHS mental-health services in the preceding 12 months. The figure was 21% among those aged 24 or younger.
Those percentages are conditional on deaths in the historical cohort. They do not measure access to care among all veterans. Other forms of help, including GP contact, are outside this particular measure; the remaining people should not be described as having received no support.
Why the ONS 2021 count is kept separate
ONS identified 253 veteran suicides occurring in England and Wales in 2021, using deaths registered by the end of 2022. The release was published on 5 April 2024.
Veteran identification and registration delays can lead to undercoverage. The dedicated series has not yet supplied a replacement estimate identified in this review, so the count remains clearly dated rather than relabelled as a current annual total.
MOD’s separate latest suicide release covers serving Regular Armed Forces personnel through 2025. Serving-personnel deaths must not be presented as deaths among ex-serving veterans or added to an unmatched veteran count.
Practical needs and mental-health support can overlap.
Leaving the Armed Forces can bring changes in work, housing, routines and social networks. The transition is different for each person; it does not inevitably mean losing all community or developing a mental-health condition.
Social connection and practical assistance can matter alongside access to mental-health care. Historical cohort findings support attention to younger service leavers while maintaining prevention and support for veterans of all ages.
Help-seeking can occur during service, soon after leaving or much later. An average drawn from patients attending one specialist service should not be applied to all veterans or treated as a recommended waiting period before seeking help.
Potential barriers include stigma, uncertainty about available help and concerns about whether a service understands military experience. Support should reflect current needs rather than an assumption that every veteran follows the same path.
The overlap between health and social circumstances makes practical support relevant without turning every adjustment or relationship into a treatment claim. Different people may need different combinations of community connection, practical help and clinical care.
Op COURAGE and support in England
Op COURAGE: The Veterans Mental Health and Wellbeing Service provides specialist support in England for veterans, reservists and serving personnel with a discharge date. People can contact the service themselves or be referred, and an assessment helps identify appropriate care.
Support can include links to help with housing, relationships, finances and employment. Eligibility and local arrangements apply; the service is not one UK-wide system and this description does not promise immediate treatment or a particular outcome.
Reading treatment-service outcomes
Combat Stress publishes outcomes from specialist treatment services for veterans. These can show improvement among the people treated, but the denominator, follow-up period and definition of recovery need to remain beside a headline percentage.
Combat Stress and NHS Talking Therapies serve different populations and use different outcome definitions. Their headline percentages do not establish that one service is more effective than the other. Recovery does not guarantee that symptoms will never recur.
Serving-personnel healthcare is a different dataset
MOD’s latest mental-health report covers 2025/26 and was published on 2 July 2026. It reports that 11.8% of eligible serving personnel—17,826 people—were seen in military healthcare for a mental-health-related reason.
This is a healthcare-contact measure, not a survey estimate of all mental illness and not a rate among veterans. Specialist initial assessments and final diagnoses also have different definitions.
Our Mental Health First Aid courses can be adapted for military and veteran settings, equipping those working with the armed forces community to recognise distress and provide initial support.
Keeping the meaning with the numbers.
Do these figures describe all UK veterans?
No single dataset does. Cohort research includes defined serving and ex-serving groups. Other records cover England and Wales or selected treatment-service patients. The population beside each measure is essential to its meaning.
Does probable PTSD mean a confirmed diagnosis?
No. Probable PTSD indicates that reported symptoms meet a questionnaire threshold. It is a research-screening result, distinct from an individual clinical assessment and recorded diagnosis.
Why is a paper published in 2026 based on earlier responses?
Research takes time to analyse, review and publish. The April 2026 Phase 4 paper analyses 2022–2023 responses from the wave reported earlier in 2024. The new publication date does not make those responses a 2026 observation.
Can the cohort percentage be multiplied by the veteran population?
That would combine different populations and methods. A selected military cohort’s symptoms cannot simply be applied to an administrative estimate of all resident veterans to produce a national count.
Do service-use figures show how many veterans need care?
Not by themselves. Healthcare contacts describe people using a defined service. Some people with needs may not use that service, and the reason for contact may differ from the condition measured in a survey.
Is transition to civilian life always harmful?
No. Circumstances and experiences vary. Work, housing, finances, relationships and social connection can be relevant, but a service-leaver label does not predict an individual’s mental health.
Methods, uncertainty and reuse
This guide is a presentation of published evidence, not a new survey. The downloads retain source definitions, service-status categories, fieldwork and publication dates, exact table values and published uncertainty where available.
Whole-study samples are not substituted for unpublished question-specific bases. Missing confidence intervals do not mean zero uncertainty. Adjusted and unadjusted comparisons, screening thresholds and diagnostic records must remain distinguishable.
Mortality ratios use a reference population and period. Service-contact percentages use eligible service populations. No causal effect, individual prediction or comparison of treatment effectiveness is inferred from unlike sources.
Veteran mental health charts.
Keep service history and scope in view.
Download SVG and PNG charts, CSV data and methodology. Keep the study population, dates, definitions and limitations with every reused figure.
Mental Health First Aid Course (2026). Veterans Mental Health Statistics UK. Evidence checked 17 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/veterans-mental-health-statistics-uk
Sources
Primary evidence and methodology. Checked 17 October 2026.
- KCMHR, Phase 4 Health and Wellbeing Cohort Study report
- King’s College London, report publication record
- King’s College London, peer-reviewed Phase 4 paper published April 2026
- King’s College London, Health and Wellbeing Cohort Study
- Rodway etal., Suicide after leaving the UK Armed Forces 1996–2018: A cohort study
- NHS, Mental health support for veterans, service leavers and reservists
- MOD, UK armed forces mental health 2025/26: annual report
- ONS, UK armed forces veterans, England and Wales: 2024 and 2025
- MOD, UK armed forces suicides: 2025
- ONS, Suicides in UK armed forces veterans, England and Wales: 2021
- Combat Stress, service impact and outcome definitions
- Combat Stress, current annual report and accounts collection