
PTSD Statistics UK: 2026 Facts, Data & Key Insights
PTSD statistics UK
The evidence behind PTSD screening, recognition and treatment — with the definitions that make the figures meaningful.

Adults who screened positive in England’s latest psychiatric morbidity survey.
England · adults aged 16+APMS 2023/24 · screening, not diagnosis
Adults reporting that a professional had told them they had PTSD at some point.
England · adults aged 16+APMS 2023/24 · lifetime self-report
Among adults screening positive, for any mental or emotional problem.
England · adults screening positiveAPMS 2023/24 · not necessarily PTSD treatment
A positive screen is not a diagnosis.
Post-traumatic stress disorder can develop after a very frightening or distressing experience. The statistics on this page distinguish symptoms, reported diagnosis and treatment, rather than treating every measure as a count of people diagnosed with PTSD.
In APMS 2023/24, 5.7% of adults aged 16 and over living in private households in England screened positive for PTSD symptoms in the previous month. The PCL-C screening questionnaire identifies people for whom further clinical assessment may be warranted; it does not itself make a diagnosis.
Separately, 3.1% reported having received a professional PTSD diagnosis at some point in their lives. A past diagnosis and current symptoms cover different time periods. These results do not estimate lifetime PTSD risk across the UK.
A positive screen
A questionnaire can identify symptoms for which further assessment may be warranted. A positive screen does not itself confirm PTSD.
Professional diagnosis
Being told by a professional that you have PTSD is a different measure. A lifetime diagnosis can precede the symptoms captured by a current screen.
Treatment
Survey reports of medication or therapy concern any mental or emotional problem. NHS treatment outcomes refer to a separate group of completed referrals.
Who is represented, and how should uncertainty be read?
APMS is a survey of adults aged 16 and over living in private households in England. People in institutions or without a private-household address are not represented. England’s results should not be relabelled as a combined UK prevalence.
Weighted estimates aim to represent the surveyed population. The valid number answering each measure can differ. Confidence intervals are shown where supplied, while missing intervals are not invented. Sampling uncertainty is only one limitation: response, disclosure and the screening method also matter.
The survey uses the PCL-C assessment. It is not a new complex-PTSD diagnostic instrument, and its results should not be described as a count of all diagnoses made using newer diagnostic categories.
APMS also asks about lifetime experience of a traumatic event. This is a different outcome from screening positive for PTSD in the previous month. Not everyone who experiences trauma develops PTSD.
The current survey found that 34.8% of adults reported a lifetime traumatic event. The gender comparison below describes that reported experience, not the proportion who developed PTSD after it.
Reported lifetime trauma, a different measure
What share reported experiencing a traumatic event at some point in their lives?
| Group / measure | percent | 95% interval |
|---|---|---|
| Women | 37.2% | 35.1–39.3% |
| Men | 31.9% | 29.5–34.3% |
| All adults | 34.8% | 33.2–36.4% |
Lifetime trauma is a different outcome from current PTSD symptoms. Not everyone who experiences trauma develops PTSD. Do not use these shares to calculate a new trauma-to-PTSD risk. Whiskers show 95% confidence intervals. The all-adult reference is included in the data table; it is not a third independent group.
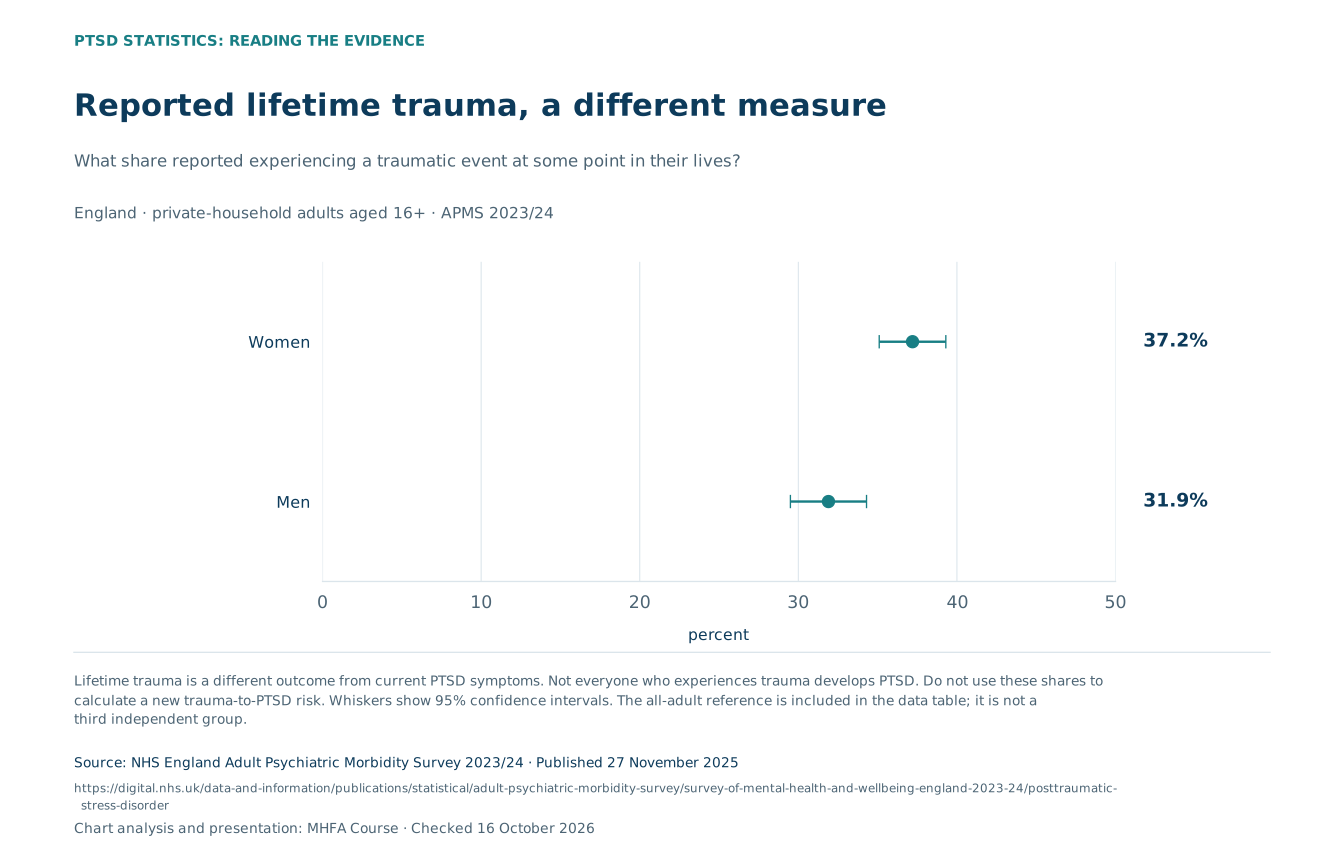
The percentages should not be used as a denominator for a new trauma-to-PTSD risk calculation. Current symptoms, lifetime exposure and professional diagnosis involve different questions and periods. A simple division would not establish the probability of developing PTSD after a particular event.
Experiences that can precede PTSD
NHS guidance describes several experiences that can precede PTSD. The following examples are not ranked population risk estimates:
- Physical or sexual assault
- Serious accidents
- War, conflict or torture
- Traumatic experiences during childbirth or serious illness
The meaning and effects of an experience vary between people. Assessment should consider current symptoms and circumstances without assuming that everyone exposed to the same event will have the same outcome.
PTSD screens over time and across ages.
The APMS PTSD-screen estimate was 4.4% in 2014 and 5.7% in 2023/24. Although the point estimate was higher, the report did not consider the change statistically significant.
That distinction matters. Calling the difference a confirmed 30% increase would overstate what the survey can show. The estimates and their uncertainty are more informative than a relative-change headline on its own.
Positive PTSD screens across survey waves
What share of adults screened positive for symptoms in the previous month?
| Group / measure | percent | 95% interval |
|---|---|---|
| 2014 | 4.4% | 3.8–5% |
| 2023/24 | 5.7% | 4.9–6.6% |
A positive PCL-C screen is not a diagnosis. The APMS report did not consider the difference statistically significant. Whiskers show 95% confidence intervals; these are separate survey waves.

PTSD screening across age groups
What share within each age group screened positive for past-month PTSD symptoms?
| Group / measure | percent | 95% interval |
|---|---|---|
| 16–24 | 11.4% | 7.8–16.4% |
| 25–34 | 8.1% | 5.9–10.9% |
| 35–44 | 5.8% | 4.3–7.7% |
| 45–54 | 5.4% | 4.2–7% |
| 55–64 | 4.5% | 3.4–5.9% |
| 65–74 | 1.7% | 1.1–2.6% |
| 75+ | 0.5% | 0.2–1.2% |
Percentages are within each age group. A positive screen is not a confirmed diagnosis or a prediction for an individual. Whiskers show published 95% confidence intervals.
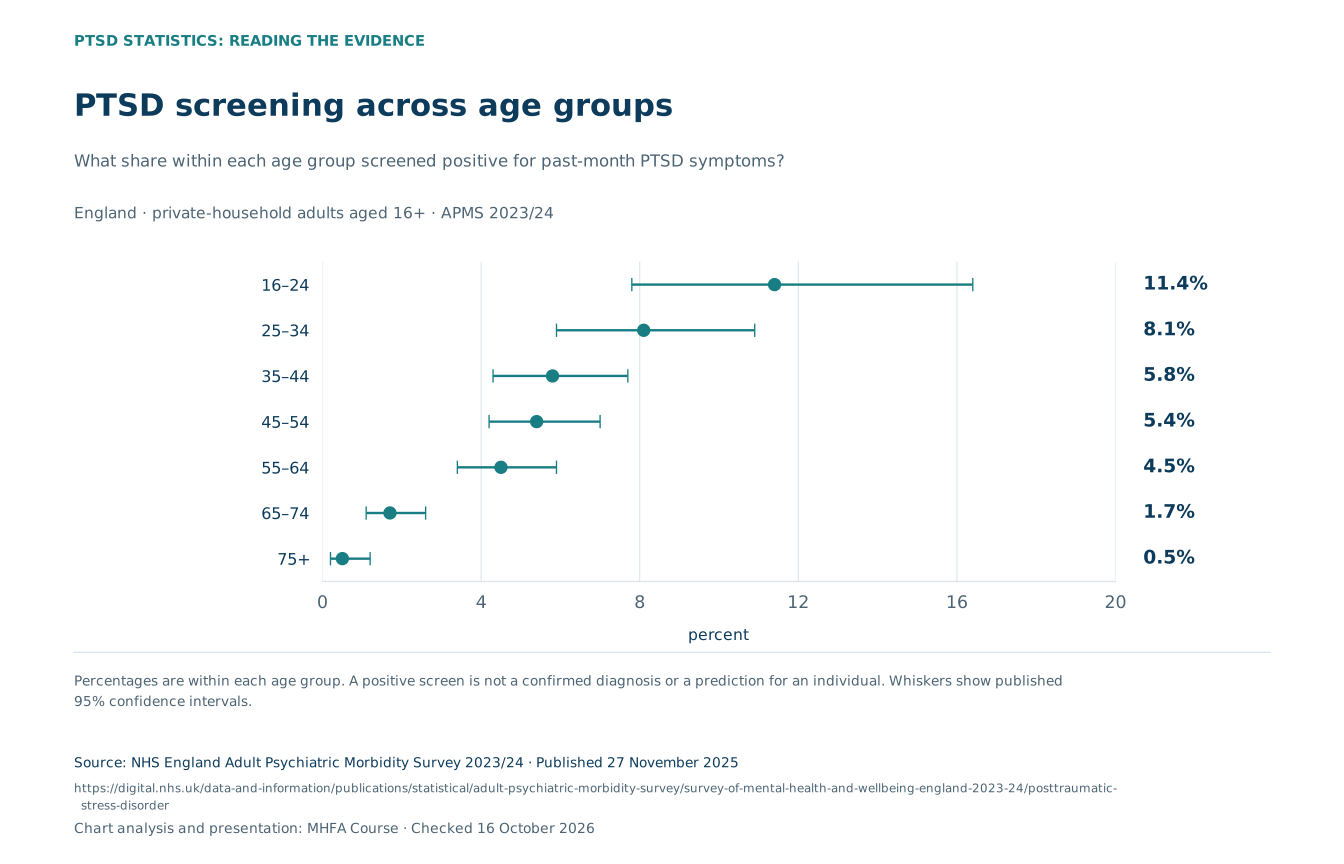
Positive screens were more common among younger adults: 11.4% of those aged 16–24 screened positive in 2023/24. The age profile describes groups in a survey, not a prediction of what will happen to an individual as they get older.
Among all adults aged 16 and over, 6.1% of women and 5.0% of men screened positive. Those estimates are separate from the lifetime-trauma comparison earlier on the page.
What the trend does not establish
Changes in awareness, disclosure or social conditions are possible research questions. These survey results do not establish that expanded diagnostic categories, the pandemic or any one influence caused the difference between estimates.
The chart shows separate survey waves rather than continuous monitoring. It should not be used to infer the prevalence in every intervening year or to describe the latest estimate as a new 2026 rate.
Deprivation, physical health and experience.
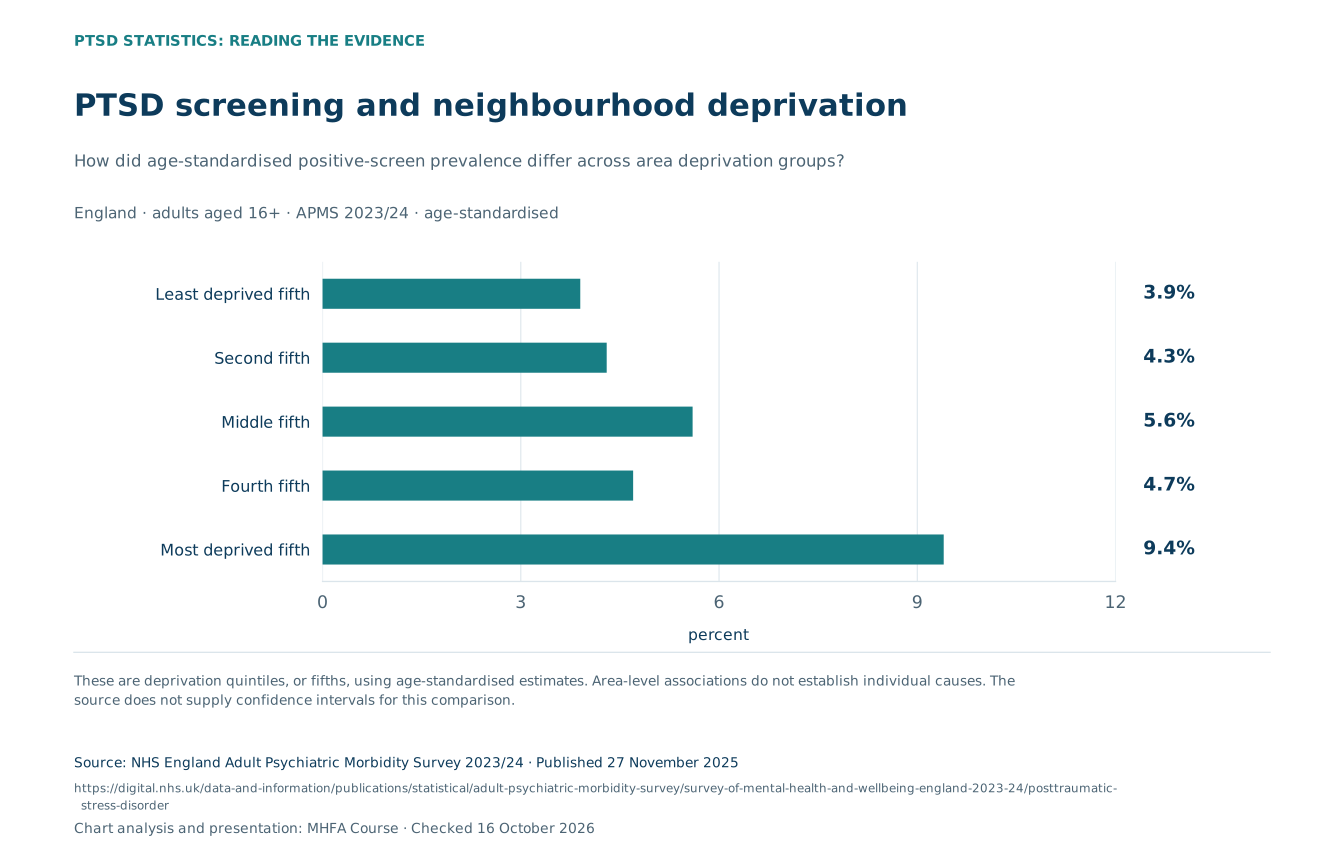
The survey finds associations between PTSD screening and people’s circumstances. To compare neighbourhood deprivation groups, it reports age-standardised estimates, allowing for differences in their age structures.
Positive-screen prevalence was 9.4% in the most deprived fifth of areas and 3.9% in the least deprived fifth. These are quintiles — fifths, not tenths. Area deprivation is not an individual diagnosis or a complete description of a person’s resources.
PTSD screening and neighbourhood deprivation
How did age-standardised positive-screen prevalence differ across area deprivation groups?
| Group / measure | percent |
|---|---|
| Least deprived fifth | 3.9% |
| Second fifth | 4.3% |
| Middle fifth | 5.6% |
| Fourth fifth | 4.7% |
| Most deprived fifth | 9.4% |
These are deprivation quintiles, or fifths, using age-standardised estimates. Area-level associations do not establish individual causes. The source does not supply confidence intervals for this comparison.
Physical health is a separate association.
Age-standardised positive-screen prevalence was 10.1% among adults with a limiting physical condition and 3.4% among those without one.
This does not mean that a physical condition caused PTSD, or that everyone with poor physical health has the same risk. The survey comparison does not isolate every other difference between the groups.
A clearly dated military cohort finding
A King’s Centre for Military Health Research study using 2014–16 data and published in 2018 found probable PTSD in 17% of ex-serving Regular personnel who had deployed to Iraq or Afghanistan in combat roles, compared with 6% in support roles.
This is a historical result for a defined cohort, not the current rate for all veterans. It should not be combined with the household survey to create a national estimate. Repeated occupational trauma, abuse and other experiences may be relevant to an individual assessment, but the context and population need to remain attached to the numbers.
A newer follow-up: different groups, not a like-for-like trend
A newer follow-up of the King’s military cohort was published in April 2026, using 2022–23 fieldwork. Among 4,104 respondents, 9.4% screened for probable PTSD.
The estimate was 10.5% among ex-serving Regulars and 7.4% among serving Regulars. These are different group definitions from the older combat-versus-support comparison. They should not be joined into a trend or relabelled as new combat-role figures.
The findings concern a particular continuing cohort and a screening measure. They are not a current diagnosis rate for all UK veterans, and the total respondent count is not the valid base for every subgroup.
Current symptoms and a history of diagnosis.
Among adults who screened positive in APMS 2023/24, 18.9% reported a previous professional PTSD diagnosis. The survey also asked about believing they had PTSD and about a reported diagnosis together with symptoms in the past year.
These are related, overlapping measures within the screen-positive group. They do not divide people into mutually exclusive stages of a diagnostic pathway.
Recognition among adults screening positive
What did adults with a positive current screen report about recognition and diagnosis?
| Group / measure | percent |
|---|---|
| Ever believed they had PTSD | 27.9% |
| Ever reported a professional PTSD diagnosis | 18.9% |
| Professional diagnosis and symptoms in the past year | 17.1% |
These measures are nested and overlap, not mutually exclusive stages. They are self-reports, not diagnoses independently verified from clinical records. The denominator is adults screening positive, not all adults.
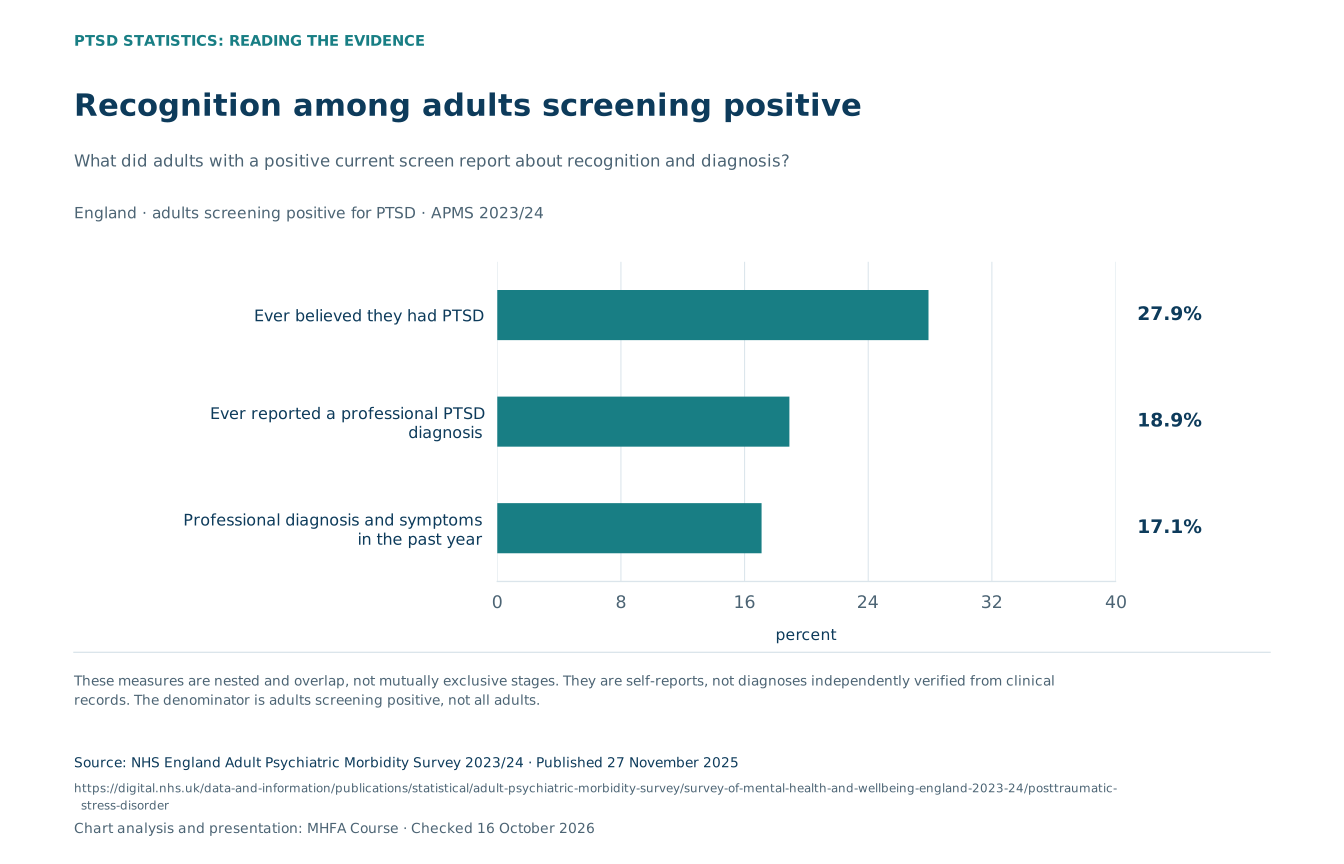
A positive screen does not establish that a professional diagnosis was missed. Equally, a lifetime diagnosis does not mean a person will screen positive at every later assessment. Symptoms, recognition, help-seeking and diagnosis are distinct experiences.
The measures are self-reported rather than independently verified against clinical records. They do not establish that everyone without a reported diagnosis required the same intervention or that everyone with a diagnosis received treatment.
What treatment figures can tell us.
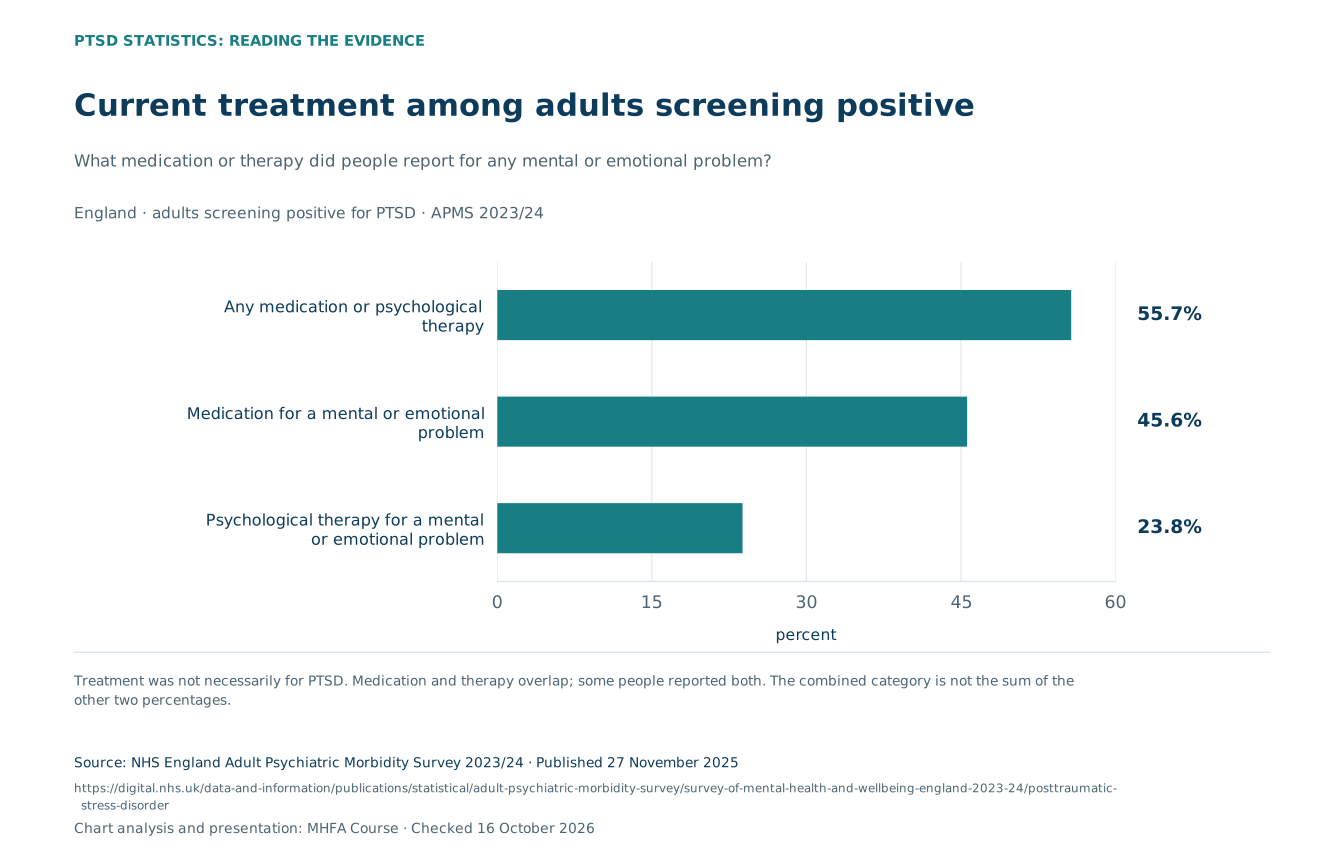
Among adults screening positive for PTSD in APMS 2023/24, 55.7% reported current medication or psychological therapy for any mental or emotional problem. Medication was reported by 45.6% and psychological therapy by 23.8%.
Some people reported both, so medication and therapy percentages overlap. The survey did not establish that those treatments were specifically for PTSD, and the figures should not be presented as PTSD-specific treatment coverage.
Current treatment among adults screening positive
What medication or therapy did people report for any mental or emotional problem?
| Group / measure | percent |
|---|---|
| Any medication or psychological therapy | 55.7% |
| Medication for a mental or emotional problem | 45.6% |
| Psychological therapy for a mental or emotional problem | 23.8% |
Treatment was not necessarily for PTSD. Medication and therapy overlap; some people reported both. The combined category is not the sum of the other two percentages.
NHS Talking Therapies: a separate outcome measure.
The published recovery rate for referrals with PTSD as the presenting complaint was 41.9% in England in 2025/26, compared with 50.1% overall.
NHS England flagged presenting-complaint data issues for six providers. Condition-specific results therefore need caution. The comparison does not establish why outcomes differ or adjust for every difference in the people and cases receiving care.
What recovery means in this service report
Recovery is measured among eligible completed referrals, excluding those known to be below the clinical threshold at the start. It records movement from above to below the programme’s relevant symptom thresholds.
This is not a guaranteed cure, an outcome for every referral received or a result for everyone in the population with PTSD. Service recovery, survey treatment use and a positive symptom screen describe different groups and cannot be joined into a treatment funnel.
The annual report covers 2025/26 and was published on 24 September 2026. Its newer publication date does not make it a new estimate of how common PTSD is in the general population.
PTSD can be treated. NHS guidance describes trauma-focused cognitive behavioural therapy, EMDR and medicines among the options, with care planned around the individual. The appropriate approach depends on assessment; the survey and service percentages do not forecast a particular person’s response.
PTSD and the Risk of Suicide
PTSD can be associated with suicidal thoughts and behaviour, but risk varies between people and studies. The sources cited here do not provide a UK lifetime estimate of suicide attempts among people with PTSD. Clinical assessment should consider the person’s current distress, circumstances and support needs.
- Take suicidal thoughts seriously and help the person reach appropriate professional support
- If someone is in immediate danger, seek emergency help rather than waiting for a routine appointment
Suicidal feelings can change and support is available. PTSD and other mental health conditions should be treated without assumptions that suicide is inevitable. Our suicide statistics guide and men’s mental health statistics guide explain the distinction between population patterns and individual risk.
Population figures are useful for understanding patterns and planning services. They cannot determine a particular person’s level of distress, support needs or outcome. Respectful assessment and appropriate help matter alongside the statistics.
Reading PTSD statistics accurately.
How common is PTSD in the UK?
The latest APMS estimate is that 5.7% of adults aged 16 and over in private households in England screened positive for past-month PTSD symptoms in 2023/24. That is a screening result for England, not a confirmed diagnosis rate or a combined UK prevalence.
Does screening positive mean someone has PTSD?
No. The PCL-C screen indicates symptoms for which further clinical assessment may be warranted. Diagnosis involves assessment beyond the screening score. A lifetime report of professional diagnosis is a separate measure.
Has PTSD definitely increased since 2014?
The point estimate rose from 4.4% to 5.7%, but the APMS report did not consider the difference statistically significant. The evidence does not support describing it as a confirmed 30% increase.
Why are 2023/24 survey results used in 2026?
APMS fieldwork ran from March 2023 to July 2024 and its PTSD chapter was published on 27 November 2025. These remain the latest APMS population estimates available at this review. Newer NHS service reports measure activity and outcomes rather than population prevalence.
Does 55.7% mean that 55.7% received PTSD treatment?
No. It is the share of adults screening positive who reported current medication or psychological therapy for any mental or emotional problem. The survey did not establish that this treatment was specifically for PTSD.
Is the NHS recovery rate a cure rate for everyone with PTSD?
No. The 41.9% figure relates to an eligible group of completed NHS Talking Therapies referrals with PTSD as their presenting complaint in 2025/26. It uses programme symptom thresholds and comes with a presenting-complaint data-quality warning.
Methods, uncertainty and reuse
This guide is an original visual presentation of published evidence, not a new survey or a diagnostic tool. Keep the population, period, instrument and denominator with each figure.
APMS estimates are weighted survey results. Current PTSD symptoms, lifetime trauma, a reported diagnosis and treatment use have different questions and reference periods. Where the source age-standardises a comparison, the chart says so. Missing confidence intervals are not estimated or treated as zero uncertainty.
The trend’s higher point estimate is not a statistically established increase. Group differences and associations do not prove an individual cause or predict a person’s outcome. Overlapping recognition and treatment measures should not be added.
Charts begin at zero. CSV files retain source precision, available confidence intervals, bases and source locations. Keep the methodology with reused charts, especially when comparing them with a study of a different population or a service report.
PTSD charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the measure, population, time period and denominator with every figure.
Mental Health First Aid Course (2026). PTSD Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/ptsd-statistics
Sources
Primary evidence and methodology. Checked 16 October 2026.
- NHS England: APMS PTSD chapter, 2023/24
- NHS England: APMS PTSD data tables
- NHS England: APMS survey methods and population coverage
- NHS England: interpreting estimates, intervals and age-standardisation
- NHS England: Adult Psychiatric Morbidity Survey collection
- NHS England: Talking Therapies annual report and quality notice, 2025/26
- NHS: PTSD assessment and treatment
- NICE NG116: post-traumatic stress disorder recommendations
- King’s College London: fourth military cohort follow-up, published 2026
- King’s College London: historical military findings, published 2018
- NHS: help for suicidal thoughts
- DHSC: suicide prevention strategy for England, 2023–2028