
Postnatal Depression Statistics UK: 2026 Facts, Data & Key Insights
Postnatal depression statistics UK
What the latest evidence tells us about symptoms after birth, recognition and access to support.

Scored above the depression symptom threshold in the latest NPEU national maternity survey.
England · May 2024 birth cohortStandardised EPDS screen
Among women who said they had experienced depression symptoms after birth.
England · 2024 maternity surveyConditional self-reported measure
Among women who said they had experienced depression symptoms after birth.
England · 2024 maternity surveyDifferent base from the EPDS screen
Symptoms, diagnosis and care are different measures.
Postnatal depression can affect parents and family life, and appropriate support is available. Understanding the statistics starts with separating clinical estimates, symptom screens and people’s accounts of diagnosis or care.
The Royal College of Psychiatrists gives a broad estimate that 10–15% of mothers experience postnatal depression after childbirth. That is a different measure from the 22.5% who scored above a depression screening threshold in the latest NPEU maternity survey in England.
The difference does not establish that one source is wrong. The population, timing and way of identifying depression differ. A screening questionnaire identifies potentially significant symptoms; clinical assessment considers those symptoms and the person’s circumstances.
Symptom screening
A score above a screening threshold indicates potentially significant symptoms. It does not by itself confirm a clinical diagnosis.
Recognition & diagnosis
Women were also asked whether they had experienced symptoms and received a professional diagnosis. Those answers have a separate, conditional denominator.
Specialist services
Service records count access to care for a range of perinatal mental-health needs. They are not a register of postnatal depression cases.
The 2024 national maternity survey received 3,728 responses, a 24% response rate. Women aged 16 or over were recruited through England’s birth register, using a two-week sampling period in May 2024. The total response count is not the denominator for every question, because some respondents did not answer every item.
The results principally describe mothers’ experiences in England. They do not provide a combined prevalence for all UK parents or establish how common depression is among fathers and partners.
How the 10–15% estimate became a count of affected mothers
In a July 2025 statement, the Royal College of Psychiatrists applied its broad estimate to England’s 2024 births, illustrating a possible 56,000–85,000 affected mothers. This was an estimate, not a count of diagnosed cases or a number of women on an NHS waiting list.
The national maternity survey answers a separate question about symptoms at the time of the survey. It should not be used to relabel that earlier clinical estimate as a diagnosed-case count.
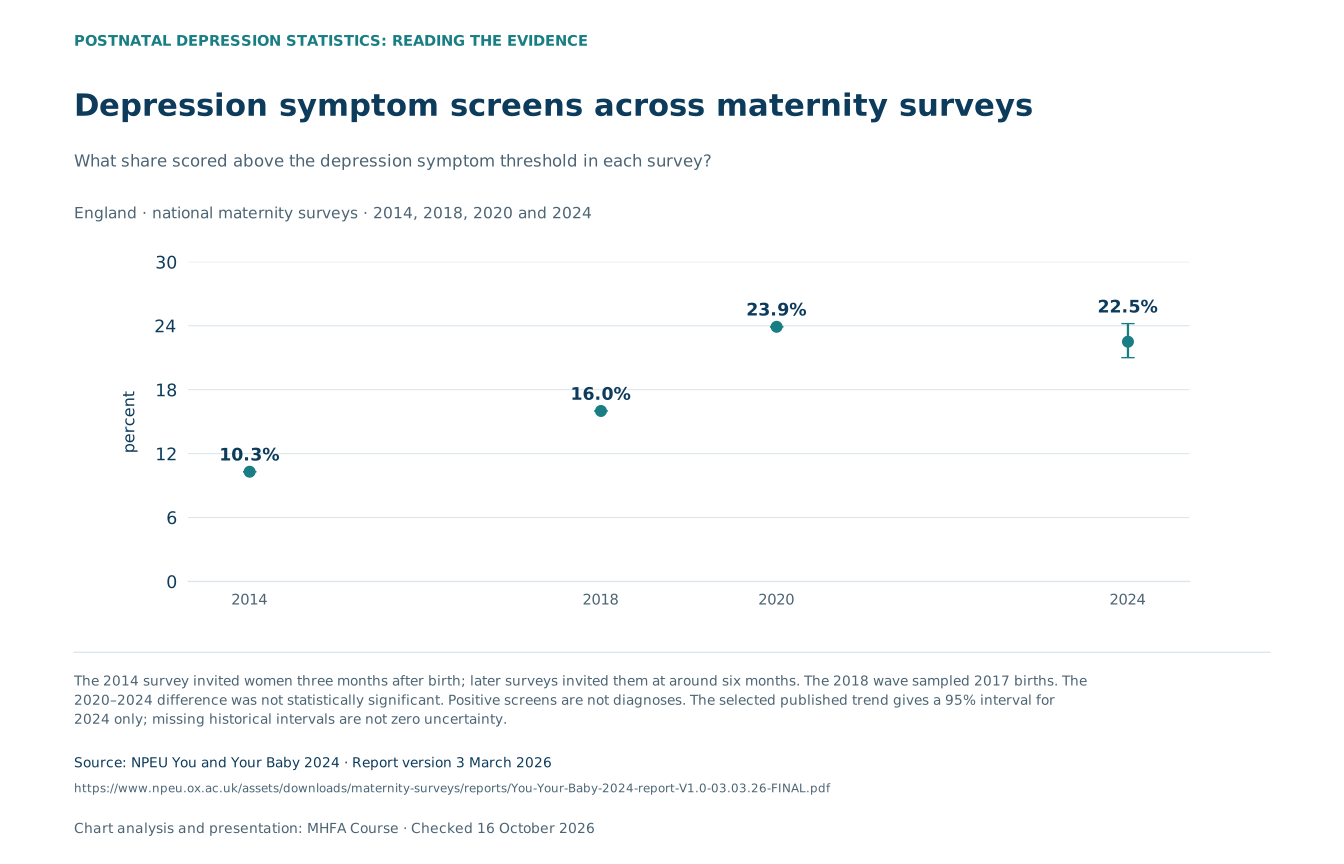
Symptoms after birth, across survey waves.
The published depression-screen estimates were 10.3% in 2014, 16.0% in 2018, 23.9% in 2020 and 22.5% in 2024. The latest reduction from 2020 was not statistically significant.
The report describes symptom levels remaining above those before the pandemic. However, there is an important timing difference: the 2014 survey invited women at three months after birth, while the later surveys invited them at around six months. The points are not identical measurements taken at the same postpartum age.
Depression symptom screens across maternity surveys
What share scored above the depression symptom threshold in each survey?
| Group / measure | percent | 95% interval |
|---|---|---|
| 2014 | 10.3% | Not supplied |
| 2018 | 16% | Not supplied |
| 2020 | 23.9% | Not supplied |
| 2024 | 22.5% | 21–24.2% |
The 2014 survey invited women three months after birth; later surveys invited them at around six months. The 2018 wave sampled 2017 births. The 2020–2024 difference was not statistically significant. Positive screens are not diagnoses. The selected published trend gives a 95% interval for 2024 only; missing historical intervals are not zero uncertainty.
Depression, anxiety and post-traumatic stress symptoms
What share screened above each threshold in the latest NPEU maternity survey?
| Group / measure | percent | 95% interval |
|---|---|---|
| Depression symptoms (EPDS) | 22.5% | 21–24.2% |
| Anxiety symptoms (GAD-2) | 16.1% | 14.8–17.6% |
| Post-traumatic stress symptoms (PC-PTSD-5) | 11.8% | 10.5–13% |
The instruments cover different recall windows: EPDS the previous week, GAD-2 the previous fortnight and PC-PTSD-5 the previous month. Groups overlap: do not add them. A separate 29.8% screened above at least one threshold. Positive screens are not diagnoses. Whiskers show 95% confidence intervals.
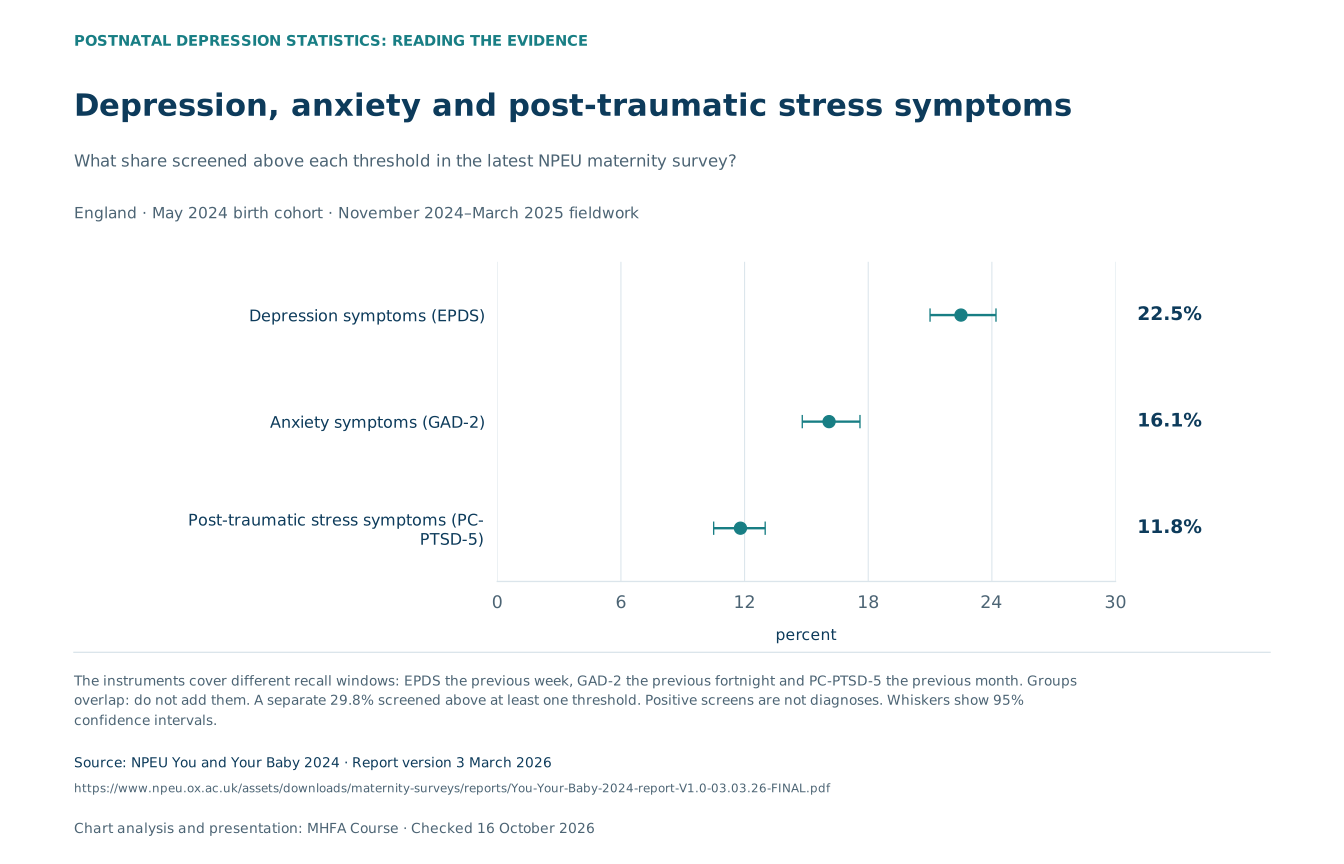
The latest survey also found 16.1% above the anxiety threshold and 11.8% above the post-traumatic stress threshold. 29.8% were above at least one of the three thresholds.
These groups overlap. Adding depression, anxiety and post-traumatic stress percentages would count some women more than once. The combined 29.8% is a separately calculated measure, not the sum of the three bars.
Survey timing, instruments and what a positive screen means
The 2018 survey sampled women who gave birth in October 2017; the wave name is not always the birth year. The latest survey sampled May 2024 births and collected responses from November 2024 to March 2025, beginning around six months after birth.
Each screening instrument uses its own questions and threshold. These results describe symptoms at the survey point, not every mental-health difficulty experienced throughout pregnancy and the whole first year after birth.
The comparison does not establish that the pandemic, cost of living or any single factor caused the pattern. Differences in circumstances, response and survey timing must be considered. Confidence intervals show sampling uncertainty; they do not resolve every limitation or turn a screen into a diagnosis.
A symptom, a diagnosis and support are not the same.
Women were asked separately whether they had experienced depression or anxiety symptoms after birth and whether they had received a professional diagnosis. Those questions do not use the same denominator as the standardised screening results.
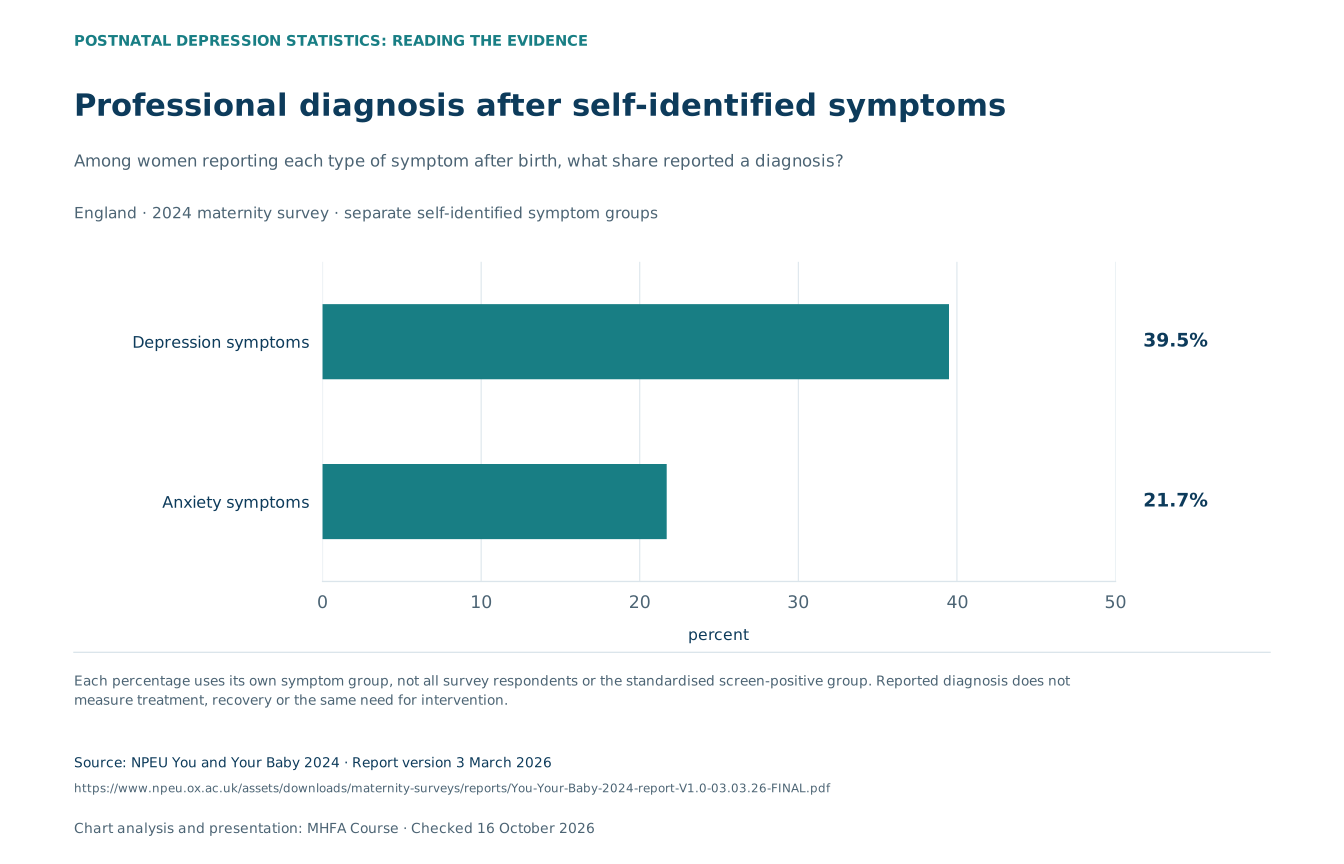
Among women who self-identified depression symptoms after birth, 39.5% reported a professional diagnosis. The corresponding figure among those who self-identified anxiety symptoms was 21.7%. Each percentage uses its own symptom group.
Professional diagnosis after self-identified symptoms
Among women reporting each type of symptom after birth, what share reported a diagnosis?
| Group / measure | percent |
|---|---|
| Depression symptoms | 39.5% |
| Anxiety symptoms | 21.7% |
Each percentage uses its own symptom group, not all survey respondents or the standardised screen-positive group. Reported diagnosis does not measure treatment, recovery or the same need for intervention.
Support or treatment reported after depression symptoms
What support did women who self-identified depression symptoms after birth report?
| Group / measure | percent |
|---|---|
| No support or treatment | 43.9% |
| Support only | 10.6% |
| Psychological therapy, with or without support | 12.4% |
| Medication, with or without support | 13.5% |
| Therapy and medication, with or without support | 19.6% |
The source presents five mutually exclusive response categories. These describe reported support or treatment, not effectiveness or recovery. The base is different from the EPDS screen-positive group.
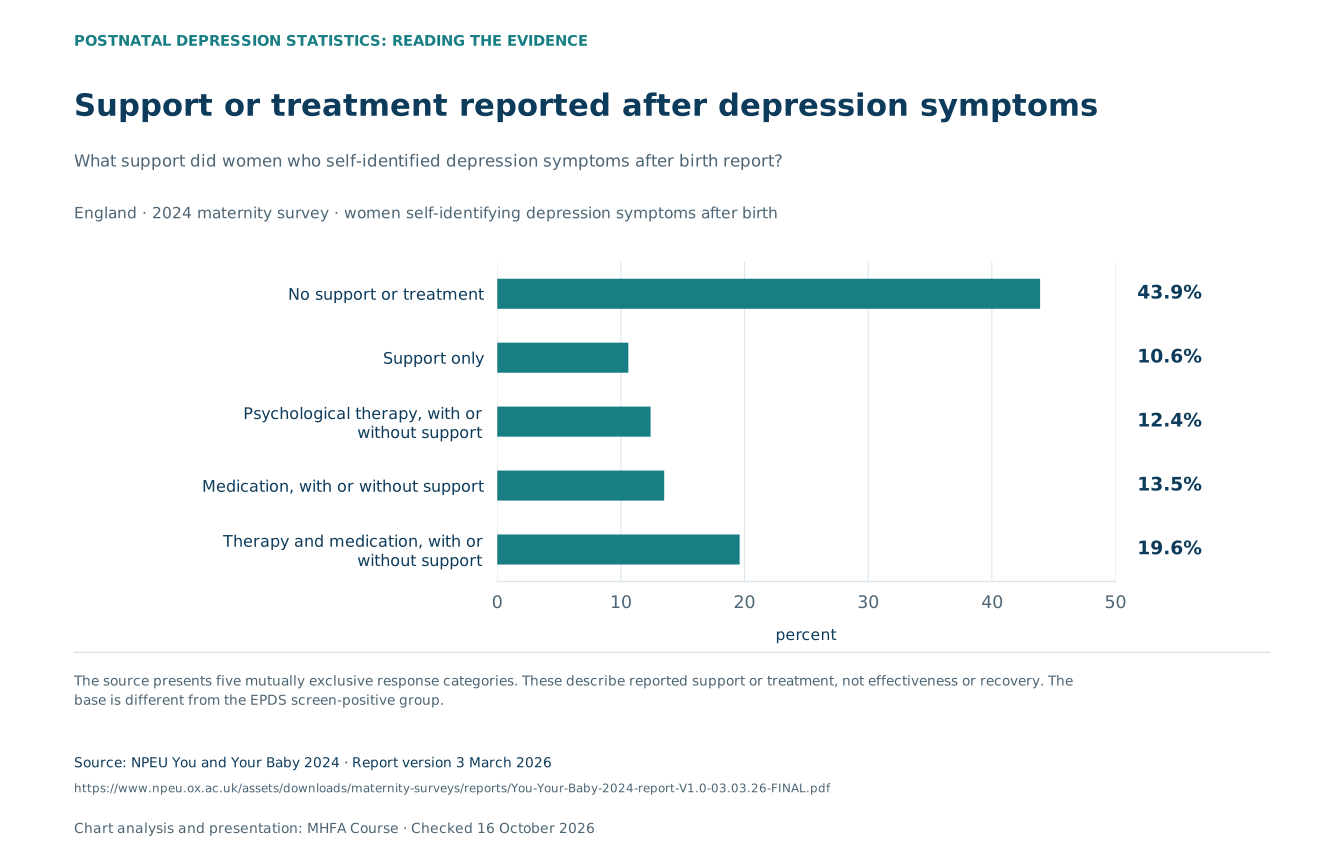
Among women self-identifying depression symptoms after birth, 43.9% reported no support or treatment. The remaining categories describe the types of support or treatment women reported. They should not be treated as a measure of how effective each intervention was.
Reporting no professional diagnosis does not establish that a person received no support. Conversely, reporting support does not establish recovery. The survey does not show that everyone without a diagnosis needed the same intervention.
Keep the denominator with the headline.
The 22.5% screening estimate relates to respondents with valid depression-screen data. The 39.5% diagnosis and 43.9% no-support estimates relate to women who said they had experienced depression symptoms after birth. They cannot be combined into a single pathway or used to calculate how many positive screens were untreated.
How mental health enters maternity care.
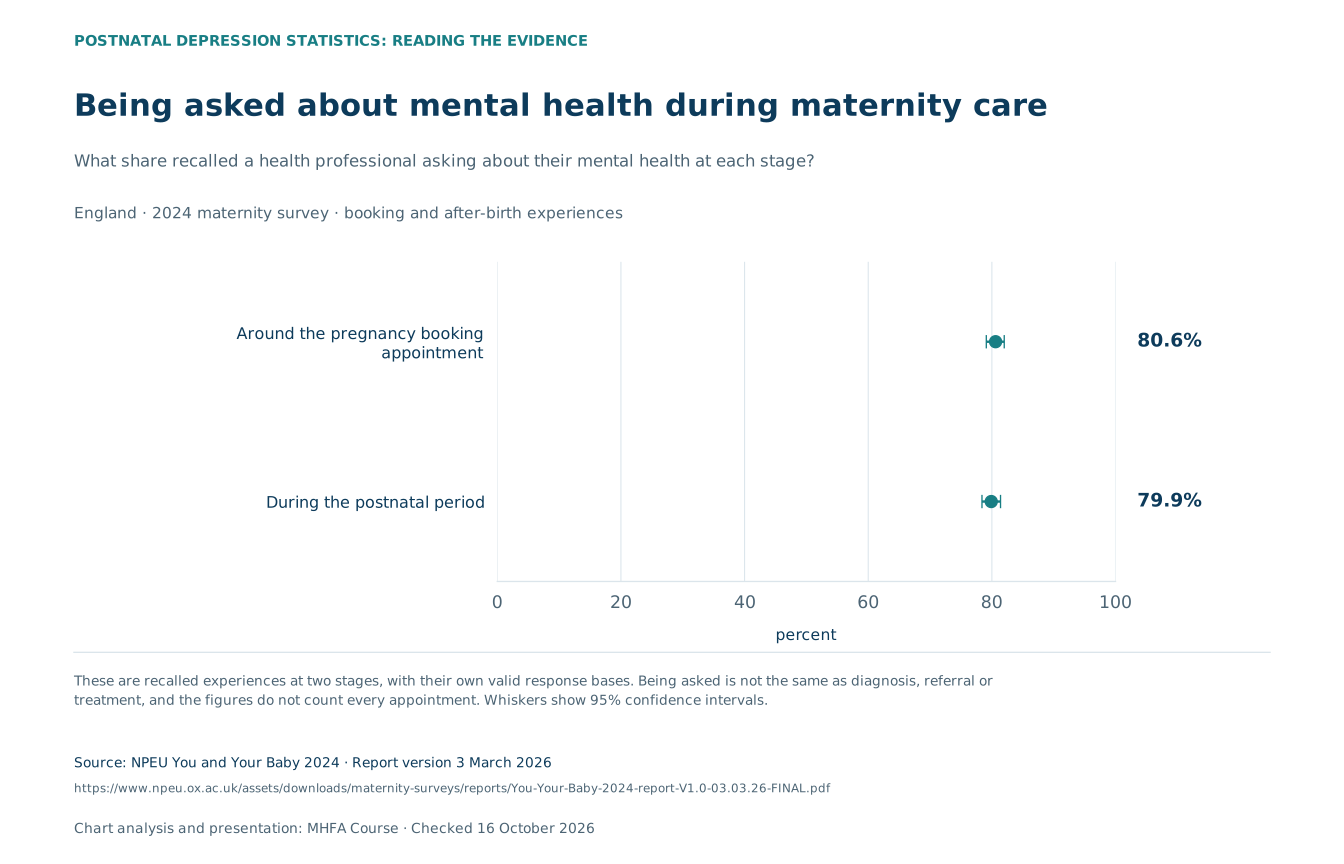
A conversation about mental health can be part of maternity care without being a diagnosis or a specialist referral. The survey asked women whether a health professional had asked about their mental health during pregnancy booking and after birth.
80.6% reported being asked around booking and 79.9% after birth. These are recollections of care at two stages, not a count of every contact or a measure of whether the conversation led to effective treatment.
Being asked about mental health during maternity care
What share recalled a health professional asking about their mental health at each stage?
| Group / measure | percent | 95% interval |
|---|---|---|
| Around the pregnancy booking appointment | 80.6% | 79.1–82% |
| During the postnatal period | 79.9% | 78.4–81.4% |
These are recalled experiences at two stages, with their own valid response bases. Being asked is not the same as diagnosis, referral or treatment, and the figures do not count every appointment. Whiskers show 95% confidence intervals.
A newer service-contact figure measures something different.
The latest NHS mental-health services release records 66,096 people in contact with specialist perinatal mental health community services, for the rolling year ending August 2026. The release was published on 8 October 2026.
This is a service-contact measure, not a count of postnatal depression diagnoses. It should not be joined to a separate dashboard series that combines perinatal and maternal mental-health services, or used to calculate the proportion of survey respondents receiving care.
Specialist perinatal mental-health services support a range of needs during pregnancy and after birth. Their access figures are a separate administrative measure. They should not be read as the number of women with postnatal depression, the number waiting for care or the number who have recovered.
Mental-health funding is wider than perinatal care
NHS mental-health spending in England was forecast at £16.1 billion for 2026/27. This is a general mental-health spending forecast, not a perinatal-services budget.
A national forecast does not establish the funding, availability or waiting time of a local perinatal service. Survey experiences of support and national service activity can inform the discussion without being interchangeable measures.
Reading the most serious outcomes carefully.
The most serious outcomes need their own definitions and denominators. Maternal mortality surveillance is not a measure of how many mothers experience postnatal depression.
The September 2026 MBRRACE-UK report covers UK deaths in 2022–24. Suicide remained the leading cause of death between six weeks and one year after the end of pregnancy. Psychiatric causes as a group accounted for 33% of late pregnancy-associated deaths.
That percentage is a share of recorded deaths in a defined period. It does not mean that 33% of mothers with postnatal depression die, and it does not mean that all those deaths were caused by depression.
During pregnancy and up to six weeks afterwards, thrombosis and thromboembolism were the leading cause of maternal death in the same report. A statement about the later period should not be applied to all maternal deaths.
Recognising difficulties and seeking support
A history of mental-health difficulties, limited support, relationship problems or stressful life events may be relevant. Postnatal depression can also occur without an obvious cause. It is not a parent’s fault and does not mean they are a bad parent.
NHS advice encourages parents to speak to a GP, midwife or health visitor if they think they may have postnatal depression. Help can include practical support, psychological therapy and medication where appropriate. Recovery and the most suitable support vary between individuals.
Assessment should reflect symptoms and circumstances, rather than assuming an age or ethnic group determines the outcome. The latest survey report does not provide the detailed subgroup comparisons needed to create a new age or deprivation ranking here.
Fathers and partners matter too
Fathers and partners can also experience depression after a baby is born. Their experiences should be assessed directly, rather than inferred from a mother’s symptoms or from a general-population percentage.
Partners who are struggling should seek support. The mothers’ survey results on this page do not provide a father or partner prevalence estimate. Our men’s mental health statistics guide provides separate wider context.
What these statistics can — and cannot — tell us.
How common is postnatal depression?
The Royal College of Psychiatrists gives a broad clinical estimate of 10–15% of mothers. Separately, 22.5% scored above the depression symptom threshold in England’s 2024 maternity survey. The latter is a screening result, not a confirmed diagnosis rate.
Why is the latest NPEU survey called 2024 when the report is from 2026?
The survey name refers to the May 2024 birth cohort. Responses were collected from November 2024 to March 2025 and the report was published in 2026. The available version is dated 3 March 2026. More recent service records measure access rather than symptom prevalence.
Did postnatal depression fall after 2020?
The depression-screen estimate fell from 23.9% in the 2020 survey to 22.5% in 2024, but the report says the difference was not statistically significant. The full trend also has a timing caveat: the 2014 survey invited women earlier after birth than the later waves.
Does 43.9% mean that nearly half of positive depression screens were untreated?
No. The 43.9% figure is among women who self-identified depression symptoms after birth, not among all those above the standardised EPDS screening threshold. It describes reported support or treatment, not an assessment of the intervention each person needed.
Can the depression, anxiety and post-traumatic stress figures be added?
No. A person can screen above more than one threshold. The survey separately reports that 29.8% were above at least one of the three; adding the individual percentages would double-count some women.
Are all the statistics for the whole UK?
No. The maternity survey and service figures cover England. MBRRACE-UK’s maternal mortality context covers the UK and measures a different outcome. The England figures should not be presented as a combined prevalence for all UK parents.
Methods, uncertainty and reuse
This guide is an original visual presentation of published evidence, not a new survey or a diagnostic tool. Keep the measure, population, birth cohort, question and denominator with each reused figure.
Survey estimates use the source’s weighting and available confidence intervals. The response count for the whole survey is not the valid base for every question. Non-response and differences in survey timing remain relevant even where an interval is supplied.
The charts use zero-based scales and separate survey waves. No confidence interval is invented where the selected source does not provide one. Symptom groups overlap; diagnosis and support questions have conditional bases; service access and mortality have their own populations and periods.
CSV files retain published precision, available bases, question details, source locations and scope notes. The downloadable charts and methodology should travel together so that the headline remains attached to its qualifications.
Postnatal mental-health charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the population, question, survey timing and denominator with every figure.
Mental Health First Aid Course (2026). Postnatal Depression Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/postnatal-depression-statistics
Sources
Primary evidence and methodology. Checked 16 October 2026.
- NPEU: latest national maternity survey, You and Your Baby 2024
- NPEU: You and Your Baby 2024 report (version 3 March 2026)
- Harrison and colleagues: primary analysis of the 2014–2020 maternity surveys
- MBRRACE-UK: Saving Lives, Improving Mothers’ Care 2026
- MBRRACE-UK: 2026 compiled report, current version 2.0
- NHS: postnatal depression
- Royal College of Psychiatrists: postnatal depression
- Royal College of Psychiatrists: dated estimate for England’s 2024 births
- NICE QS115: asking about mental health and wellbeing
- UK Parliament: NHS mental health spending forecast, March 2026
- NHS England: Mental Health Services Monthly Statistics, August 2026
- NHS: finding mental health care before, during and after pregnancy
- NHS England: specialist perinatal and maternal mental health service roles