
Police Officer Mental Health Statistics UK: 2026 Facts, Data & Key Insights
Police officer mental health statistics UK
What workforce surveys tell us about pressure, wellbeing and support—and why the population behind each figure matters.

often or always felt fatigued or physically exhausted by work
England and Wales territorial police workforce. A past-12-month experience, not a clinical diagnosis.agreed they face unrealistic time pressures
The current workforce survey includes police officers and staff; this is not an officer-only percentage.agreed they can access effective wellbeing support
Agreement with the access question, not a count of people who received or completed treatment.Whose experiences do the figures describe?
Police work can involve traumatic events, demanding shifts and organisational pressures. The experiences of a response officer, an investigator and a member of police staff can differ substantially.
A workforce survey describes the people and organisations it covers. It is important to distinguish officers from staff, participating forces from the whole service, and a report covering England and Wales from a UK-wide estimate.
Reported stress, wellbeing, symptoms, clinical diagnoses and administrative absence are also different measures. None can be substituted for the others or used alone to determine whether an individual needs support or is fit for a particular role.
33 of the 43 territorial forces actively participated. The report limits its representativeness claims to those participating forces; small numbers of responses from the other ten were also included. The 55,602-response territorial-force analysis is different from the larger total of 56,677 responses that includes non-territorial forces.
The 2026 report’s results are weighted to account for differing response rates. Participation was voluntary, so non-response bias remains possible: people who completed the survey may differ from those who did not. The overall sample is not the exact valid-response base for every question.
Reported experiences
Surveys describe a defined set of respondents, ranks and organisations. A percentage is only useful alongside its question, timeframe and denominator.
Different assessments
Reporting stress, screening positive for symptoms and receiving a clinical diagnosis measure different things. They should not be treated as interchangeable rates.
Individual circumstances
Survey averages cannot determine a person’s needs or fitness for a particular duty. Support and assessment should consider symptoms, functioning and circumstances.
What the older Police Federation survey measured
The 2024 Police Federation of England and Wales Pay and Morale Survey analysed 35,092 responses from federated-rank officers in England and Wales, approximately 24% of that workforce.
81% reported stress, low mood, anxiety or other mental-health or wellbeing difficulties in the previous 12 months. Among respondents reporting those difficulties, 93% said work had worsened them. The second percentage uses a smaller, conditional group; it is not 93% of all respondents or officers.
This historical officer survey has different coverage and questions from the newer workforce survey. Its percentages should not be joined to the new report as a simple trend in diagnosis or prevalence.
Pressure, fatigue and day-to-day wellbeing.
Workload, shifts, work-life balance and fatigue can affect how people experience police work. Survey findings can identify areas needing attention while leaving room for different experiences across roles and circumstances.
A response to a workplace question is not necessarily a clinical symptom or diagnosis. Some questions ask about frequency, others about agreement or the impact of a problem. The charts retain those distinctions rather than treating every percentage as the same kind of mental-health rate.
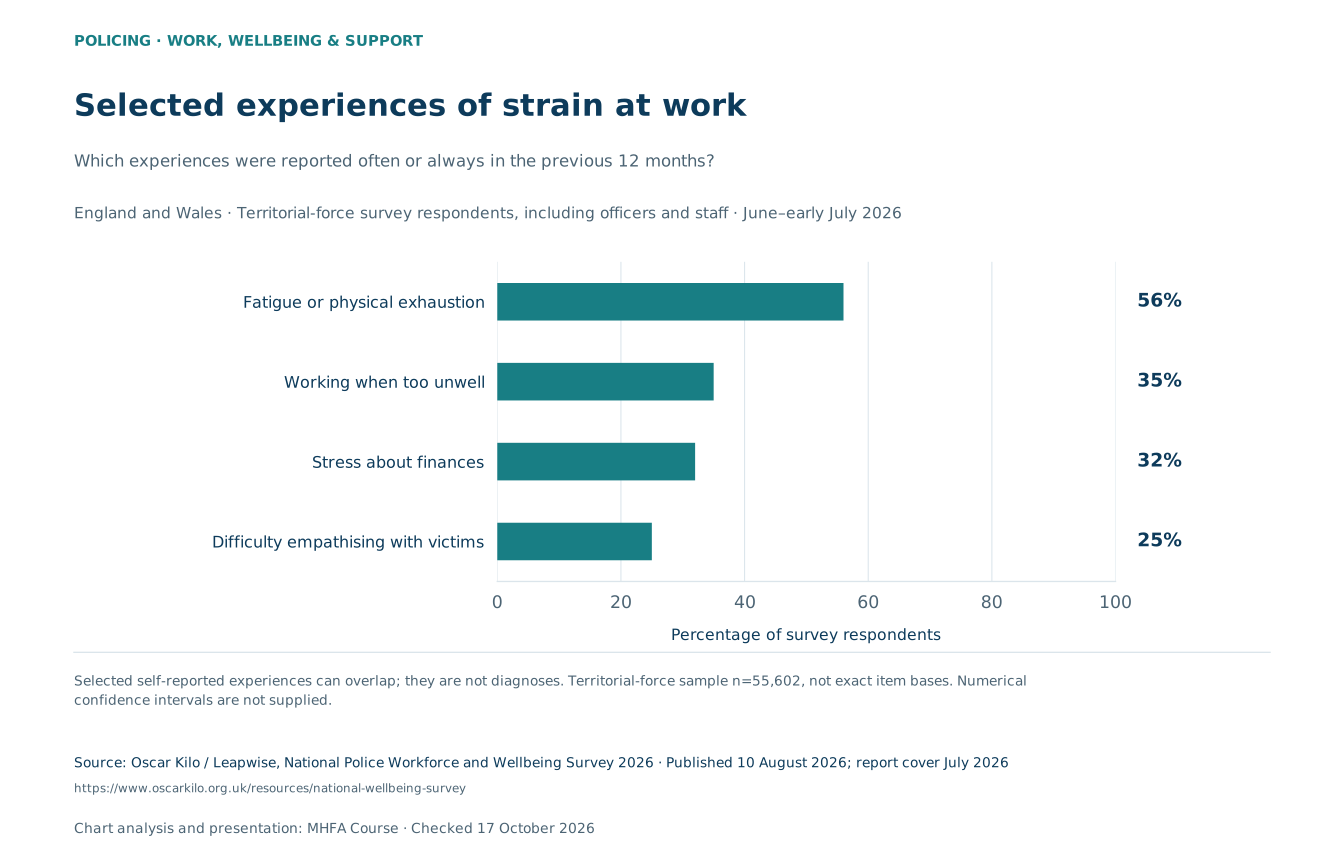
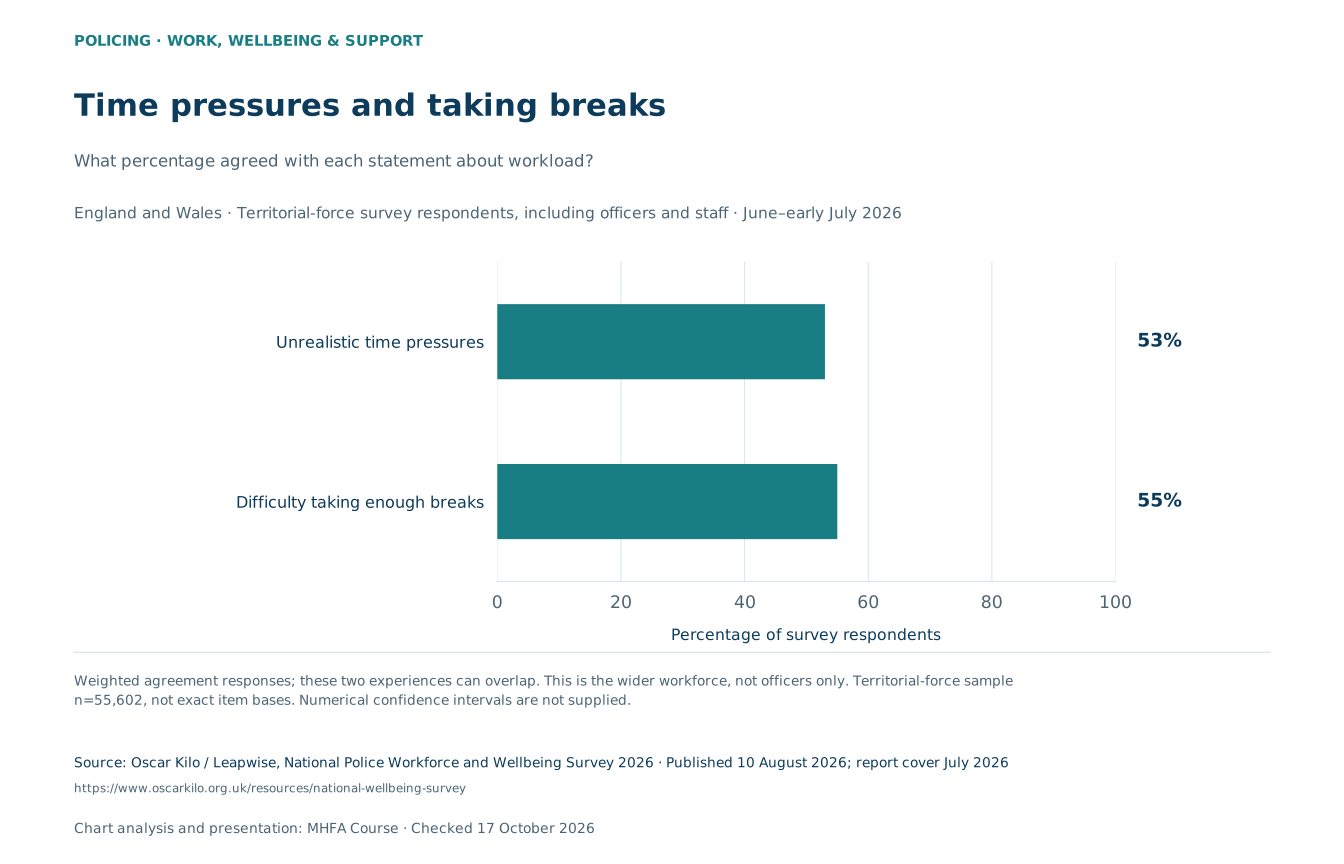
The experience questions ask how often something happened in the last 12 months; the chart shows often or always. The separate workload questions measure agreement. People can appear in several response groups, so percentages should not be added.
Selected experiences of strain at work
Which experiences were reported often or always in the previous 12 months?
| Group / measure | percent |
|---|---|
| Fatigue or physical exhaustion | 56% |
| Working when too unwell | 35% |
| Stress about finances | 32% |
| Difficulty empathising with victims | 25% |
Selected self-reported experiences can overlap; they are not diagnoses. Territorial-force sample n=55,602, not exact item bases. Numerical confidence intervals are not supplied.
Time pressures and taking breaks
What percentage agreed with each statement about workload?
| Group / measure | percent |
|---|---|
| Unrealistic time pressures | 53% |
| Difficulty taking enough breaks | 55% |
Weighted agreement responses; these two experiences can overlap. This is the wider workforce, not officers only. Territorial-force sample n=55,602, not exact item bases. Numerical confidence intervals are not supplied.
A discrepancy inside the source report
The detailed wellbeing chart on page 17 reports 45% for emotional exhaustion and 44% for feeling burnt out because of the job. These two figures are reversed in the executive summary.
Because the two sections conflict, emotional exhaustion and burnout are excluded from the plotted figures and headline cards. The chart instead shows four other verified experiences. These remain self-reports, not diagnoses.
Dated officer-specific findings on stress, fatigue and leaving
In the PFEW 2024 survey, 44% described their job as very or extremely stressful. 61% said fatigue made some duties or responsibilities difficult to carry out, and 73% said it affected family or social life. These selected experiences can overlap and should not be added.
23% were actively looking for other work or planning to resign within two years. Among those considering leaving, 75% said the job’s impact on mental health and wellbeing had a major effect on their decision.
Intentions are not completed departures. The 75% result is conditional on considering leaving; it is not the proportion of all officers who leave because of mental ill health.
Exposure is different from a diagnosis.
Repeated exposure to traumatic events or material can be relevant to mental health. It does not mean that an officer will inevitably develop a disorder.
Historical Police Care UK research using a 2018 survey found symptoms consistent with PTSD or complex PTSD in around 20% of trauma-exposed police officers and staff. This is a selected, trauma-exposed research group and a symptom-screening result—not a current diagnosis rate for every officer in the UK.
Assessment should consider the individual’s symptoms, functioning and circumstances. A high score on a screening measure can indicate a need for further assessment; it does not replace that assessment or establish fitness for every duty.
Indirect exposure can matter.
Some specialist roles involve repeated contact with distressing material, including child-abuse investigations. This can warrant assessment and support, but it does not establish that every exposed worker develops secondary trauma or PTSD.
Working conditions also deserve attention.
Research using the 2018 survey found associations between poorer working conditions and complex-PTSD symptoms. These findings support attention to workload, support and working arrangements without proving that one procedure prevents every long-term harm.
The research does not provide a current ranking of psychological harm across all specialist units. Findings from construction, veterans or NHS staff should not be used as if they measured police officers.
What support looks like in the evidence.
Concerns about confidentiality, stigma or career consequences can affect willingness to seek help. Support needs to be considered in the context of the person’s role and circumstances.
Workforce responses about colleagues, managers or services can help describe the environment. They are not a guarantee that every person can obtain suitable care, or evidence that a particular intervention reduces national rates of illness.
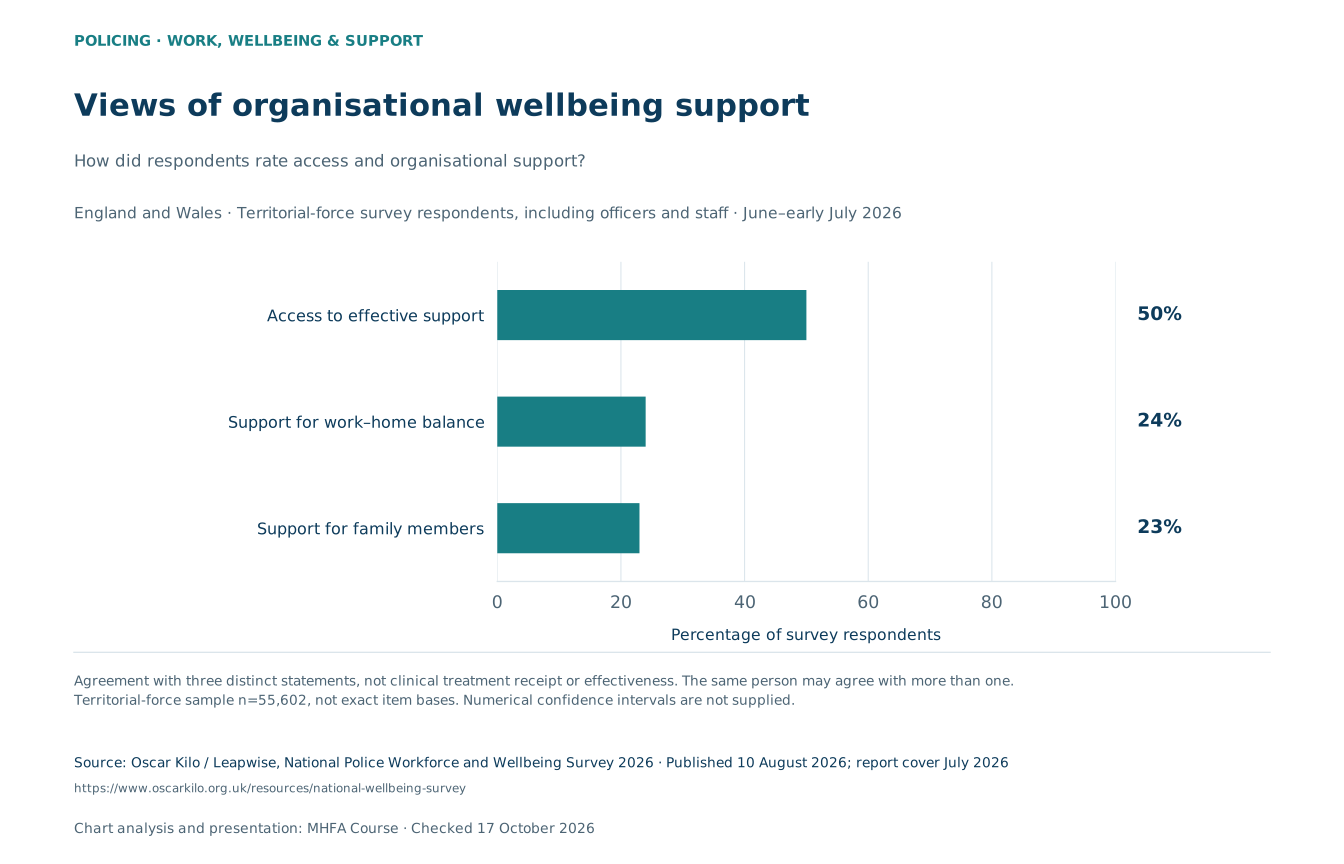
The agreement chart asks about access and organisational support. Responses outside agreement include neutral responses as well as disagreement, so the 50% access figure does not mean that all of the remaining 50% were unable to obtain support.
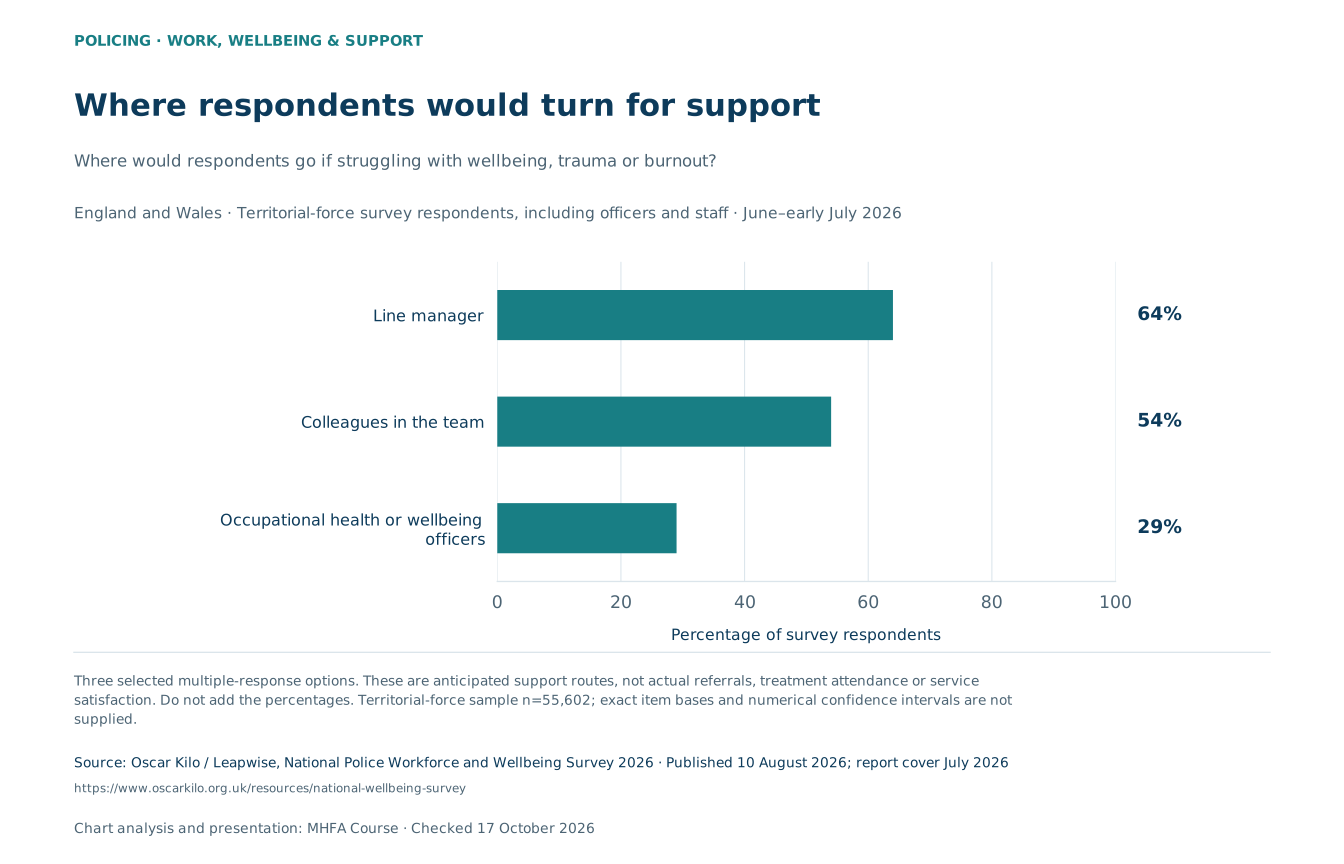
The following two charts ask where someone would go if they struggled, and what makes support difficult to access. They are selected multiple-response options, not complete distributions of treatment received.
Views of organisational wellbeing support
How did respondents rate access and organisational support?
| Group / measure | percent |
|---|---|
| Access to effective support | 50% |
| Support for work–home balance | 24% |
| Support for family members | 23% |
Agreement with three distinct statements, not clinical treatment receipt or effectiveness. The same person may agree with more than one. Territorial-force sample n=55,602, not exact item bases. Numerical confidence intervals are not supplied.
Where respondents would turn for support
Where would respondents go if struggling with wellbeing, trauma or burnout?
| Group / measure | percent |
|---|---|
| Line manager | 64% |
| Colleagues in the team | 54% |
| Occupational health or wellbeing officers | 29% |
Three selected multiple-response options. These are anticipated support routes, not actual referrals, treatment attendance or service satisfaction. Do not add the percentages. Territorial-force sample n=55,602; exact item bases and numerical confidence intervals are not supplied.
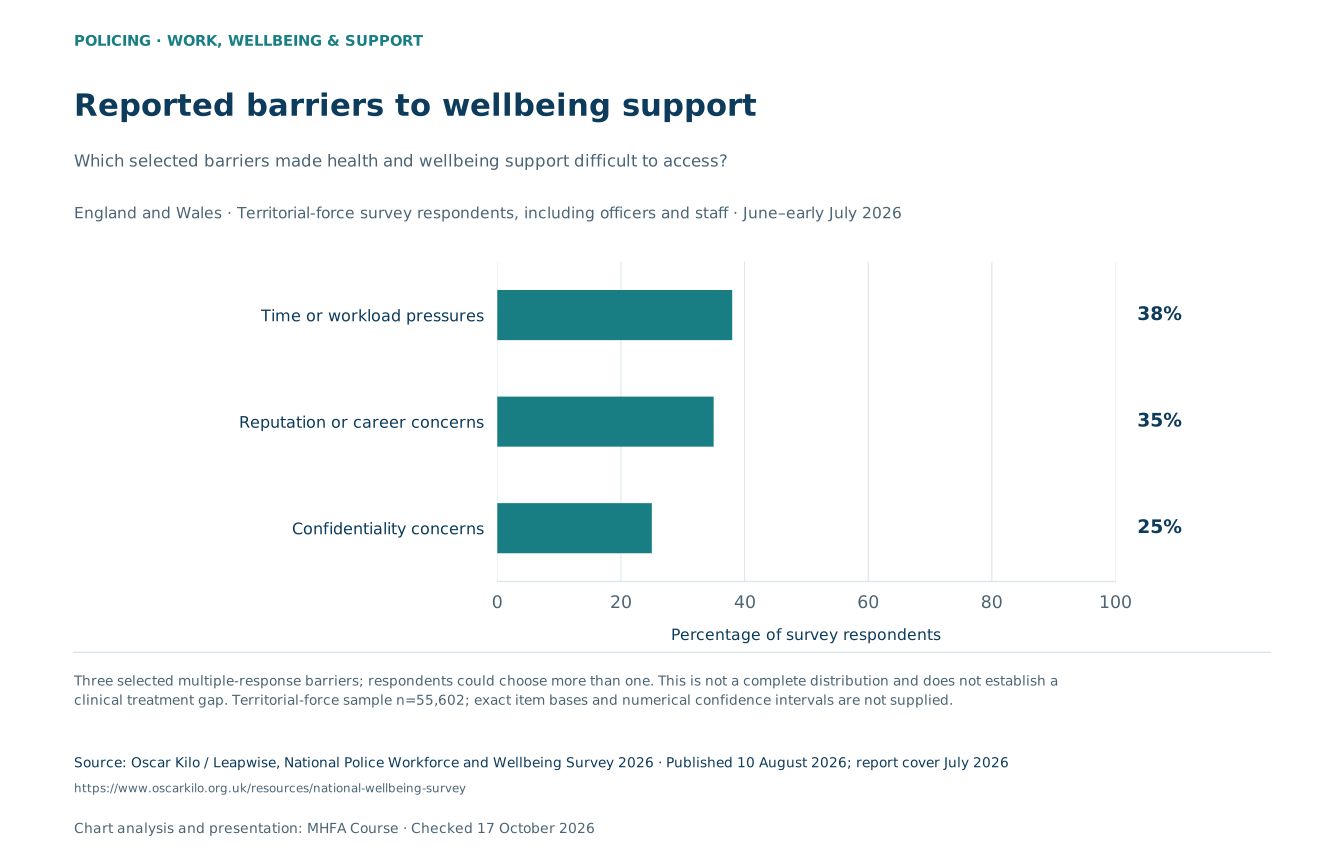
Reported barriers to wellbeing support
Which selected barriers made health and wellbeing support difficult to access?
| Group / measure | percent |
|---|---|
| Time or workload pressures | 38% |
| Reputation or career concerns | 35% |
| Confidentiality concerns | 25% |
Three selected multiple-response barriers; respondents could choose more than one. This is not a complete distribution and does not establish a clinical treatment gap. Territorial-force sample n=55,602; exact item bases and numerical confidence intervals are not supplied.
Disclosure and confidentiality
Confidentiality arrangements and their limits should be explained clearly. A disclosure should be considered individually, with appropriate occupational-health advice where needed.
Fitness for a particular duty
Mental-health symptoms do not automatically make an officer unfit for every duty. Safety-sensitive roles may require an individual assessment. Support, adjustments and any role restrictions should reflect the person’s circumstances.
Mind’s Blue Light Programme developed mental-health resources and support for emergency-service personnel. Programme activity and participant feedback are different from evidence that a particular course reduces national rates of illness or suicide.
What the same report shows for officers specifically
Among officer respondents, the three selected anticipated support routes were line managers (60%), team colleagues (54%) and occupational health or wellbeing officers (27%).
The selected officer-reported barriers were time or workload (45%), reputation or career concerns (43%) and confidentiality concerns (29%). These are officer-only results from the same 2026 report, distinct from the wider-workforce charts. Multiple responses were allowed; exact item bases and confidence intervals are not supplied.
Reading absence and suicide data carefully.
Administrative records and mortality statistics answer different questions from a wellbeing survey. The dates, people counted and definitions need to match before a comparison can be meaningful.
At 31 March 2026, official Home Office records showed 3,358 full-time-equivalent officers on long-term sick leave in the 43 territorial forces of England and Wales, equivalent to 2.3% of officers.
This is a snapshot of medical absence lasting more than 28 calendar days. It includes physical and psychological conditions and is not a mental-health-specific figure, an annual count of sickness episodes or days lost. The release was published on 22 July 2026.
Why an undated police-suicide ratio is not reliable
The sources reviewed do not establish a current annual UK comparison between police suicides and deaths in the line of duty. Such a comparison needs a consistent definition of serving officers, a stated period and complete records. An undated ratio should not be used.
Occupational suicide statistics and fatal workplace-injury data are collected for different purposes. Age ranges, occupation coding and registration delays can differ. A comparison reported for construction cannot be used as a proxy for policing.
Our suicide statistics guide explains the broader measures and limitations. Our men’s mental health statistics guide provides separate context for men, who make up the majority of the police workforce.
Our Mental Health First Aid courses are widely used in emergency services settings, providing the practical skills needed to support colleagues through mental health difficulties and to build cultures where it is safe to ask for help.
Using police mental-health statistics responsibly.
Are these figures for every police officer in the UK?
No. Each survey has a defined geography, workforce and responding sample. Officer-only findings should not be treated as staff findings, and a report on England and Wales is not automatically a UK total. The scope appears beside each chart.
Does a wellbeing difficulty mean a clinical diagnosis?
No. Reporting stress, low mood or a wellbeing difficulty is different from screening for a condition and from receiving a diagnosis after assessment. A survey percentage should retain the wording of the question it measures.
Can these surveys be combined into a trend?
Only where the publisher supports a comparable question, population and method. An older officer-only survey and a newer wider-workforce survey should not be joined simply because both discuss mental health.
Does trauma exposure inevitably lead to PTSD?
No. Exposure and responses vary. The historical trauma-exposed research findings are not a diagnosis rate for every officer, and screening is not a substitute for individual assessment.
Does seeking help automatically make someone unfit for police work?
No. Fitness decisions should consider the individual, their functioning and the duties involved. Safety-sensitive roles may require specific assessment; a general survey estimate cannot decide an individual case.
Do intentions to leave show how many officers actually left?
No. A survey question about plans or intentions is not an administrative count of departures. A reason reported by potential leavers also uses a different denominator from a question asked of all respondents.
Methods, uncertainty and responsible reuse
Charts reproduce verified source values with their populations, dates and question wording. All axes start at zero. Published uncertainty is retained where available; an absent confidence interval is not evidence of zero uncertainty.
Survey findings can be affected by who responds, what is asked and how the data are weighted. Whole-survey sample sizes are not substitutes for missing question-specific bases. A large sample alone does not remove possible non-response bias.
The downloadable files retain source locations and qualifications. Keep workforce coverage, reference periods and conditional denominators with each figure. Associations are not individual predictions or proof that a particular workplace factor caused a clinical condition.
Police mental health charts.
Keep the workforce context attached.
Download SVG and PNG charts, CSV data and methodology. Preserve the survey dates, participating workforce, questions and limitations alongside each figure.
Mental Health First Aid Course (2026). Police Officer Mental Health Statistics UK. Evidence checked 17 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/police-officer-mental-health-statistics-uk
Sources
Primary evidence and methodology. Checked 17 October 2026.
- Oscar Kilo: National Police Workforce and Wellbeing Survey 2026 results
- Oscar Kilo / Leapwise: National Police Workforce and Wellbeing Survey 2026 national report
- Oscar Kilo: national wellbeing survey collection
- PFEW / Social Market Foundation: Pay and Morale Survey 2024 headline report
- Police Care UK: Policing, The Job & The Life Survey 2018
- University of Cambridge: working conditions and PTSD research
- Mind: wellbeing and mental health support in emergency services
- College of Policing: wellbeing guidance
- Oscar Kilo: national consensus for police occupational health
- College of Policing: psychological risk management
- ONS: occupational suicide analysis and interpretation
- Home Office, Police workforce, England and Wales: 31 March 2026
- Home Office, User guide to police workforce statistics