
Construction Worker Mental Health Statistics UK: 2026 Facts, Data & Key Insights
Construction worker mental health statistics UK
What the evidence tells us about people working in construction—and the limits of the numbers often used to describe their mental health.

reported stress every day in the previous year
CIOB 2025 voluntary survey. Respondents’ experiences, not a national clinical prevalence estimate.reported access to a mental health first aider
CIOB 2025 respondents. This measures reported availability, not the effectiveness of training.were not confident at all about approaching a colleague who might be struggling
CIOB 2025 respondents. A further 7% were not very confident.Construction has many roles. The evidence has different boundaries.
Construction employers and workers have reasons to take mental wellbeing seriously. But a percentage from a workforce survey, a work-related illness rate and a suicide mortality comparison answer different questions.
Construction includes many occupations, contracts and working environments. Experiences on one project or among a group of managers cannot automatically be applied to every tradesperson, labourer, site team or self-employed worker.
The charts below present the latest verified CIOB study alongside clearly separated official context. They describe what was measured without turning selected survey responses into a single UK-wide prevalence estimate.
Workforce surveys
A voluntary survey describes the people who took part. Respondents’ job roles, location and recruitment affect how far the findings can be applied to the wider workforce.
Occupational analysis
Death-registration analysis uses specific occupations, ages and periods. A historical occupational comparison is not a current annual total for the construction industry.
Mental health
Reported stress, fatigue or low mood is different from a clinical diagnosis. Group figures help describe a situation; they cannot determine an individual person’s needs.
Who took part in the CIOB survey?
CIOB’s 2025 report analysed 865 responses collected between December 2024 and March 2025. 87% of respondents were UK-based and 13% were international. The sample included many managers.
Participation was voluntary. People who chose to answer may differ from those who did not, and the study is not a representative survey of everyone working in UK construction.
The whole analysed sample of 865 is not automatically the valid-answer base for every question. Exact item bases and numerical confidence intervals are not published for the charted comparisons, so they are left unspecified rather than estimated.
Results can still identify issues worth examining. Their value is strengthened by keeping the respondent population visible, rather than describing the percentages as rates for the whole industry.
Stress and fatigue in everyday working life.
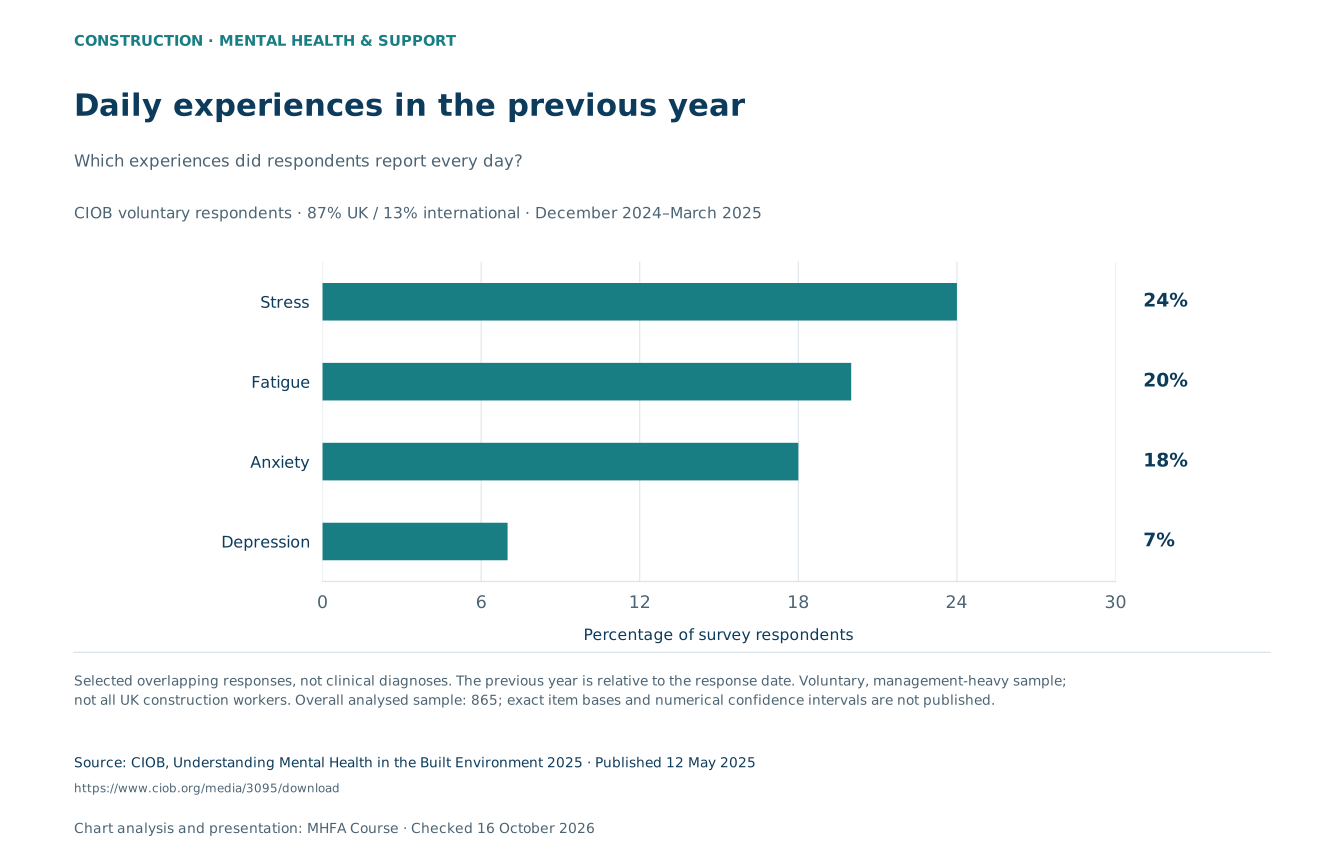
In CIOB’s 2025 survey, 24% of respondents reported stress daily in the previous year. 20% reported daily fatigue, 18% daily anxiety and 7% daily depression.
These are responses to questions about experiences and their frequency. They are not diagnoses established by a clinical assessment. The categories also overlap: one person could report several experiences.
“Daily” matters. These values should not be relabelled as the proportion who experienced a symptom at any point during the year, or as the proportion who were experiencing it on the survey date.
Daily experiences in the previous year
Which experiences did respondents report every day?
| Group / measure | percent |
|---|---|
| Stress | 24% |
| Fatigue | 20% |
| Anxiety | 18% |
| Depression | 7% |
Selected overlapping responses, not clinical diagnoses. The previous year is relative to the response date. Voluntary, management-heavy sample; not all UK construction workers. Overall analysed sample: 865; exact item bases and numerical confidence intervals are not published.
How the report describes suicidal thoughts
The report’s frequency chart and narrative indicate that 27% of respondents reported suicidal thoughts at least once in the previous year. CIOB’s accompanying press release gives 28%. This guide uses the report’s 27% figure and makes the discrepancy explicit rather than silently combining the two versions.
This is a sensitive self-reported experience among survey participants. It is neither a suicide death rate nor an estimate of how many people across the UK construction workforce will die by suicide. It should not be compared directly with the occupational mortality statistics below.
What respondents said about workplace culture.
The survey also asked about aspects of working culture. The next chart shows selected issues respondents rated as moderately or extremely stressful.
The most frequently reported of these selected issues was a lack of understanding of job roles, at 61%. Conflicting demands were reported by 59%. Pressure to attend regardless of circumstances or health and a lack of trust in management each stood at 57%.
Inadequate managerial support was reported by 56% and feeling undervalued by 55%. These responses can overlap and do not form a set of mutually exclusive causes.
Selected pressures in workplace culture
Which aspects did respondents rate moderately or extremely stressful?
| Group / measure | percent |
|---|---|
| Unclear job roles | 61% |
| Conflicting demands | 59% |
| Pressure to attend despite circumstances | 57% |
| Lack of trust in management | 57% |
| Inadequate managerial support | 56% |
| Feeling undervalued | 55% |
Six selected role and management items from Table 7; not a complete ranking. Responses overlap. Voluntary, management-heavy sample; no causal conclusion or national prevalence estimate. Exact item bases and numerical confidence intervals are not published.
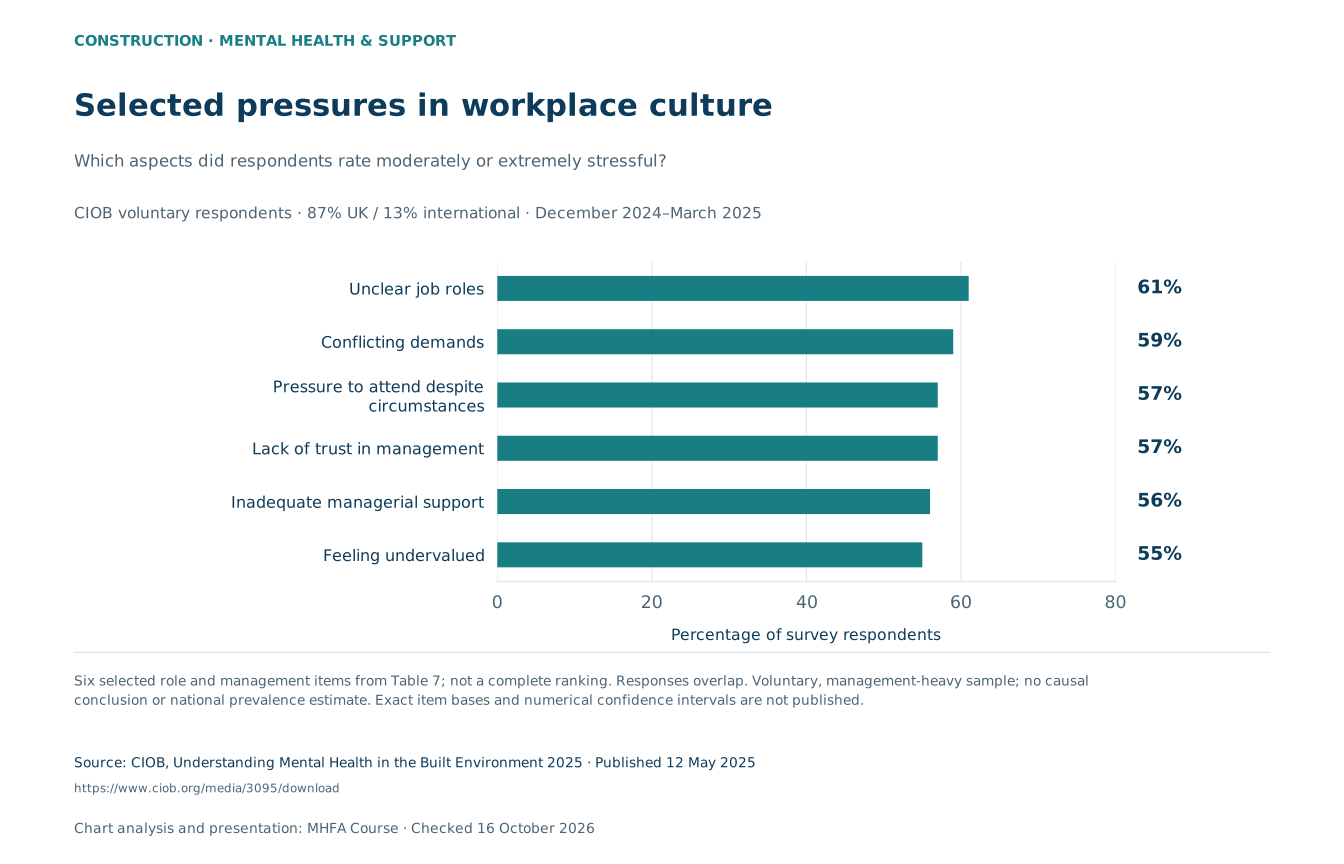
These findings identify respondents’ perceptions. They do not establish how much any single workplace factor caused a mental-health outcome, and they should not be used to assign blame for an individual person’s illness or suicide.
For an employer or site team, the useful next question is whether comparable concerns appear in its own conversations, risk assessments and working arrangements. Local evidence is needed to understand which changes would address the circumstances of that workforce.
A separate official measure: work-related illness.
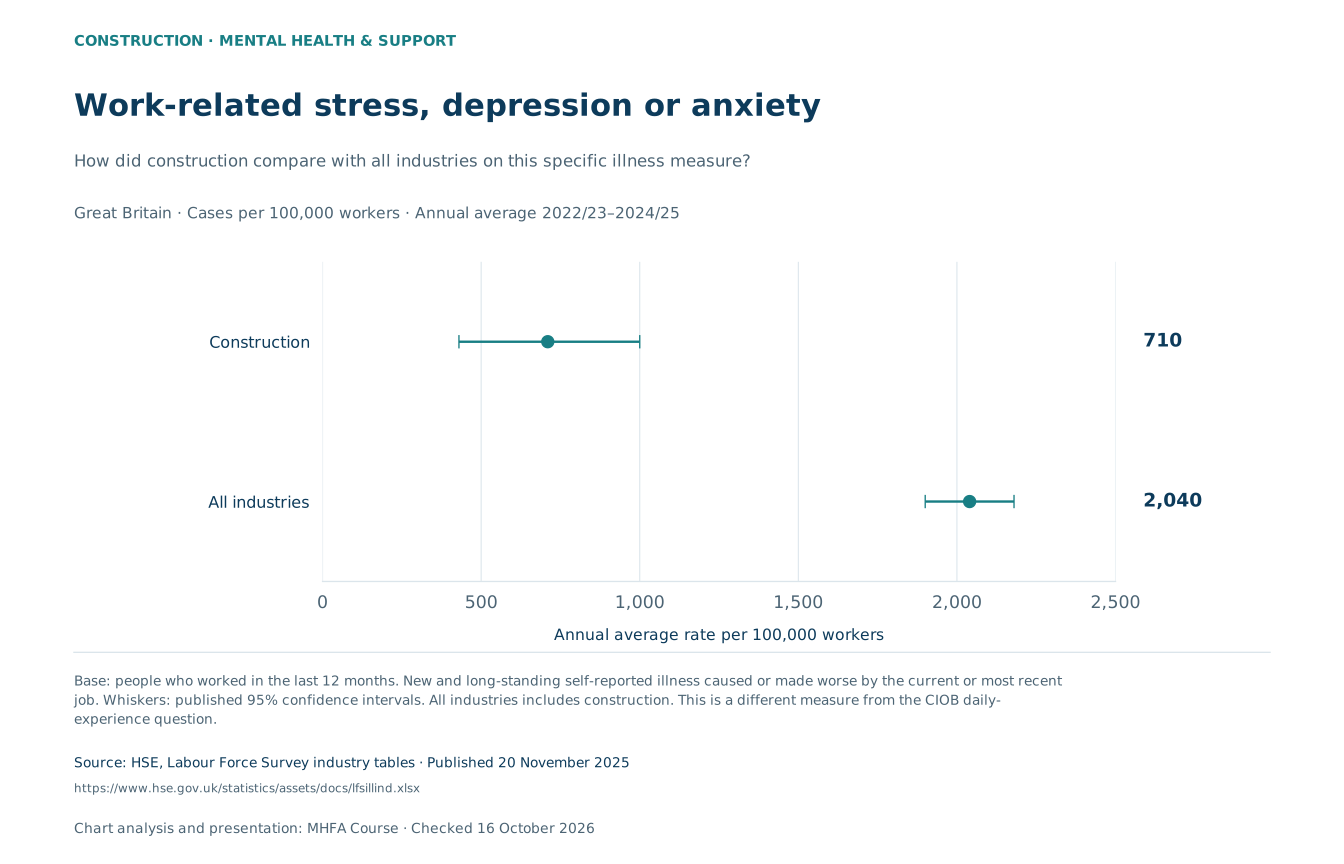
HSE’s Labour Force Survey estimate for construction is 710 cases per 100,000 workers, compared with 2,040 across all industries, as an annual average over 2022/23–2024/25 in Great Britain.
The base is people who worked in the last 12 months, and the all-industries comparison includes construction. This measure covers new and long-standing self-reported stress, depression or anxiety caused or made worse by the current or most recent job. It is different from reporting stress daily in a voluntary survey. The figures are not contradictory estimates of the same question.
The chart shows published 95% confidence intervals: 430–1,000 for construction and 1,900–2,180 for all industries. A lower industry estimate does not describe every worker’s experience or remove the need to assess and manage work-related stress.
Work-related stress, depression or anxiety
How did construction compare with all industries on this specific illness measure?
| Group / measure | per 100,000 workers | 95% interval |
|---|---|---|
| Construction | 710 | 430–1,000 |
| All industries | 2,040 | 1,900–2,180 |
Base: people who worked in the last 12 months. New and long-standing self-reported illness caused or made worse by the current or most recent job. Whiskers: published 95% confidence intervals. All industries includes construction. This is a different measure from the CIOB daily-experience question.
Support needs to be available—and approachable.
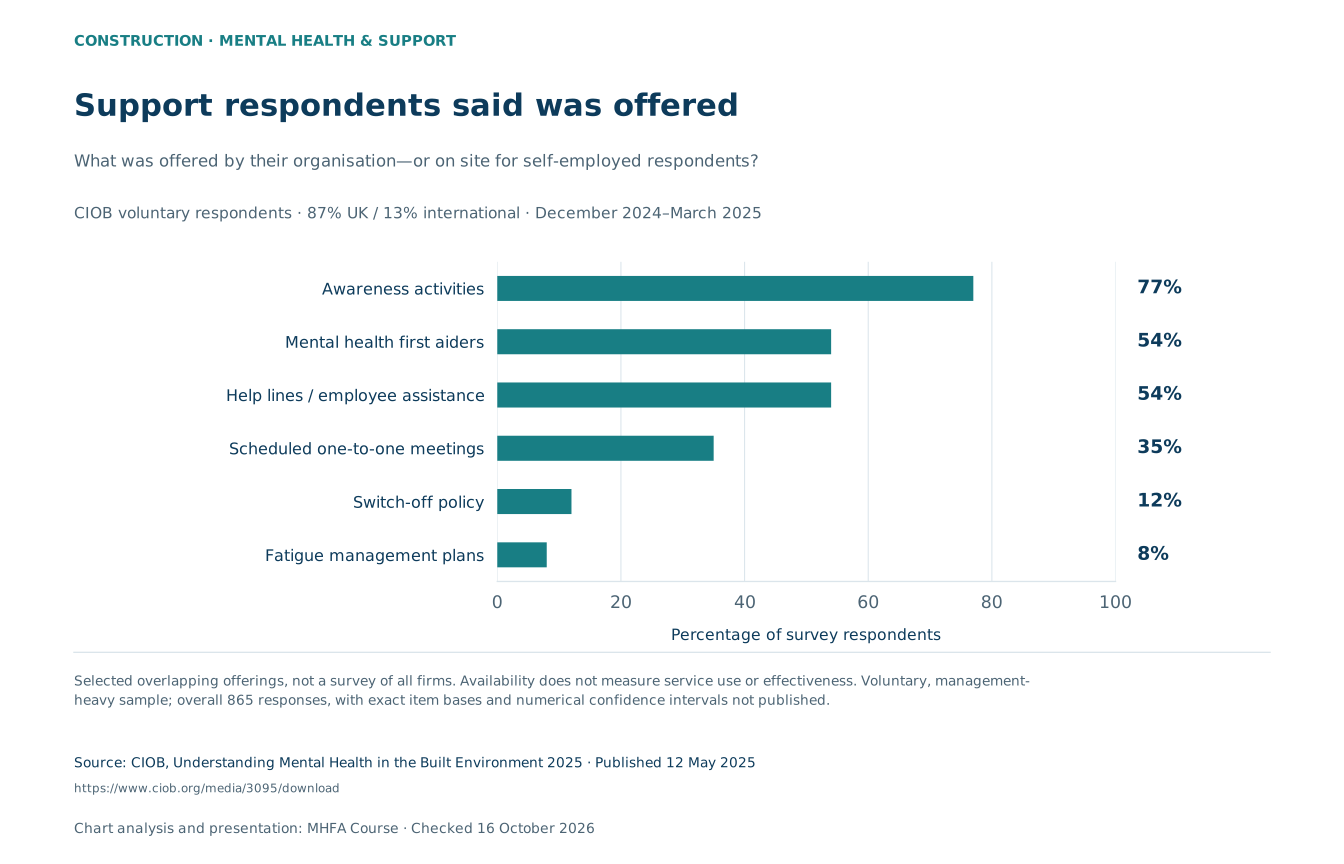
Respondents reported several kinds of support at work. 77% said they had been encouraged to take part in mental-health awareness activities. 54% reported mental health first aiders and 54% reported an employee assistance programme or help line.
Scheduled one-to-one meetings with managers were reported by 35%. A policy supporting switching off outside working hours was reported by 12%, and fatigue-management plans by 8%.
These are selected offerings reported by respondents. They are not an independent audit of employers, and the same participant could report more than one type of support. Availability also does not establish whether a service is accessible, used, trusted or effective.
Support respondents said was offered
What was offered by their organisation—or on site for self-employed respondents?
| Group / measure | percent |
|---|---|
| Awareness activities | 77% |
| Mental health first aiders | 54% |
| Help lines / employee assistance | 54% |
| Scheduled one-to-one meetings | 35% |
| Switch-off policy | 12% |
| Fatigue management plans | 8% |
Selected overlapping offerings, not a survey of all firms. Availability does not measure service use or effectiveness. Voluntary, management-heavy sample; overall 865 responses, with exact item bases and numerical confidence intervals not published.
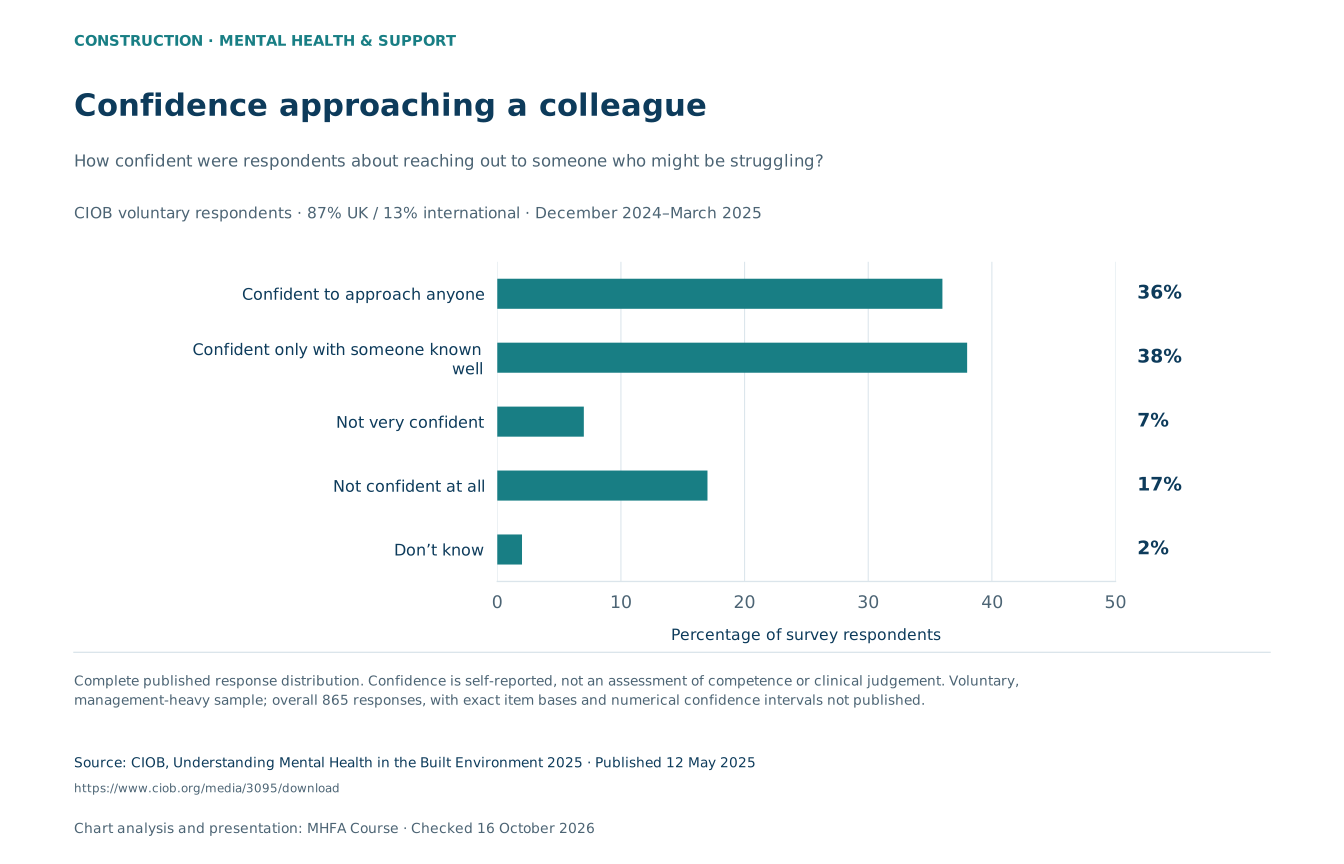
Confidence approaching a colleague
How confident were respondents about reaching out to someone who might be struggling?
| Group / measure | percent |
|---|---|
| Confident to approach anyone | 36% |
| Confident only with someone known well | 38% |
| Not very confident | 7% |
| Not confident at all | 17% |
| Don’t know | 2% |
Complete published response distribution. Confidence is self-reported, not an assessment of competence or clinical judgement. Voluntary, management-heavy sample; overall 865 responses, with exact item bases and numerical confidence intervals not published.
Confidence and change over time
When asked about approaching a colleague they thought might be struggling, 36% said they were confident approaching anyone, while 38% were confident only if they knew the colleague well. 7% were not very confident, 17% were not confident at all and 2% did not know.
The 17% figure therefore describes the least-confident response, not everyone who lacked confidence. Familiarity with a colleague matters to how these categories are interpreted.
The 2025 report compares 54% reporting access to a mental health first aider with 35% in the 2020 survey. The surveys involved different voluntary samples. This is evidence of different reported availability in the two studies, not proof that a particular training programme improved national mental-health outcomes.
Support after distress has developed and prevention of harmful working conditions serve different purposes. Neither should be treated as a substitute for the other.
Reading occupational suicide statistics carefully.
ONS’s clearly dated occupational analysis found elevated suicide mortality in some male construction occupations. It covered deaths registered in England during 2011–2015 among people aged 20–64.
For male workers in elementary construction occupations, the mortality ratio was about 3.7 times the male national comparison in that historical analysis. This is a specific occupation and period; it does not apply to every person working in construction today.
Occupation is not the same as industry. Someone’s occupation describes the work they do, while an industry classification describes the business activity of their employer. The distinction matters when comparing ONS occupation statistics with HSE industry statistics.
Why an unmatched suicide-to-injury ratio is misleading
Suicide registrations and fatal workplace injuries use different definitions, reporting systems and populations. A comparison needs matching age coverage, geography, period and definitions of construction work.
Dividing an occupational suicide total by an industry fatal-injury total cannot establish a current “ten times” risk for an individual construction worker. A death-registration year also does not necessarily identify the year in which each death occurred.
Suicide has multiple influences. An occupational association does not show that a person’s job was the cause, or predict what will happen to someone in that occupation.
Newer counts do not replace the historical risk comparison
ONS has also published provisional occupational suicide counts for 2023 and 2024 in England and Wales, released on 31 March 2025. Those newer counts do not provide a verified replacement for the historical 3.7 standardised mortality ratio used here.
Counts and standardised risk comparisons answer different questions. This guide does not construct a new construction-wide risk estimate from the provisional tables or splice their newer occupation classification into the older analysis.
Look at working conditions as well as individual support.
The practical value of these figures is to prompt specific questions about working conditions, communication and access to support. They do not prescribe a single solution for every site.
Financial and contractual uncertainty
Self-employment and short contracts can affect income security and access to employer-provided support. Employment status and entitlements vary; it is inaccurate to assume every construction worker lacks sick pay or occupational-health support.
Hours, travel and time away
Long hours, travel and accommodation away from home can affect rest and relationships. The demands of the role and the individual’s circumstances both matter.
Communication and workplace culture
Stigma and expectations about coping can make conversations difficult. Employers should examine their own culture without assuming all men or all construction workplaces respond in the same way.
Individual support and adjustments
People may need different forms of communication, support or adjustment, including neurodivergent workers. Responses should reflect the person’s needs rather than an assumed profile of the workforce.
CIOB recommends attention to workload, working conditions, management support and access to help. HSE guidance also makes managing work-related stress part of employers’ health-and-safety responsibilities.
A conversation or training programme should not be presented as a guaranteed way to reverse a national trend. Prevention, appropriate professional help and everyday management practices have different roles.
The £51 billion estimate is economy-wide
Deloitte’s 2024 report estimated around £51 billion in annual costs to UK employers from poor mental health, using a model covering the wider UK economy.
It does not quantify construction’s share. Allocating that headline amount to construction without a separate defensible model would create an unsupported sector estimate. Likewise, a modelled average benefit from interventions is not a guaranteed return for any particular course or employer.
What construction mental-health statistics can tell us.
Do these percentages describe all UK construction workers?
No. The CIOB study was voluntary, included international respondents and had a particular mix of job roles. Its figures describe the analysed responses, not representative prevalence among every UK construction worker.
Does daily anxiety mean a diagnosed anxiety disorder?
No. A self-reported experience and its frequency are different from a clinical assessment. The survey categories can overlap and should not be added together.
What does the historical 3.7 figure mean?
It refers to male elementary-construction workers aged 20–64 in England’s 2011–2015 occupational suicide analysis, compared with the male national population. It is not a current annual industry total or a figure for every construction occupation.
Does access to a mental health first aider prove an intervention works?
No. Reported availability does not measure uptake, quality or outcomes. Different voluntary survey samples cannot establish that one intervention caused a national change.
Why are some confidence intervals missing?
The CIOB report does not publish numerical intervals or exact item-valid sample sizes for these charts. The overall 865 analysed responses are not automatically the base for each question, so missing precision is not manufactured.
Why keep older occupational evidence?
It supports a specific, clearly dated finding about particular occupations. Its historical period is kept visible, rather than changing the year label or treating it as a present-day rate.
Methods, uncertainty and reuse
This guide presents published evidence visually; it is not a new survey. CIOB’s voluntary participant responses are kept separate from official occupational statistics.
All charts start at zero. Where a source does not publish numerical confidence intervals or exact question bases, the download records those as unavailable rather than inventing them from the overall sample size.
Keep the frequency threshold, population, period and recruitment method when reusing a chart. Do not add overlapping responses or treat a reported association as a causal effect.
Different surveys and changing samples make apparent differences over time harder to interpret. A change in reported support availability is not proof of a treatment effect or a reduction in national suicide risk.
Construction mental-health charts.
With their context intact.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the survey population, question, dates and limitations with every figure.
Mental Health First Aid Course (2026). Construction Worker Mental Health Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/construction-worker-mental-health-statistics
Sources
Primary evidence and methodology. Checked 16 October 2026.
- CIOB: Understanding Mental Health in the Built Environment 2025
- CIOB: 2025 report publication
- CIOB: 2025 press release
- CIOB: current research listing
- CIOB: May 2026 discussion of the 2025 findings
- ONS: suicide by occupation, England 2011–2015
- HSE: work-related stress and employer responsibilities
- HSE: identifying organisational stress risks
- Deloitte: 2024 UK employer-cost analysis
- HSE LFSILLIND industry tables
- HSE Construction statistics in Great Britain, 2025
- ONS suicide by occupation: 2023 and 2024, provisional
- UK Parliament written answer on latest occupation data