
Children's Mental Health Waiting Times UK: 2026 Facts, Data & Key Insights
Children’s mental health waiting times
What the latest evidence says about getting help, recorded waits and the support families may need along the way.

Open referral spells still awaiting a recorded first contact.
England · end of August 2026Aged 0–17 at referral; spells are not unique children.
Of those spells had been open for more than 52 weeks without a recorded first contact.
England · end of August 2026Denominator: 279,604 open referral spells.
Median elapsed wait among children still awaiting a second contact at year end.
England · 2024/25 analysisSnapshot at 31 March 2025; not an eventual total wait.
Which clock is being measured?
A headline waiting-list total can hide several different experiences. Some children have not yet had a first conversation; others have received an assessment or support but are waiting for a further step. A referral can remain open while care is being provided.
A referral
A request to a service creates a referral record. A person may have more than one referral. Counts of referrals and counts of children therefore need different labels.
An open referral
This is a status at a particular date. It can include someone already receiving care, so the total is not automatically the number waiting without support.
A first contact
A first conversation can happen before an assessment or treatment begins. A short wait to first contact does not necessarily mean every later stage happens quickly.
Assessment or treatment
These waits need their own start and end points. A clock ending under a statistical definition does not describe every aspect of a family’s experience.
The most useful questions are: who is counted, what starts the clock, and what stops it? A monthly snapshot of people still waiting is different from the waits of people who started receiving help during that month. An annual referral total measures activity over a period, rather than the size of a waiting list on one day.
What is a referral spell?
The NHS referral-spell measures group overlapping referrals, or referrals separated by no more than five days, within the same provider. The children and young people series is based on age 0–17 at referral, so some people counted may now be 18 or older. A spell is not an interchangeable count of individual children.
A recorded contact is not necessarily the start of a particular treatment, and missing or incomplete data can affect whether an event appears in a record. These measures are useful for monitoring access, but cannot establish everything a child has received from family, school, community or other services.
What do the access figures show?
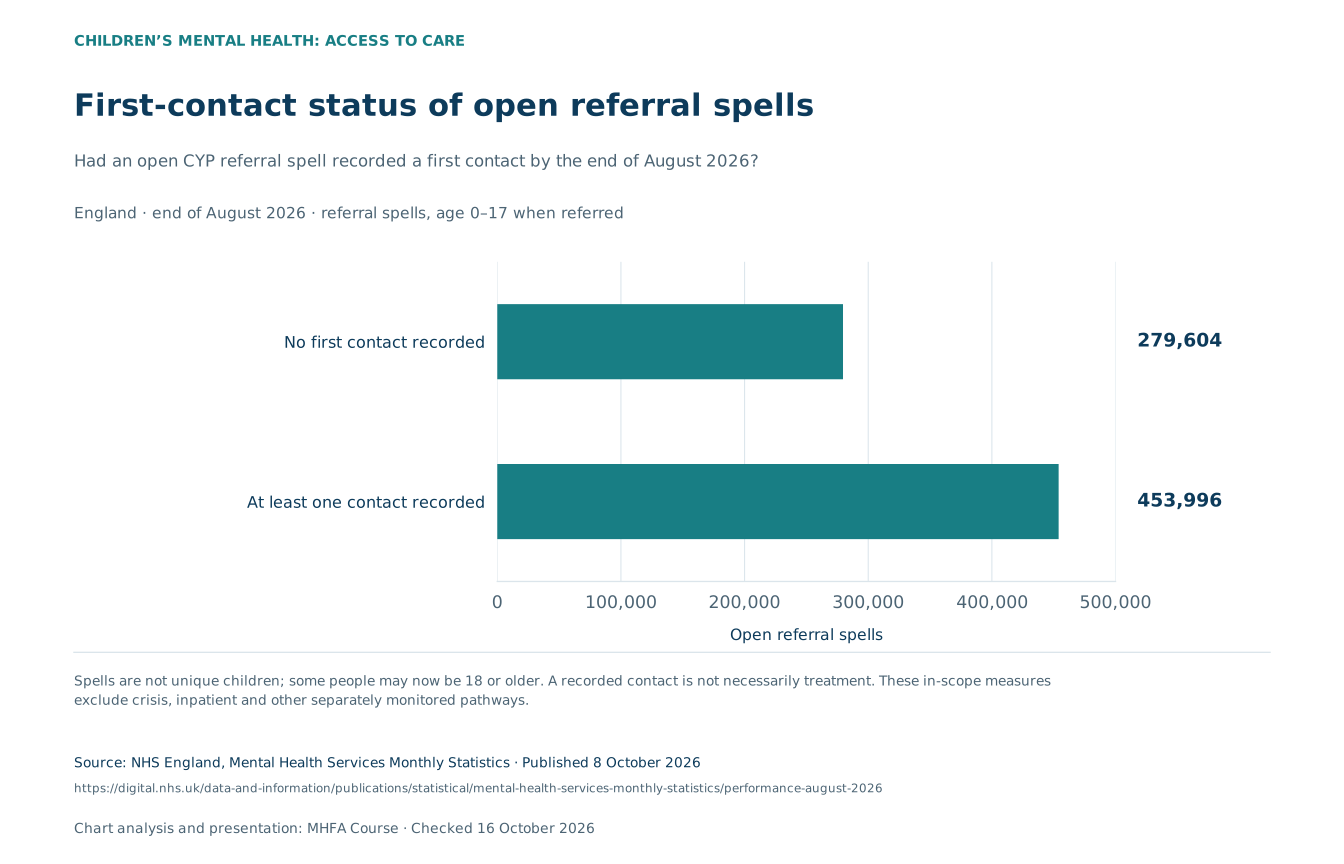
At the end of August 2026, England’s published children and young people referral-spell data recorded 733,600 open spells. Of these, 279,604 had no recorded first contact and 453,996 had at least one contact.
The categories describe recorded contact status. They should not be relabelled as “untreated” and “treated”: a contact can occur before an assessment or a longer course of care, and a record may not capture every source of support.
The separately published 506,475 people with an open referral to children and young people’s services is a people-based snapshot. It is not the denominator for the referral-spell charts.
Different age rules and units mean these totals should not be turned into a funnel.
First-contact status of open referral spells
Had an open CYP referral spell recorded a first contact by the end of August 2026?
| Group / measure | referral spells |
|---|---|
| No first contact recorded | 279,604 |
| At least one contact recorded | 453,996 |
Spells are not unique children; some people may now be 18 or older. A recorded contact is not necessarily treatment. These in-scope measures exclude crisis, inpatient and other separately monitored pathways.
How long had open first-contact waits lasted?
What proportion of open CYP referral spells awaiting a first contact had passed each threshold?
| Group / measure | % |
|---|---|
| More than 52 weeks | 44.2% |
| More than 78 weeks | 32.0% |
| More than 104 weeks | 22.3% |
The thresholds overlap: a wait beyond 104 weeks is also beyond 78 and 52 weeks. These are ongoing waits at the snapshot, not eventual total waits or predictions for new referrals.
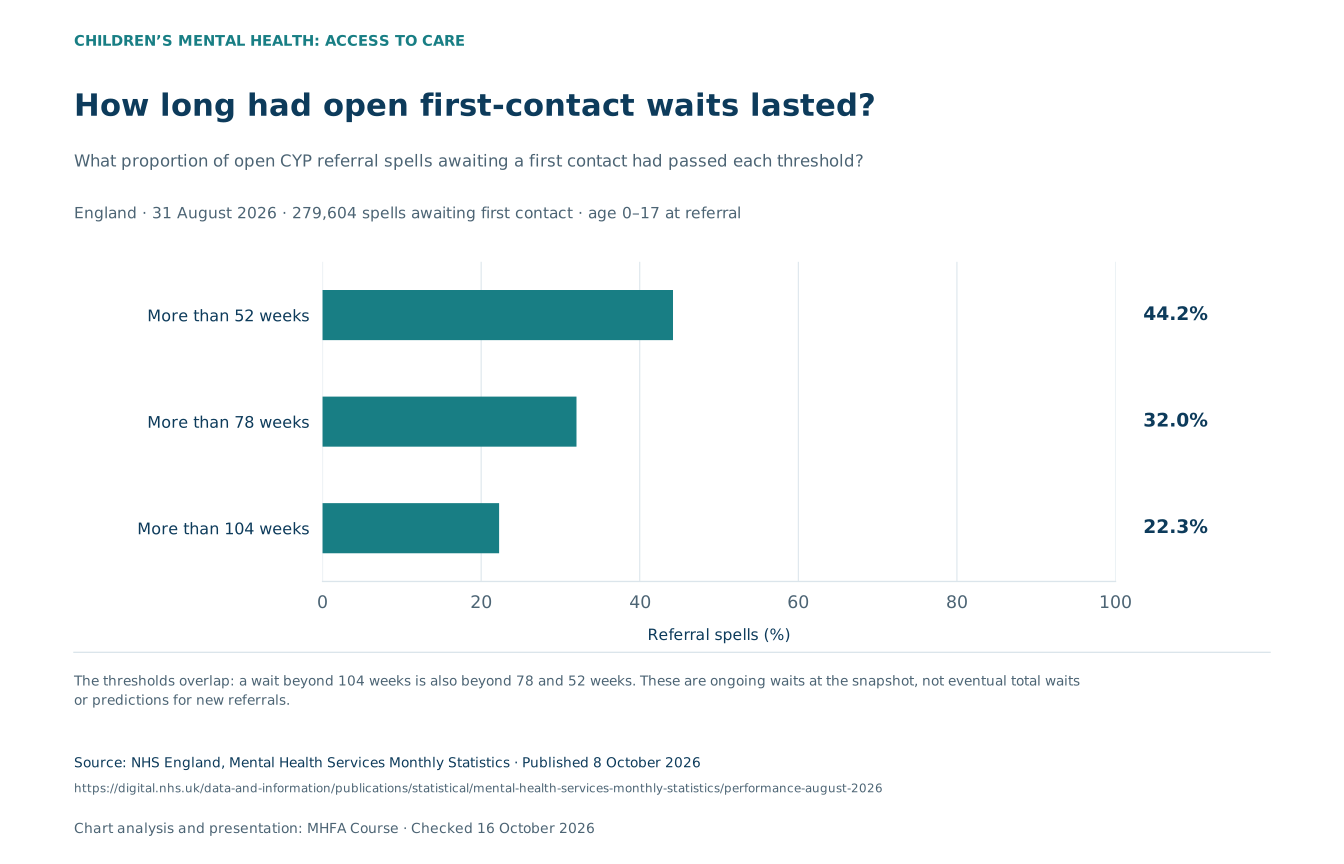
Among the 279,604 spells without a recorded first contact, 44.2% had been open for more than 52 weeks, 32.0% for more than 78 weeks and 22.3% for more than 104 weeks.
These thresholds overlap: a spell longer than 104 weeks is also longer than 78 and 52 weeks. The bars are cumulative, not separate groups. Adding them or showing them as a pie would misrepresent the data.
The figures describe waits still in progress at the snapshot date. They do not tell us the eventual total wait for each spell, nor the wait that a child newly referred today should expect.
A completed wait and an unfinished wait.
The Children’s Commissioner’s analysis of England’s 2024/25 NHS data gives a different annual view. It uses a second contact as a proxy for treatment, rather than the first-contact milestone in the monthly charts.
The median was 35 days for children reaching a second contact during the year. Among children still waiting at 31 March 2025, the median elapsed wait was 224 days.
One median concerns a completed wait to the chosen endpoint; the other concerns a wait still in progress. Neither is a maximum or a forecast for a particular child.
Completed waits and waits still in progress
How long had children waited for a second recorded contact in the annual analysis?
| Group / measure | days |
|---|---|
| Received a second contact during 2024/25 | 35 days |
| Still awaiting a second contact at year end | 224 days |
Different groups and endpoints: completed waits to second contact versus waits still in progress at 31 March 2025. Two contacts are a treatment proxy, not proof that needs were met. The medians do not describe a change over time.
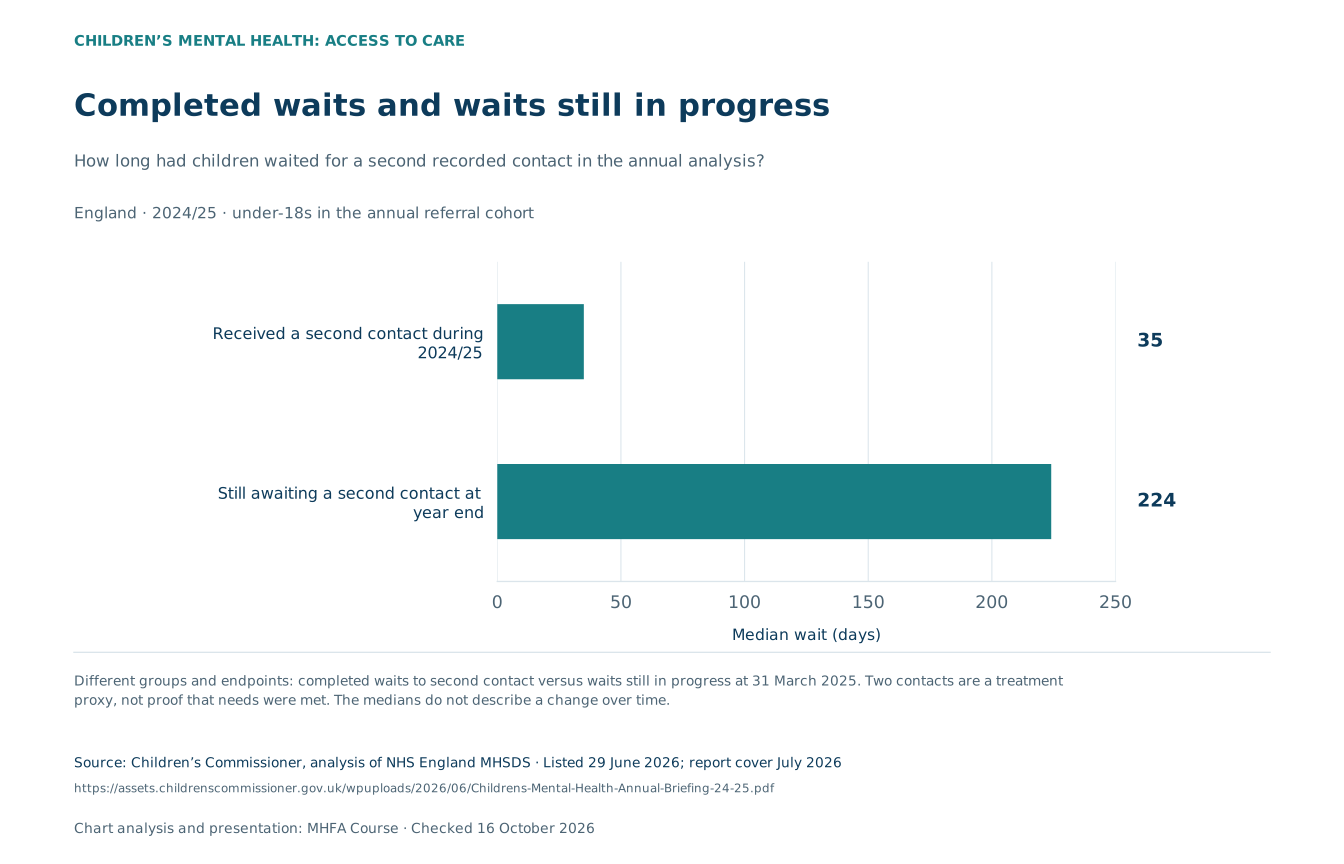
Two contacts are an imperfect proxy: they do not prove that a child’s needs have been met or describe the intensity of treatment. The annual cohort excludes children already in treatment at the start of the year, which also affects how it should be compared with other service totals.
The annual study and monthly NHS figures use different periods, populations and definitions. A change from 224 days to a newer monthly statistic would not establish that waiting times had improved or worsened.
Eating-disorder care has defined time targets.
Some pathways have specific access standards. For children and young people with an eating disorder in England, the measures shown here concern urgent referrals starting treatment within one week and routine referrals within four weeks. The target is 95% for each standard.
In June–August 2026, 356 of 452 urgent referrals met the one-week standard (78.8%). For routine referrals, 2,130 of 2,616 met the four-week standard (81.4%).
Eating-disorder referrals starting within the standard
Among referrals entering treatment, what share started within the relevant urgent or routine threshold?
| Group / measure | % |
|---|---|
| Urgent: treatment within 1 week | 78.8% |
| Routine: treatment within 4 weeks | 81.4% |
Separate standards and denominators: urgent within one week (356 of 452), routine within four weeks (2,130 of 2,616). The target is 95% for each. The method changed in April 2026; these figures are not joined to the old series.
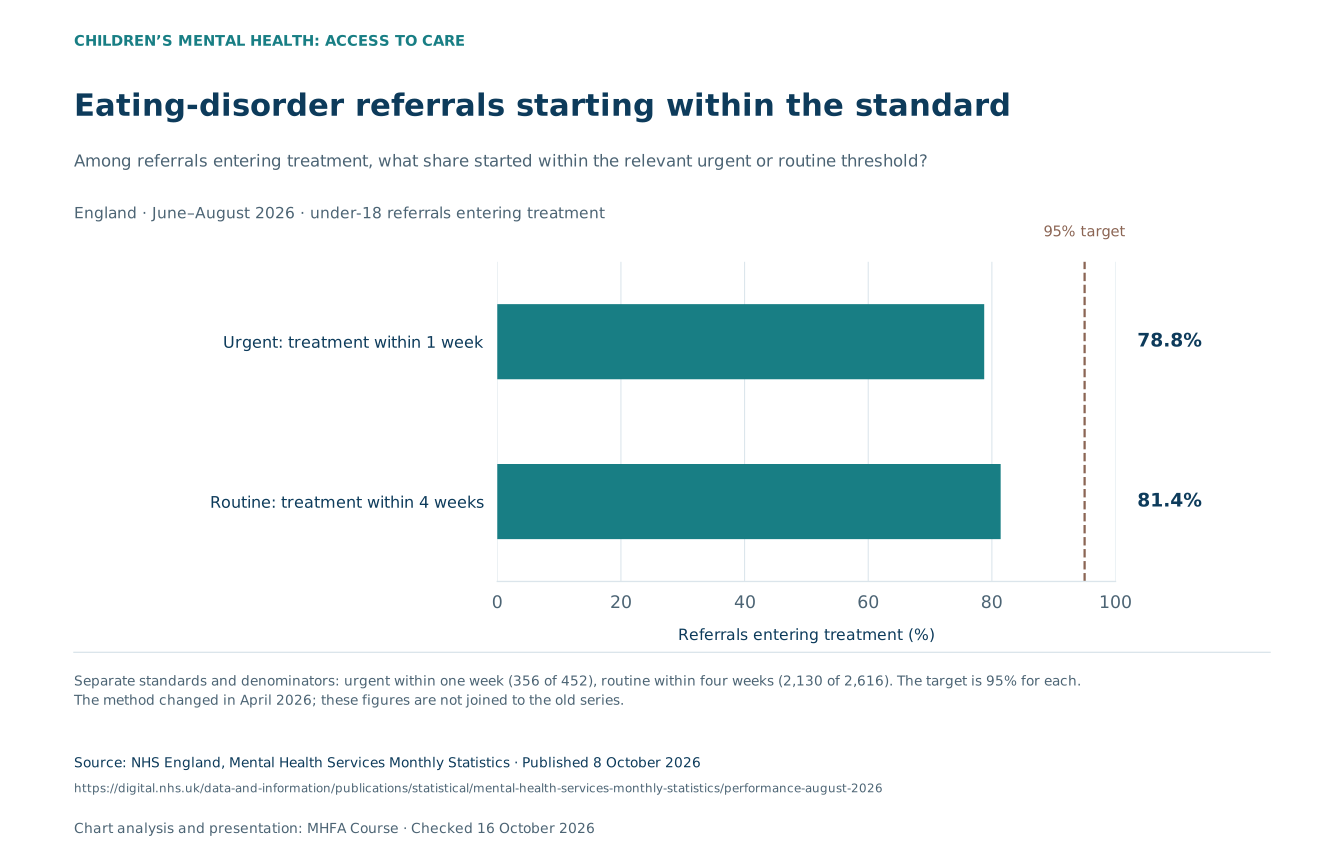
The two percentages have different time thresholds and denominators. They measure performance against each pathway’s standard, not a ranking of how quickly otherwise comparable children were treated.
The reporting method changed in April 2026. This guide does not draw a trend by joining the new figures to earlier figures produced under the previous method. Neither standard should be extended to every CAMHS referral.
ADHD referrals need a careful reading.
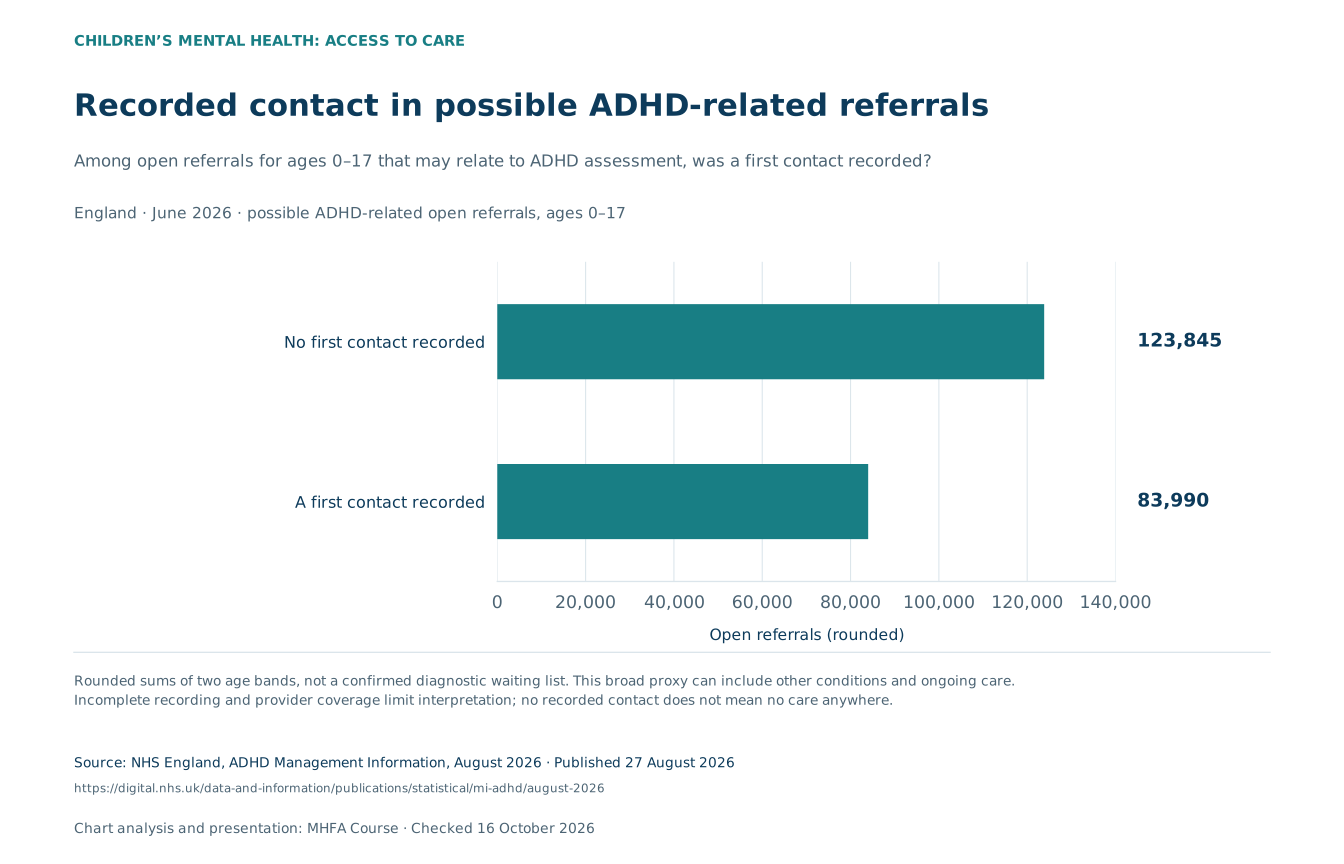
Possible ADHD-related assessment referrals are another distinct dataset. The June 2026 MHSDS age breakdown recorded a rounded total of 207,835 open referrals for ages 0–17: 123,845 with no recorded contact and 83,990 with a contact.
These are possible ADHD-related referrals identified through a proxy, not a complete, confirmed diagnostic waiting list. The records can include other conditions and ongoing care. The counts are rounded, and the MHSDS extract does not cover every community-health pathway.
How the child figures relate to the all-age total
The age totals were 4,665 referrals for ages 0–4 and 203,170 for ages 5–17, adding to 207,835 using rounded counts. The wider all-age release identified 780,430 possible referrals in MHSDS and up to 179,232 in community-health waiting-list data, producing a headline of up to 959,662.
That all-age combined headline is not a children-only total. Coverage, proxy definitions and provider submissions affect comparisons, so the figures should not be used to calculate the proportion of all children who have ADHD or to claim a precise diagnostic backlog.
Recorded contact in possible ADHD-related referrals
Among open referrals for ages 0–17 that may relate to ADHD assessment, was a first contact recorded?
| Group / measure | open referrals |
|---|---|
| No first contact recorded | 123,845 |
| A first contact recorded | 83,990 |
Rounded sums of two age bands, not a confirmed diagnostic waiting list. This broad proxy can include other conditions and ongoing care. Incomplete recording and provider coverage limit interpretation; no recorded contact does not mean no care anywhere.
Referral duration should not be presented as time without any contact, adjustments or support. Families can discuss a child’s needs with their school, special educational needs coordinator or GP while an assessment is pending. Difficulties do not themselves confirm ADHD, and support should respond to the child’s needs rather than assume a diagnosis.
For more on the condition and its measurement, see our ADHD statistics guide.
The wider context, kept separate.
How common are mental-health difficulties? England’s 2023 survey
England’s latest published follow-up survey found a probable mental disorder in 20.3% of 8–16 year olds in England in 2023, compared with 12.5% on the comparable measure in 2017. For ages 17–19, the estimates were 23.3% and 10.1%.
These are survey estimates of probable disorder, not referral or waiting-list counts. Rates were stable between 2022 and 2023; the younger group’s estimate had not more than doubled since 2017. The survey cannot attribute the pattern to a single cause.
What the self-harm admissions figure can and cannot show
England recorded 27,736 hospital admissions for intentional self-harm among 10–24 year olds in 2023/24. These are episodes of hospital care, not unique people or all self-harm in the community; the age group also includes young adults.
OHID did not update this indicator in May 2026 and warned that trends can reflect service provision as well as need. A falling admission count does not prove an improvement in children’s mental health, and it cannot demonstrate that a waiting-time change caused an outcome.
Funding and staffing: all-age figures, not a CAMHS budget
The March 2026 parliamentary statement forecast NHS mental health spending in England of £16.1 billion in 2026/27, compared with £15.7 billion in 2025/26. Its share of the recurrent baseline was forecast to fall from 8.68% to 8.40%, while spending increased in real terms. These are all-age mental health figures, not a ring-fenced children’s budget.
The government reported reaching its target of 8,500 additional mental health workers in April 2026. That is not a count of additional child specialists or proof of a particular effect on waiting times. Funding and staffing figures alone cannot establish why an individual child waits.
See our NHS mental health statistics guide for wider context.
Support should not stop while a child waits.
Ask which stage you are waiting for
Ask the service what the next appointment is intended to do, how long the expected wait is, and what support is available in the meantime. A first conversation, specialist assessment and ongoing treatment may have different timelines.
If you have not heard back, contact the service or ask the person who made the referral for its details. Local self-referral arrangements vary, so check what is available in your area rather than assuming every service uses the same route.
Report changes in need
Tell the service if symptoms, daily functioning or safety concerns change. A referral records information from a point in time; the team needs to know if circumstances have worsened since then.
Support from trusted adults, school staff and appropriate community services may help while a child waits. It should not be treated as a substitute for urgent assessment when there are immediate concerns.
Mental Health Support Teams provide help in participating schools and colleges, including support for mild to moderate difficulties. The June 2026 government data release estimated that MHST-supported settings accounted for 60% of pupils and further-education learners in England in 2025/26. This measures coverage of settings, not the percentage receiving treatment or meeting a waiting-time target.
Full national coverage is planned for 2029. That remains a future commitment, not evidence that every school already has a team. School and community support complement specialist care; they do not remove the need for urgent help when safety is at risk.
Self-harm needs a compassionate response and an assessment of physical and psychological needs. A national waiting-time figure cannot predict what will happen to one child, and these data cannot establish that a particular delay caused an episode. NICE advises against using simple risk categories to decide who receives care.
Further background is available in our self-harm statistics guide.
Making sense of the waiting-time figures.
Is there one national CAMHS waiting time?
No single figure describes every service, pathway or stage of care. Waiting for a first contact is different from waiting for assessment or treatment. This guide uses England’s published measures with their definitions, rather than presenting them as a single UK-wide average.
Does an open referral mean a child is waiting without care?
No. An open referral may include someone receiving support or treatment. To understand a waiting-time statistic, check whether it counts people, referrals or referral spells, and what event ends the recorded wait.
Does every CAMHS referral have an 18-week limit?
There is no single 18-week access standard covering every CAMHS pathway. NHS guidance describes rights for consultant-led care, while other pathways have their own standards or arrangements. The relevant service can explain what applies to a particular referral.
Can these figures tell a family how long they will wait?
They describe groups and recorded activity, not a forecast for an individual. A median is the midpoint of the measured waits, not a maximum. A person’s needs, urgency, pathway and local service all matter when discussing the next step.
Can a child receive support before an ADHD assessment?
Families can discuss needs and suitable support with their child’s school and health professionals while waiting. A pending assessment does not mean nothing can be discussed or adjusted. Urgent concerns should be acted on rather than held until a routine diagnostic appointment.
Methodology and limits
The main charts use published England administrative data and the Children’s Commissioner’s analysis of NHS records. Administrative counts depend on coding, submissions and coverage. They are not sample-survey estimates; missing confidence intervals should not be interpreted as proof that records are complete or error-free.
Counts, percentages and medians retain their own denominators and reference dates. Referral spells are not unique children; possible ADHD-related referrals are not confirmed diagnoses. The long-wait thresholds are cumulative. Annual completed waits and waits still in progress are separate groups, and ongoing waits are not eventual durations.
Charts use zero-based axes and published precision suitable for reading. Downloads retain underlying values, source locators and any reported numerators and denominators. This guide is an original visual presentation of published evidence, not a new survey or a forecast of a particular family’s wait.
Waiting-time charts.
The definitions travel with them.
Download the charts as SVG and PNG, with the underlying CSV data and methodology. Keep the population, period and clock definition with each figure when sharing it.
Mental Health First Aid Course (2026). Children’s Mental Health Waiting Times UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/childrens-mental-health-waiting-times-uk
Mental Health First Aid in education settings
Equipping education staff with Mental Health First Aid skills is one of the most cost-effective ways to ensure that children showing early signs of mental health difficulties are identified and supported before they reach crisis point.
Our Mental Health First Aid courses include specialist provision for education settings, helping teachers and support staff develop the awareness, skills, and confidence to act early when children are struggling.
Sources
Primary evidence and methodology. Checked 16 October 2026.
- NHS England: Mental Health Services Monthly Statistics, Performance August 2026August 2026 performance; published 8 October 2026. Some measures use a three-month period.
- NHS England: Children and young people referral-spell definitions
- Children’s Commissioner: Children’s and Young People’s Mental Health Services 2024–252024/25 data. Publication listing: 29 June 2026; the report cover says July 2026.
- NHS England: Mental health access and waiting-time standards
- NHS England: Eating-disorder waiting-time method, April 2026 changesPublished 18 May 2026.
- NHS England: ADHD Management Information, August 2026June 2026 referral data; published 27 August 2026.
- NHS England: ADHD data interpretation and coveragePublished 14 May 2026.
- Department for Education: Mental Health Support Team coverage and experiencesPublished 10 June 2026.
- Department for Education: Mental Health Support Team data releasePublished 10 June 2026.
- NHS England: Mental Health of Children and Young People in England 2023, Part 1Published 21 November 2023.
- OHID: Child and maternal health profiles, March 2025Published 4 March 2025.
- OHID: May 2026 update and mental-health indicator limitationsPublished 6 May 2026.
- OHID Fingertips: England self-harm admission count and period
- UK Parliament: NHS mental-health spending forecast 2026/27Published 12 March 2026.
- DHSC: 8,500 extra mental-health workers announcedPublished 30 April 2026.
- NHS: Support while waiting for children’s mental-health services
- NHS: Discussing your needs and planned support
- NICE NG225: Self-harm assessment and care recommendations
- NHS: How to access mental-health services
- NHS: Where to get mental-health support for children and young peopleReferral routes, first conversations and contacting services.