
Carer Mental Health Statistics UK: 2026 Facts, Data & Key Insights
Carer mental health statistics UK
What the evidence says about unpaid carers’ wellbeing, the pressures they describe and the support they need.

Unpaid carers counted across the UK’s combined censuses.
2021 censuses & Scotland 2022Rounded count · not a new 2026 estimate
Rated their mental health bad or very bad.
June–August 2025 · self-selected surveyNot a diagnosis rate or population prevalence
Reported little social contact and feeling socially isolated.
Council-known adult carers of adults2025/26 survey · October–November 2025 fieldwork
Unpaid care is a role, not a single experience.
Unpaid carers support relatives, partners or friends with illness, disability or other care needs. They are not the same population as people employed to provide professional care.
Caring can involve a few hours of help each week or sustained support alongside paid work, parenting and the carer’s own health needs. Roles and circumstances change over time, so a single count cannot describe every caring experience.
Some people may not recognise the help they provide as “caring”. Survey wording, age coverage and whether respondents identify and report that role can affect the figures. Estimates from different sources should not be treated as interchangeable.
Carers UK’s combined census estimate is about 5.8 million unpaid carers across the UK, including about 1.7 million providing at least 50 hours of care a week. England and Wales accounted for about 5 million.
In England and Wales, 59% of unpaid carers were women in Census 2021. This is the female share of carers, not the percentage of all women providing care.
Census evidence
A census records people who report providing unpaid care under its question and age coverage. It is a snapshot of a caring role, not everyone who may become a carer.
Carer surveys
A survey can describe the pressures carers report. Its recruitment and eligibility determine whom the results represent; not every survey is a national prevalence estimate.
Mental health
Feeling stressed, anxious or depressed in a survey is different from a clinical assessment. Support should consider each person’s needs rather than infer a diagnosis from a percentage.
What the census totals can and cannot tell us
Carers UK’s census-based estimate combines the 2021 censuses in England, Wales and Northern Ireland with Scotland’s 2022 census. That makes the reference period visible: it is not a new count taken in 2026. National question wording and age coverage differ: England and Wales counted usual residents aged 5 and over, while Scotland reported ages 3 and over.
The census counts people reporting an unpaid caring role at that time. It does not count everyone who has ever provided care, and it can miss people who do not recognise or report the support they give as caring.
The number of hours is also a snapshot. Someone providing a few hours of help can face different demands from someone providing at least 50 hours a week, but hours alone do not describe the complexity of the role or a person’s mental health.
What carers say about their own wellbeing.
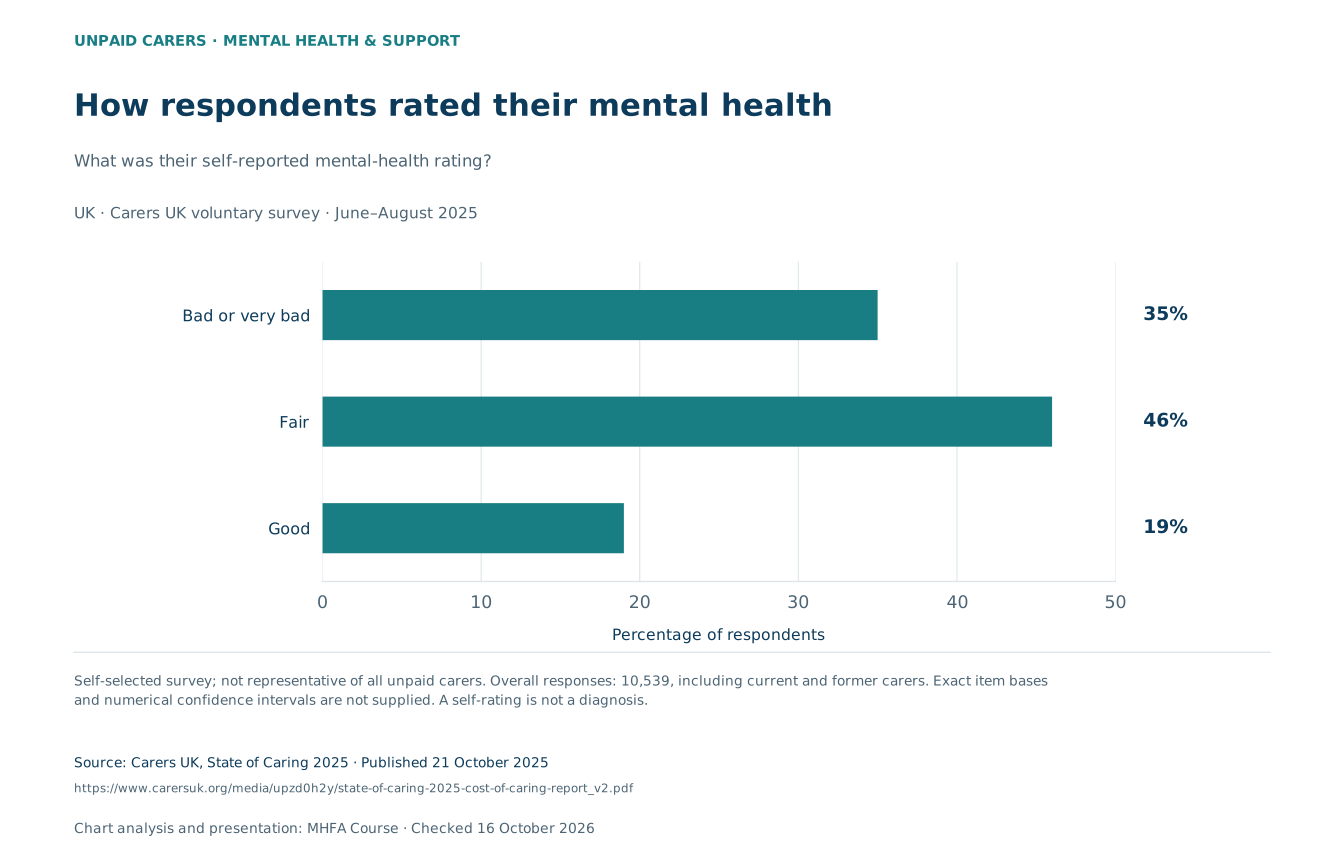
In Carers UK’s State of Caring 2025 survey, 35% of respondents rated their mental health as bad or very bad. A further 46% rated it fair and 19% good.
The online survey received 10,539 responses between June and August 2025. Participants chose to take part. Its findings give a detailed account of respondents’ experiences but cannot establish the prevalence of mental-health conditions among all UK unpaid carers.
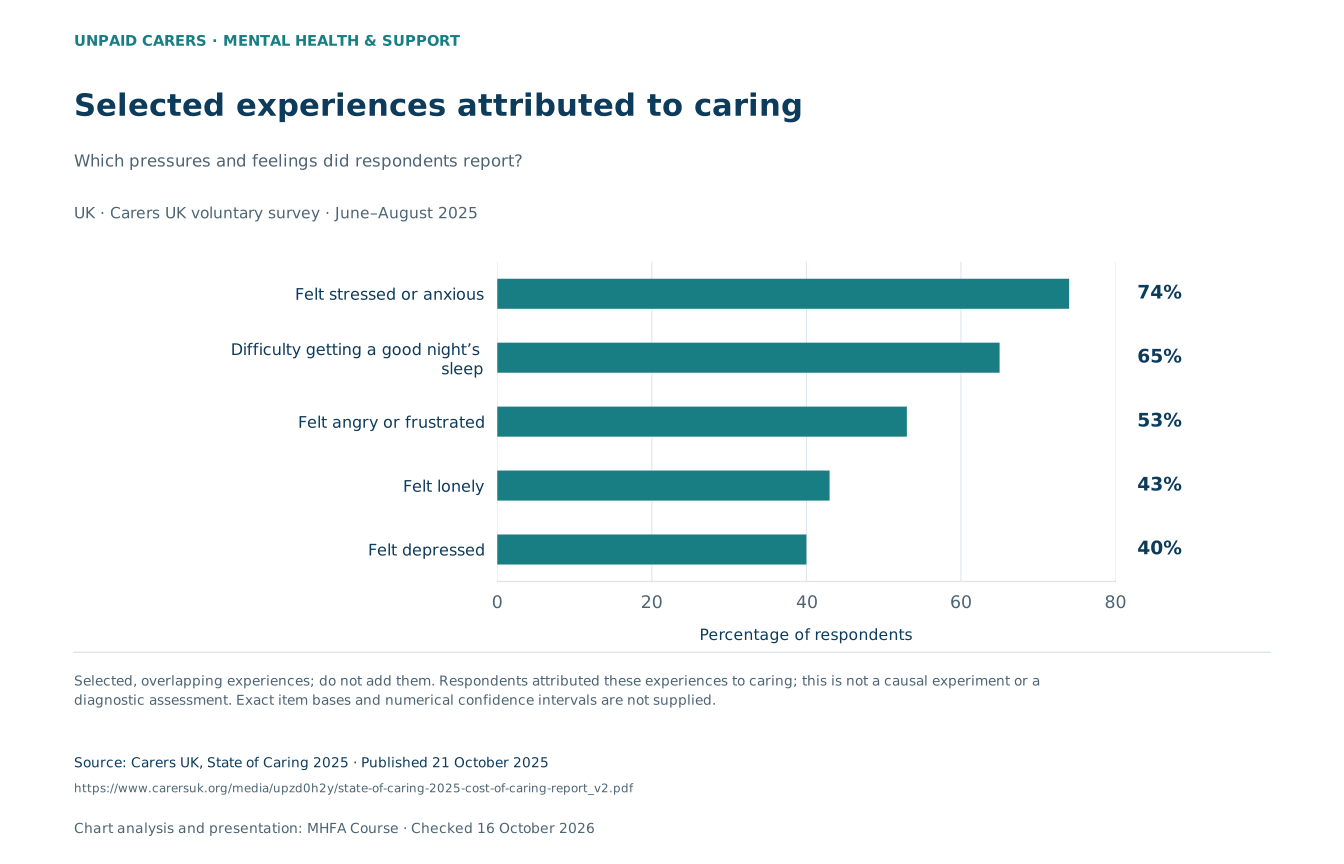
The first chart shows the rating categories. The second shows selected experiences participants said they had as a result of caring. Those experiences can overlap: the same respondent may report several.
How respondents rated their mental health
What was their self-reported mental-health rating?
| Group / measure | percent |
|---|---|
| Bad or very bad | 35% |
| Fair | 46% |
| Good | 19% |
Self-selected survey; not representative of all unpaid carers. Overall responses: 10,539, including current and former carers. Exact item bases and numerical confidence intervals are not supplied. A self-rating is not a diagnosis.
Selected experiences attributed to caring
Which pressures and feelings did respondents report?
| Group / measure | percent |
|---|---|
| Felt stressed or anxious | 74% |
| Difficulty getting a good night’s sleep | 65% |
| Felt angry or frustrated | 53% |
| Felt lonely | 43% |
| Felt depressed | 40% |
Selected, overlapping experiences; do not add them. Respondents attributed these experiences to caring; this is not a causal experiment or a diagnostic assessment. Exact item bases and numerical confidence intervals are not supplied.
Who took part in State of Caring?
Carers UK recruited the online survey through its members, website, social channels and supporting organisations. The organisation explicitly says it is not representative.
The whole survey included 93% current carers and 7% former carers. Among current carers, 61% reported providing at least 50 hours of care a week. This makes it especially important not to describe the results as population prevalence among every UK carer.
The 10,539 total responses are the overall survey size. Not everyone answered every question, and exact valid-answer bases and numerical confidence intervals are not published for these selected figures.
Reported experiences are not diagnoses
A response such as feeling stressed, anxious or depressed describes how someone answered a survey question. It does not establish a clinical anxiety or depressive disorder.
A person’s caring role may be important to understanding their wellbeing, but the same level of caring does not have the same effect on everyone. Survey associations do not identify the cause of each person’s symptoms.
Caring does not inevitably lead to mental illness. The person’s relationships, resources, health and the support available to them all need to be understood in context.
Relationships, time and opportunities to rest.
Caring may leave less time for rest, friendships and activities. In the 2025 Carers UK survey, 65% of respondents said they struggled to get a good night’s sleep because of caring and 43% said they felt lonely.
In the same survey, 59% said caring had led them to lose touch with family or friends. Losing contact and feeling lonely are separate questions, even though they can describe related pressures.
57% of the same survey’s respondents reported disagreements with a partner, family or friends because of caring. These are separate, overlapping reports, not categories that can be added.
A separate official measure of social contact
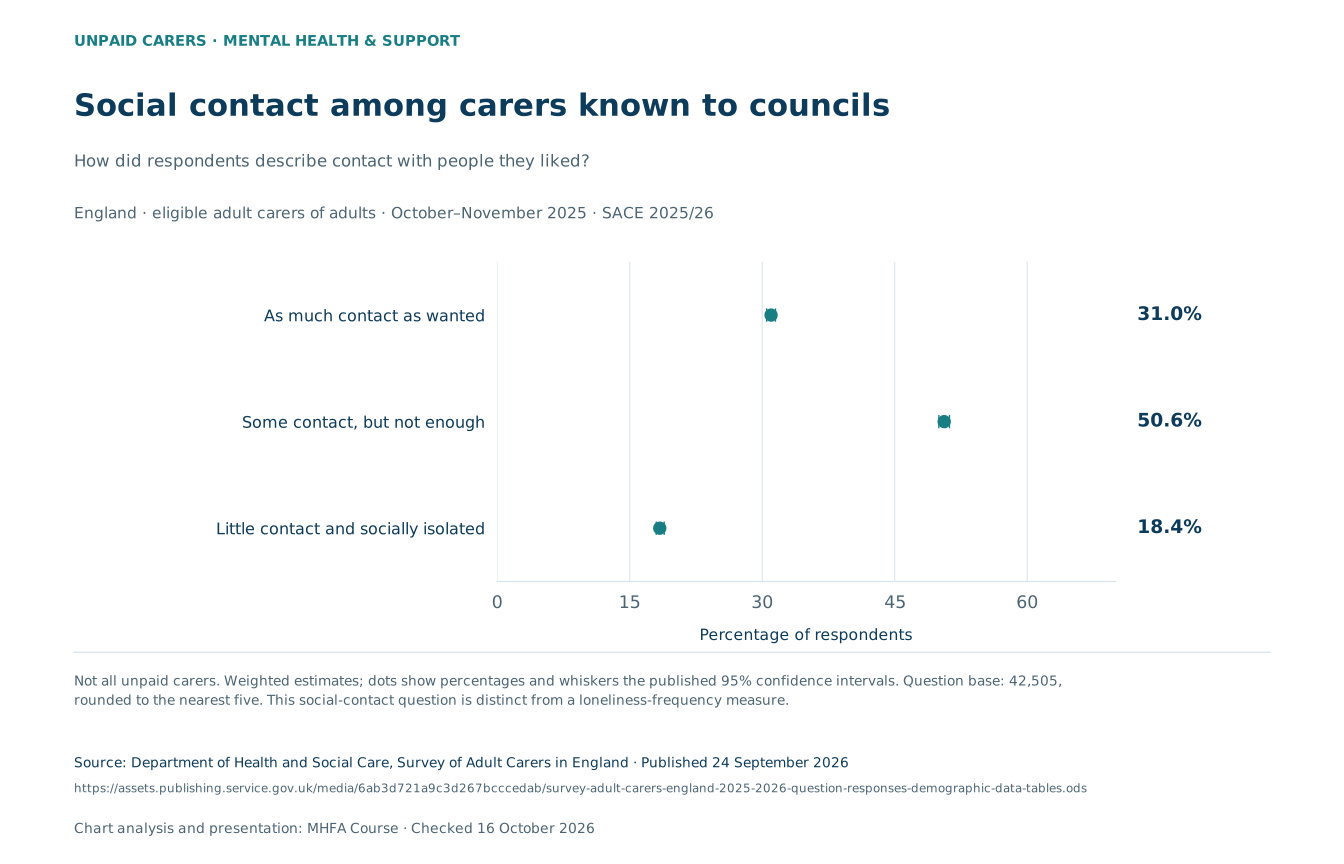
The 2025/26 Survey of Adult Carers in England asked carers known to councils about contact with people they liked. 31.0% reported as much contact as they wanted, 50.6% some contact but not enough, and 18.4% little contact and feeling socially isolated.
The middle response is specifically “some contact, but not enough”. It is not the total proportion of all respondents without enough contact. This question is also different from simply asking whether someone feels lonely.
Social contact among carers known to councils
How did respondents describe contact with people they liked?
| Group / measure | percent | 95% interval |
|---|---|---|
| As much contact as wanted | 31% | 30.5–31.5% |
| Some contact, but not enough | 50.6% | 50–51.2% |
| Little contact and socially isolated | 18.4% | 18–18.9% |
Not all unpaid carers. Weighted estimates; dots show percentages and whiskers the published 95% confidence intervals. Question base: 42,505, rounded to the nearest five. This social-contact question is distinct from a loneliness-frequency measure.
Who is included in the official England survey?
SACE covers unpaid carers aged 18 and over caring for another adult aged 18 and over, known to councils and meeting its support or assessment criteria. It is not a survey of every unpaid carer in England or across the UK.
Eligible carers had received carer support in the previous twelve months, or had been assessed in that period but received no direct support, at each council’s selected population-extraction date. Responses are weighted to that eligible population.
The survey is mainly postal. Non-response and exclusions from the sampling frame may affect the results. The published question base for social contact is 42,505 respondents, rounded to the nearest five; this is not the number selecting any one response.
The dots show estimates and the whiskers show the publisher’s 95% confidence intervals. Those intervals describe sampling uncertainty, not every possible source of bias.
Loneliness and poor mental health can occur together. A survey finding about losing touch with friends or feeling lonely does not show that isolation alone causes depression, or quantify an individual carer’s risk of suicide.
Practical support, opportunities for breaks and help maintaining valued relationships can matter alongside support for the person receiving care. What is helpful should be discussed with the carer rather than assumed from a group average.
Caring can overlap with paid work and other responsibilities.
A caring role can overlap with employment, parenting and the carer’s own health needs. The groups below help describe some of those circumstances without assuming that every carer has the same experience.
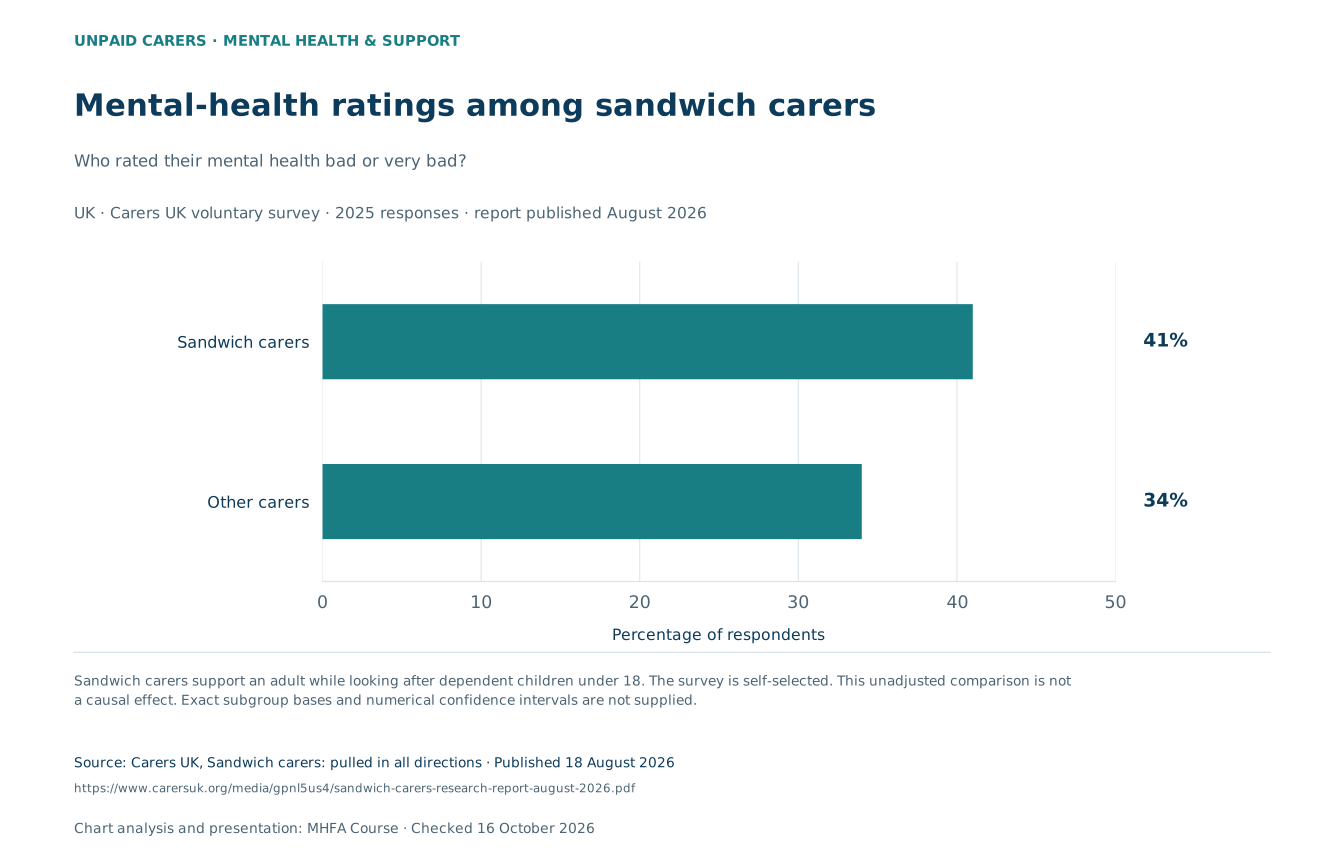
A Carers UK report published on 18 August 2026 analysed 2025 survey responses from people supporting an adult relative, partner or friend while also looking after dependent children aged under 18. 41% of these “sandwich carers” rated their mental health bad or very bad, compared with 34% of other carers in the survey.
These are two groups within the self-selected survey. They are not rates of diagnosed illness or proof that combining roles caused the difference. The report does not supply exact valid-answer subgroup bases or numerical confidence intervals for this comparison.
Mental-health ratings among sandwich carers
Who rated their mental health bad or very bad?
| Group / measure | percent |
|---|---|
| Sandwich carers | 41% |
| Other carers | 34% |
Sandwich carers support an adult while looking after dependent children under 18. The survey is self-selected. This unadjusted comparison is not a causal effect. Exact subgroup bases and numerical confidence intervals are not supplied.
Control over daily life is another dimension of support.
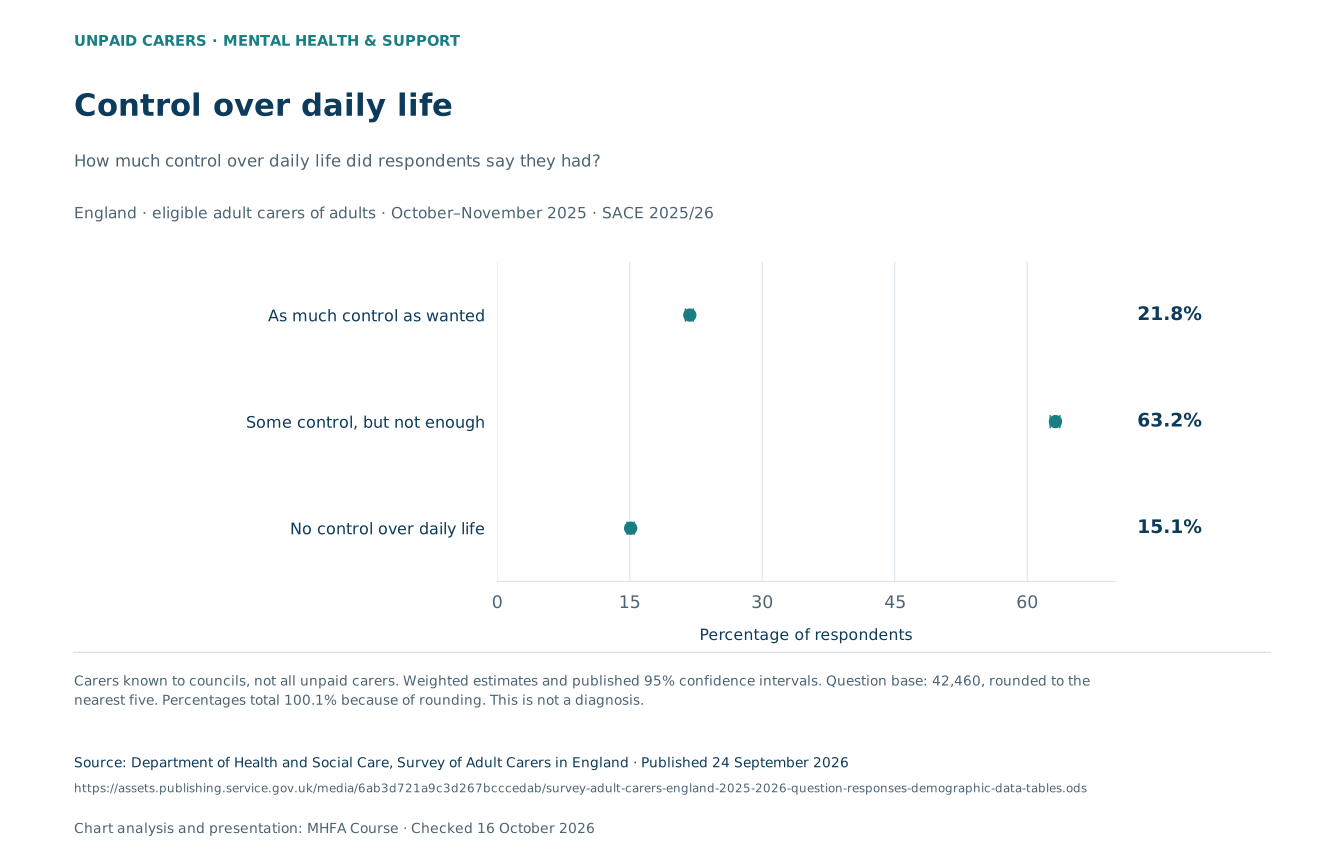
The official England survey separately asked about control over daily life. 21.8% reported as much control as they wanted; 63.2% some control but not enough; and 15.1% no control.
These are respondents’ perceptions, not measures of diagnosis, service eligibility or the quality of a particular care arrangement. The question used 42,460 valid responses, rounded to the nearest five. The percentages total 100.1% because of rounding.
Control over daily life
How much control over daily life did respondents say they had?
| Group / measure | percent | 95% interval |
|---|---|---|
| As much control as wanted | 21.8% | 21.3–22.2% |
| Some control, but not enough | 63.2% | 62.6–63.7% |
| No control over daily life | 15.1% | 14.7–15.5% |
Carers known to councils, not all unpaid carers. Weighted estimates and published 95% confidence intervals. Question base: 42,460, rounded to the nearest five. Percentages total 100.1% because of rounding. This is not a diagnosis.
Among employee respondents to State of Caring 2025, 35% said they had reduced their working hours. That denominator is employee respondents, not every survey participant or every UK carer.
Across the survey, 68% wanted more support to look after their own health and wellbeing. This describes respondents’ stated needs; it is not an estimate of eligibility for a particular service.
Young carers need space for their own lives.
Young carers are children and young people who help care for someone with illness, disability or other support needs. Their role should be understood alongside their own education, relationships, health and development.
Estimates depend on the age range and how caring is measured. A school survey should not be presented as a count of all young carers across the UK, and an adult-carer survey does not describe children’s experiences.
Caring can affect time for school, friendships and rest. NHS guidance says young carers should not take on tasks that are inappropriate for their age or put their health or education at risk.
In England, a young carer or their parent can ask the local council for a young carer’s assessment. It considers how caring affects the young person, whether they want to continue and what support the family needs. A school’s pastoral or safeguarding team can also help them find support.
An assessment starts with the carer’s needs.
In England, a council must assess an adult caring for another adult where it appears that the carer may need support now or in the future. This duty is set out in section 10 of the Care Act 2014.
The assessment considers wellbeing, the person’s ability and willingness to care, and the outcomes they want to achieve. It is an opportunity to discuss the effects of caring on their own life, including work, relationships, health and time for other activities.
Request an assessment.
A carer can contact their local council to ask for an assessment. NHS guidance explains that the assessment is free.
Separate assessment from entitlement.
An assessment does not automatically guarantee a particular service or payment. Eligibility and any financial assessment are separate questions.
The other UK nations have their own legal frameworks. The English Care Act duty should not be described as a single UK-wide rule.
Carers can also speak to their GP about their own health. Help for the person receiving care should not replace attention to the carer’s needs.
Our Mental Health First Aid courses help those working with carers — in health, social care, and community settings — to identify and respond to carer mental health needs.
Reading carer statistics in context.
Do these statistics include paid care workers?
The guide focuses on unpaid carers supporting relatives, partners or friends. Professional care workers are a different population. A person may have both roles, but a survey of one group should not be relabelled as evidence about the other.
Does a bad mental-health rating mean a diagnosed condition?
No. A self-rated mental-health question is not a clinical assessment. Likewise, reporting stress, anxiety or feeling depressed does not establish the prevalence of diagnosed disorders.
Can different carer surveys be compared directly?
Only with care. Geography, age coverage, eligibility, recruitment and questions can differ. Results from a self-selected UK survey and an England survey of carers known to councils should not be combined or presented as an annual change.
Can someone ask for support before caring reaches a crisis?
In England, the assessment duty applies where it appears an adult caring for another adult may need support now or in the future. An assessment considers the person’s own wellbeing and circumstances; it does not automatically guarantee a particular service or payment.
Is a carer’s assessment free?
NHS guidance says the assessment is free. Whether someone is eligible for a particular type of support, and any relevant financial assessment, are separate matters.
What about young carers?
Young carers’ needs differ from adult carers’ needs. In England, a young carer or their parent can ask the council for an assessment of the impact of caring on wellbeing, education and family life.
Methods, uncertainty and reuse
This guide presents published evidence visually; it is not a new survey. Population counts, respondents’ experiences and clinically assessed conditions are different measures.
Check the geography, dates, age coverage and recruitment method before comparing percentages. A self-selected survey can provide valuable accounts of caring without establishing prevalence among every unpaid carer.
Where exact item bases and confidence intervals are supplied, they travel with the data. Missing intervals or subgroup bases are not invented. A whole-survey response count is not automatically the valid-answer base for each question.
The charts start at zero. Keep their scope and notes when reusing them; do not add overlapping responses or interpret observed differences as causal effects.
Carer wellbeing charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the population, survey question, period and limitations with every figure.
Mental Health First Aid Course (2026). Carer Mental Health Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/carer-mental-health-statistics-uk
Sources
Primary evidence and methodology. Checked 16 October 2026.
- Carers UK: State of Caring 2025 full report
- Carers UK: State of Caring 2025 publication
- Carers UK: current State of Caring collection
- Carers UK: Sandwich carers report, August 2026
- Carers UK: Sandwich carers publication
- Carers UK: census-based key facts and figures
- ONS: Unpaid care by age, sex and deprivation, Census 2021
- National Records of Scotland: Census 2022 unpaid care
- NISRA: Census 2021 health and unpaid-care tables
- Care Act 2014: section 10
- DHSC: Care and support statutory guidance
- NHS: Carer’s assessments
- NHS: Being a young carer — your rights
- DHSC SACE 2025/26 release
- Question responses and demographic data tables
- Time series data including 95% confidence intervals
- SACE methodology
- SACE data quality report