
Burnout Statistics UK: 2026 Facts, Data & Key Insights
Burnout statistics UK
What the latest research tells us about sustained pressure, time away from work and the support people receive.

Experienced high or extreme pressure or stress often or always in the previous year.
UK adults aged 18+ · November 2025 surveyReported needing time off due to poor mental health caused by pressure or stress in the previous year.
UK workers aged 18+ · November 2025 surveySaid mental health was prioritised through visible actions and resources.
UK workers aged 18+ · November 2025 surveyStress frequency covers all adults. Questions about work cover employed respondents. Return-to-work support concerns a smaller group who had taken time off and returned. None of these percentages is a national clinical diagnosis rate for burnout.
Burnout has a specific work-related meaning.
The World Health Organization describes burnout as an occupational phenomenon arising from chronic workplace stress that has not been successfully managed. It is included in ICD-11, but is not classified there as a medical condition. Its definition specifically concerns work.
Energy depletion
Feeling exhausted or depleted is one dimension of burnout. A difficult day or tiredness alone does not establish all the dimensions of the phenomenon.
Negativism or cynicism
WHO includes increased mental distance from a person’s job, or feelings of negativism or cynicism about it. The work context is part of the definition.
A reduced sense of effectiveness
The third dimension is reduced professional efficacy. Burnout is broader than a single question about feeling stressed or needing time off.
People use “burnout” in everyday conversation in several ways. In research, the wording of the question determines what a percentage means. A survey asking about stress during the previous year is measuring reported stress; a questionnaire about burnout characteristics measures those characteristics. Neither automatically counts medically diagnosed cases.
This guide therefore keeps the report’s measures separate. Its title describes the topic, while each chart names the outcome actually measured. That distinction also explains why figures from different reports can look very different without one necessarily contradicting another.
Why does Deloitte report a different burnout figure?
Deloitte’s research published in May 2024 found that 63% of respondents reported at least one burnout characteristic, compared with 51% in its 2021 research. The later result came from an October 2023 survey of 3,156 UK working adults. That is a difference of 12 percentage points in its own measure. Reporting one characteristic is not the same as meeting every part of WHO’s description, and the question is different from Mental Health UK’s stress-frequency question.
What is behind the 91% headline?
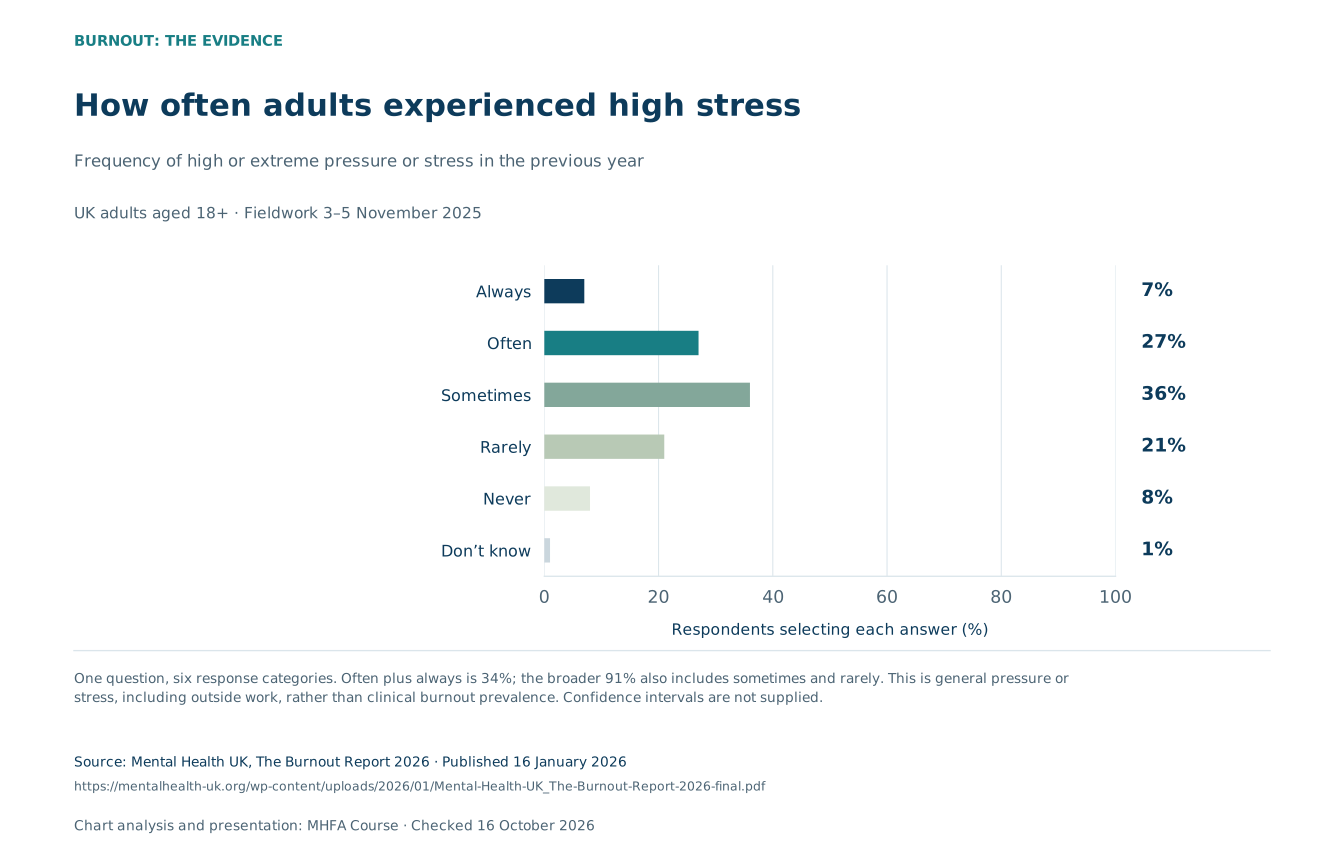
The widely quoted 91% figure includes UK adults who experienced high or extreme pressure or stress rarely, as well as sometimes, often or always. It describes a broad experience over the previous year.
A more specific reading is that 34% answered often or always. The full distribution below shows why those two summaries should not be treated as the same headline. They are nested groups drawn from one question, so they cannot be added together.
Reported high or extreme pressure or stress often or always.
All UK adults aged 18+, rather than workers alone.
How often adults experienced high stress
Frequency of high or extreme pressure or stress in the previous year
| Response / group | Percentage |
|---|---|
| Always | 7% |
| Often | 27% |
| Sometimes | 36% |
| Rarely | 21% |
| Never | 8% |
| Don’t know | 1% |
One question, six response categories. Often plus always is 34%; the broader 91% also includes sometimes and rarely. This is general pressure or stress, including outside work, rather than clinical burnout prevalence. Confidence intervals are not supplied.
Frequency still does not tell us everything about the experience. The question does not establish how long an episode lasted, whether work was the main cause, or whether the respondent met a clinical definition of another mental health condition. It is useful evidence of perceived pressure, with those limits kept in view.
The report separately found that 59% of adults said poor sleep had contributed to stress in the previous year. This records respondents’ perceptions. It does not prove that stress caused a particular physical illness or that improving one factor alone would prevent burnout.
Stress-related absence across age groups.
One in five workers surveyed said they had needed to take time off in the previous year because of poor mental health caused by pressure or stress. This is a self-reported need for absence. It does not tell us how many days each person took, or how many absences were recorded as burnout.
Stress-related time off by age
Reported needing time off in the previous year because of poor mental health caused by pressure or stress
| Response / group | Percentage |
|---|---|
| Aged 18–24 | 39% |
| Aged 55+ | 11% |
| All workers (reference) | 20% |
Two selected age groups. The all-worker 20% reference includes these groups; the three middle age groups do not have exact published values. Subgroup sample sizes and confidence intervals are not supplied. This measures reported need for time off, rather than days lost.
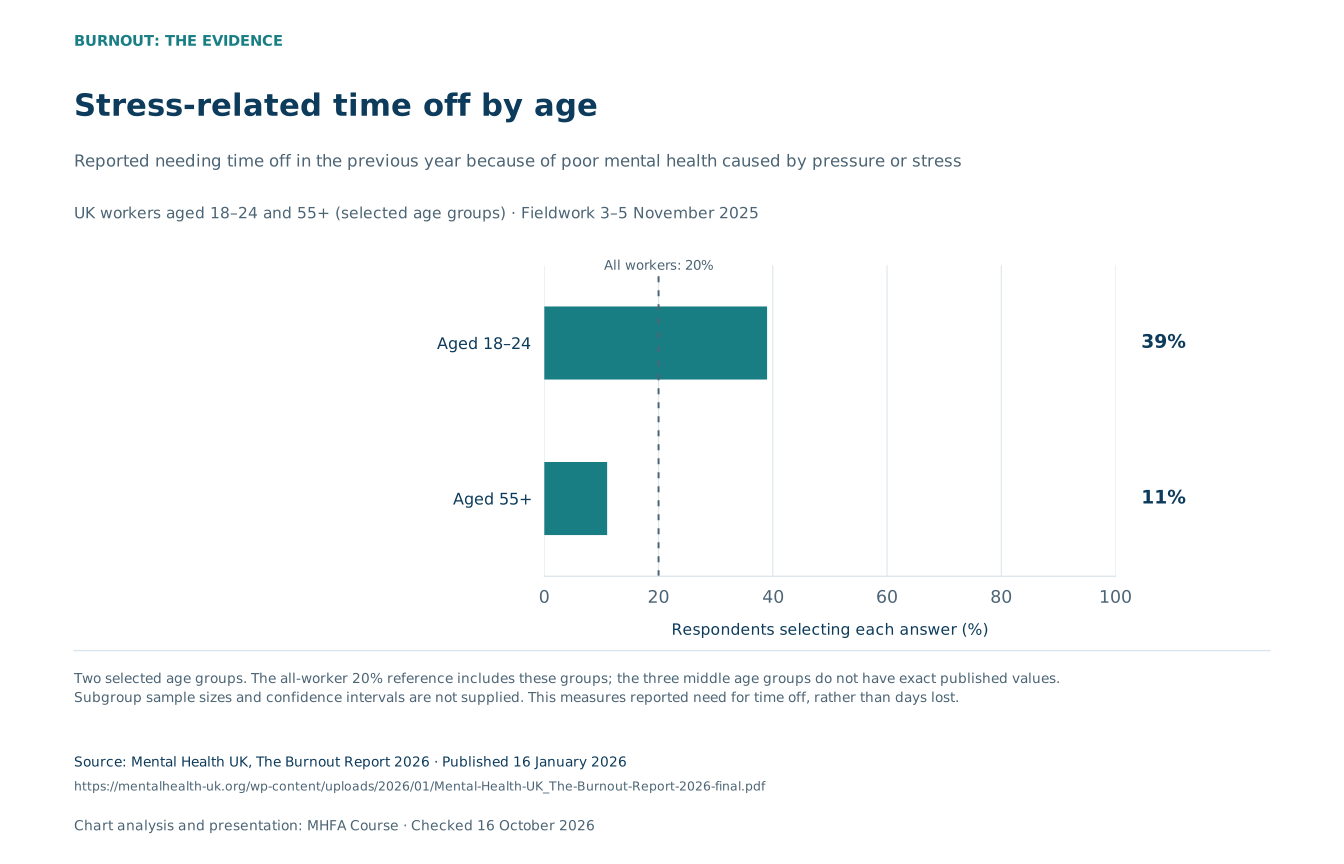
The age breakdown shows different reported experiences, rather than a diagnosis-based ranking of who is most vulnerable. The 39% result for workers aged 18–24 is a subgroup estimate; the 20% all-worker figure includes those younger respondents. They are not two independent groups.
Differences in jobs, hours, circumstances and reporting may matter, but this survey cannot establish which factors caused an age difference. The published chart does not provide confidence intervals or age-group sample sizes, so precise claims about statistical significance would go beyond the evidence.
What workers say has contributed.
Workers were asked about factors they felt had caused stress in the past year and might have contributed to burnout. A high or increased workload was reported by 42%, regular unpaid overtime by 33%, and fear of redundancy or job security by 32%.
The chart below focuses specifically on workers aged 18–24, for whom the report publishes six exact results. Its percentages use that younger age group, rather than all workers. They provide a closer view of what younger respondents reported, without treating their experiences as representative of the whole workforce.
Pressures reported by workers aged 18–24
Agreement that each work factor caused stress in the past year and may have contributed to burnout
| Response / group | Percentage |
|---|---|
| High or increased workload | 57% |
| Extra paid hours or another job because of living costs | 51% |
| Unpaid overtime beyond contracted hours | 47% |
| Feeling isolated at work | 45% |
| Fear of redundancy or job insecurity | 43% |
| Bullying or intimidation by colleagues | 35% |
These six published factors can overlap. Workers attributed stress to them; the survey does not establish causality or a clinical diagnosis. This chart covers workers aged 18–24, not all workers. Subgroup sample size and confidence intervals are not supplied.
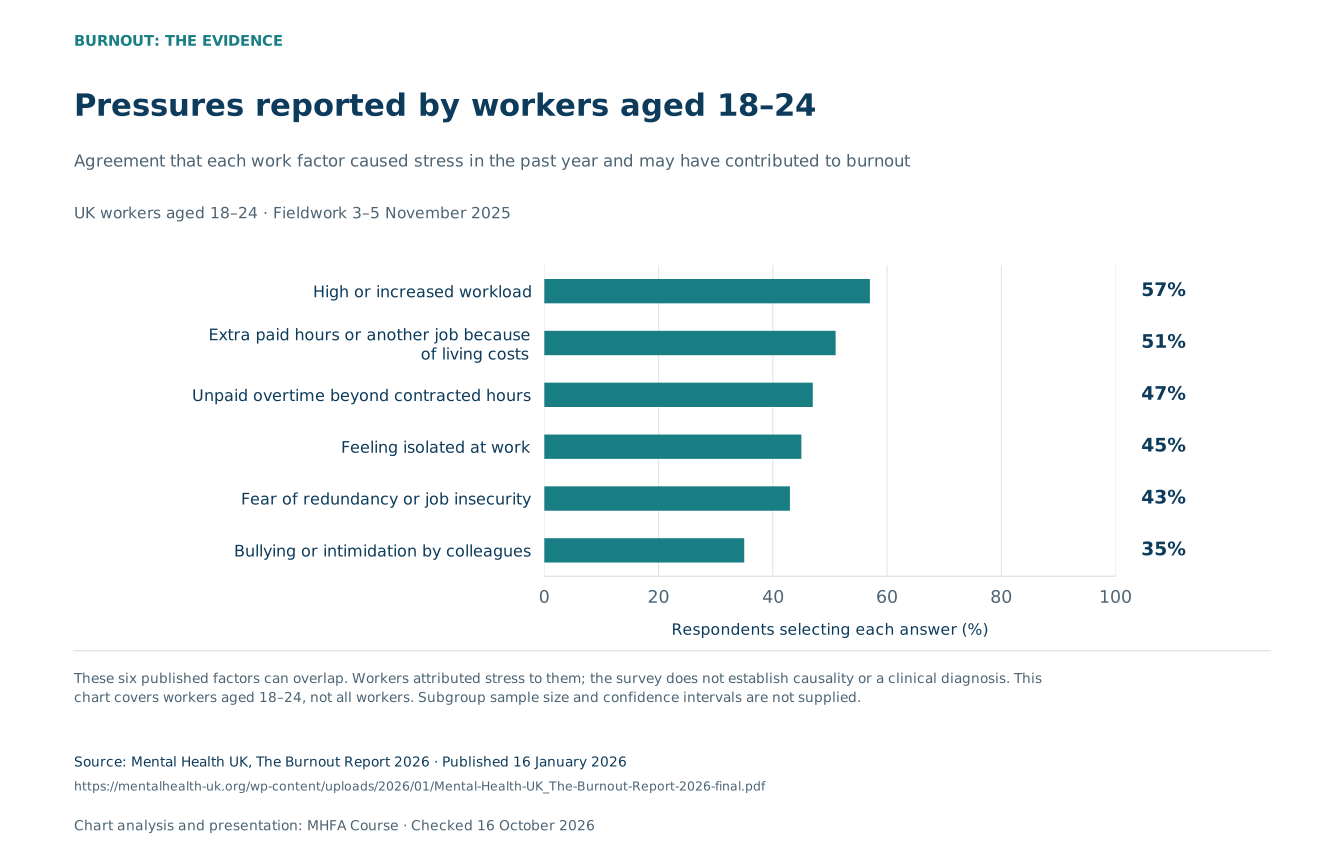
Several pressures can apply to the same person. These percentages therefore overlap and should not be summed into a total. The wording also matters: respondents linked an experience to their own stress. That is useful information about perceived pressures, rather than proof that a particular factor caused a diagnosed condition.
For a workplace discussion, the questions are more informative than a single national number. They invite attention to how work is organised, which demands feel manageable and whether people can raise concerns. They do not identify the cause of an individual’s difficulties or establish the right response without talking to that person.
How comfortable do workers feel?
A question about feeling comfortable talking to a manager is different from a question about whether support is available. The report examines both. In the 2026 edition, 35% of workers said they would not feel comfortable telling a line manager or senior leader about high or extreme pressure or stress at work.
The published comparison reports 38% for women and 32% for men. The all-worker 35% figure is included as a reference, rather than as a third independent group. No complete comfort-versus-discomfort distribution is inferred from these selected results.
Discomfort discussing stress with a manager
Would not feel comfortable telling a line manager or senior leader about experiencing high or extreme pressure or stress at work
| Response / group | Percentage |
|---|---|
| Women | 38% |
| Men | 32% |
| All workers (reference) | 35% |
This is anticipated comfort, rather than actual disclosure, absence or working while ill. The all-worker 35% reference includes these groups. Subgroup sample sizes and confidence intervals are not supplied.
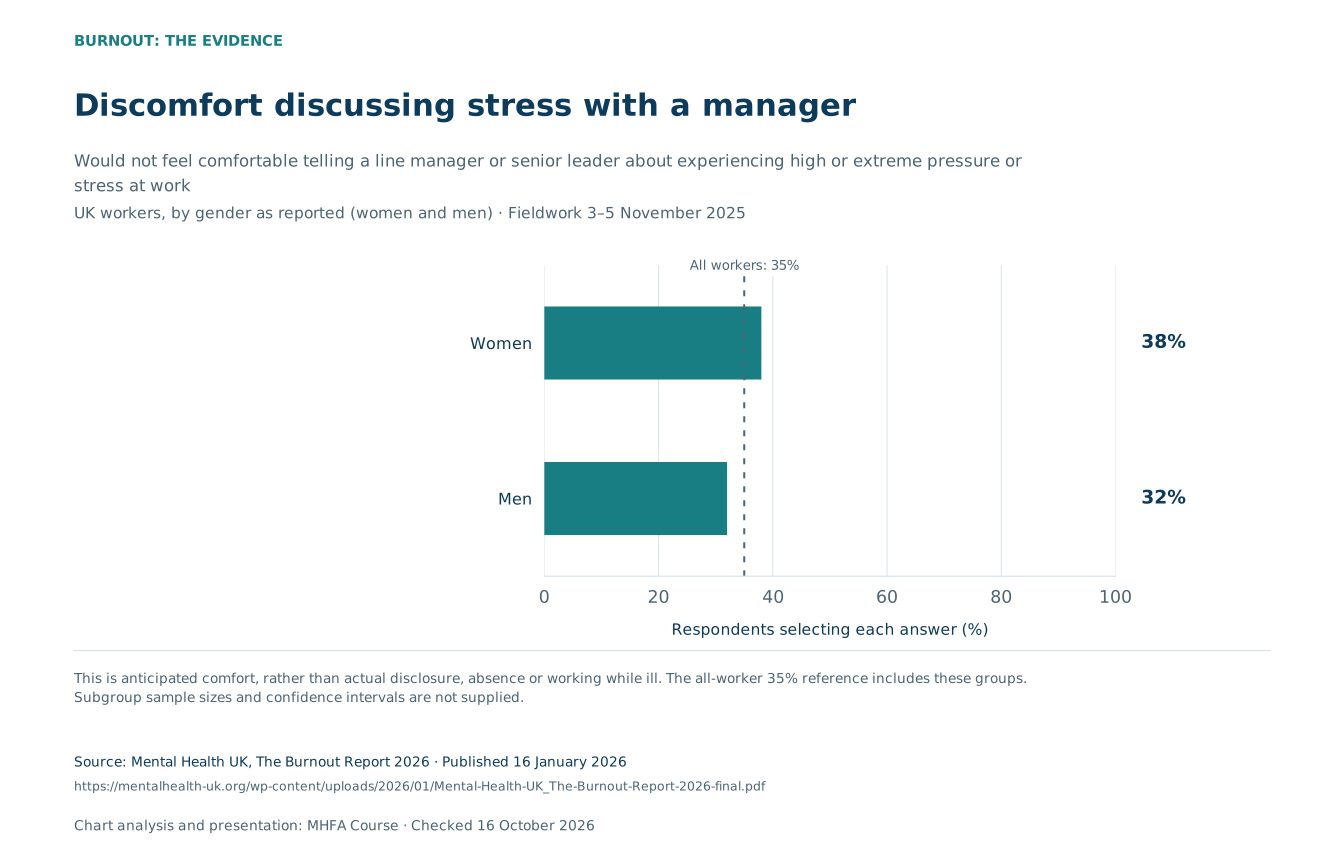
This describes how people thought they would feel in that situation. It does not show that every uncomfortable respondent actually withheld a diagnosis, needed sickness absence or was working while ill. The all-adult 91% stress headline has a different denominator and cannot be combined with this question to calculate a “silent burnout” total.
Employees’ perceptions of their employer’s approach add another dimension. Just over a quarter, 27%, described mental health as a priority backed by visible actions and resources. Another 29% described awareness being raised while managers lacked time, training or resources to provide meaningful support.
How workers describe employer support
Description of the employer’s approach to mental health in the workplace
| Response / group | Percentage |
|---|---|
| Awareness, but managers lack time, training or resources | 29% |
| Prioritised through visible action and resources | 27% |
| Treated as a tick-box exercise | 18% |
| Not prioritised at all | 10% |
Selected responses with exact published values; the unlabelled don’t-know category is not included. These are workers’ perceptions, not an audit of employers or their policies. Confidence intervals are not supplied.
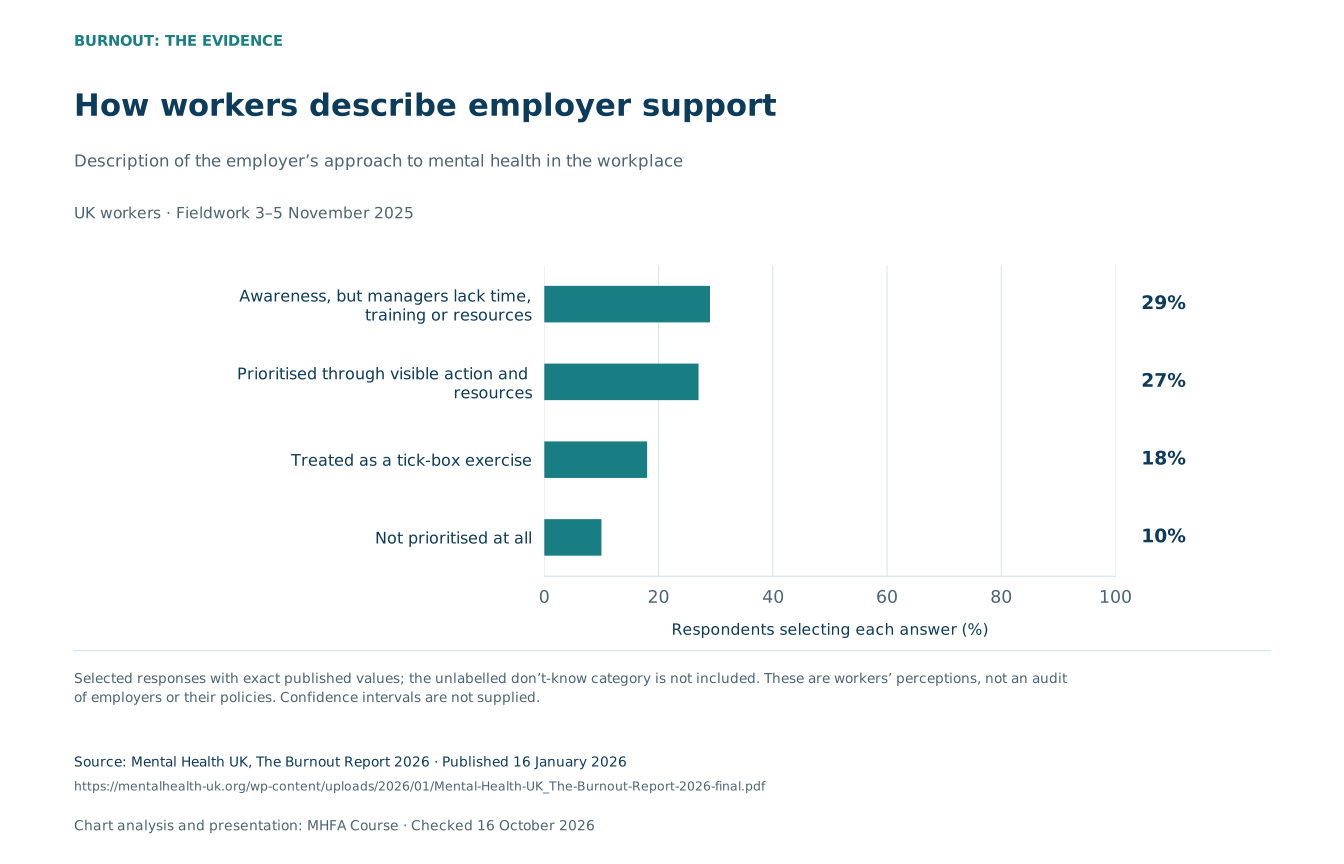
The latter is one bundled response. It should not be shortened to a claim that 29% of managers lacked training alone. These are workers’ views of their workplace, rather than an independent audit of employer policies. Formal provision and an employee’s experience of using it are related but distinct.
Support on returning to work.
The return-to-work findings concern workers who had taken time off because of high or extreme pressure or stress and then returned. This smaller, conditional group is the denominator for every percentage below.
Support reported after returning to work
Support received after returning from time off due to high or extreme pressure or stress
| Response / group | Percentage |
|---|---|
| No support received | 27% |
| Flexible or reduced hours | 27% |
| Formal return or recovery plan | 17% |
| Phased or gradual return | 17% |
| Remote work or a different physical environment | 16% |
| Additional support: EAP, training, coaching or peers | 15% |
| Regular manager wellbeing check-ins | 11% |
Only workers who took relevant time off and returned; this subgroup’s sample size is not supplied. Support options can overlap, with no support a distinct response. These findings do not establish diagnosed burnout or the effectiveness of support. Confidence intervals are not supplied.
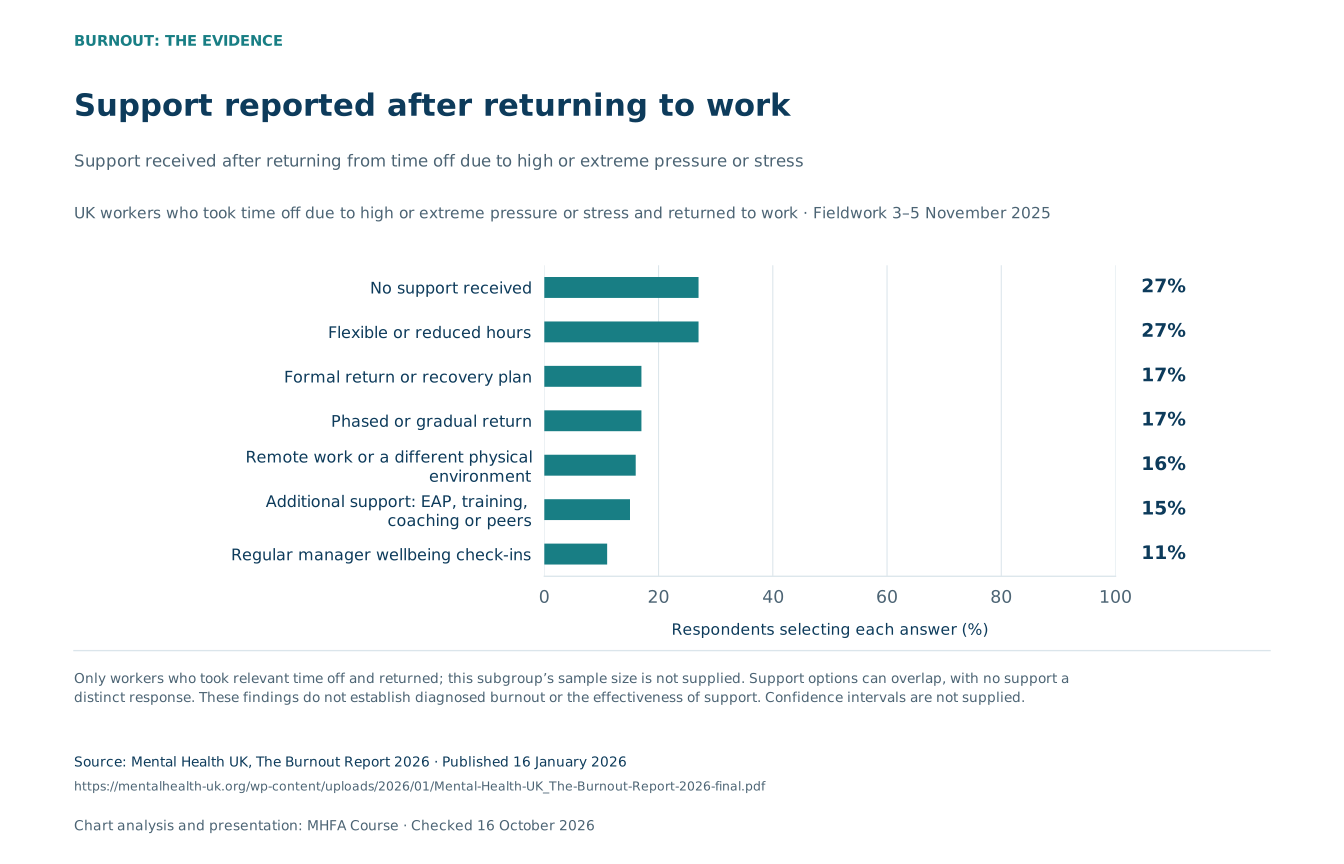
More than one form of support could be reported. Flexible hours, a phased return and a recovery plan can therefore overlap; the categories are not pieces of one complete pie. The 27% reporting no help or support is not 27% of all UK workers or all employers.
The results describe what respondents said they were offered. They do not establish which intervention works best, the quality of the support, whether it met each person’s needs, or how long recovery took. A lower figure for one option is not automatically evidence that every employer should use that option for everyone.
Make room for a specific conversation
Acas recommends talking with an employee about work-related stress and what support could help. A useful conversation can focus on demands, changes that may be practical and how progress will be reviewed. It should allow the person to explain their experience, rather than assume their needs from a survey average.
Keep health needs in view
NHS guidance advises seeking help if stress is affecting daily life or self-help is not helping. A GP can assess symptoms and discuss support. Describing an experience as burnout should not prevent someone from seeking an assessment for persistent or concerning symptoms.
Related measures need their own context.
A separate picture from NHS trust staff
The 2025 NHS Staff Survey asks directly how often staff feel burnt out because of their work. In its national results, 31.5% of NHS trust staff in England answered often or always. Fieldwork took place in September–November 2025, and the results were published on 12 March 2026.
This is a workforce-specific report of frequency, not a clinical diagnosis. Its population and question differ from Mental Health UK’s general stress question, so the two percentages should not be compared as equivalent measures.
Often or always felt burnt out because of their work.
National results cover 206 NHS trusts. The survey received 751,088 staff responses across those trusts; that is not the denominator for this individual question.
Official and employer studies help describe the wider workplace mental health picture, but they answer different questions. HSE estimated 964,000 workers with work-related stress, depression or anxiety in Great Britain in 2024/25, alongside 22.1 million working days lost. Burnout is not measured separately within those totals.
CIPD’s 2025 survey of responding organisations reported average annual sickness absence of 9.4 days per employee, covering all causes. Its separate 41% figure concerns employers naming mental ill health among their top three causes of long-term absence. Neither is a rate of burnout among individual workers.
How should the wider cost estimates be read?
Deloitte’s 2024 analysis estimated £51 billion in annual costs to UK employers from poor mental health and an average £4.70 return per £1 invested across the interventions it studied. This does not guarantee savings from a particular programme. AXA’s separate £57.4 billion figure is the reduced-productivity component of its wider £102 billion model for 2023, not the total cost of burnout.
These are wider poor-mental-health models, not a measured cost of burnout. The employer-cost analysis was published in 2024 and the AXA model concerns 2023; neither should be labelled as a new 2026 estimate. Their scopes differ, and the intervention average does not predict the result of a particular course or employer programme.
The strongest use of these sources is to retain their original definitions. National survey responses, employer reports, modelled costs and formal health definitions can inform the same discussion without becoming one interchangeable dataset.
Reading burnout statistics with care.
What percentage of people in the UK have burnout?
The reviewed sources do not establish one national clinical prevalence rate. The Burnout Report’s 91% measures adults experiencing high or extreme stress at least rarely; 34% experienced it often or always. Deloitte’s burnout-characteristic question measures something different. Each should keep its own label.
Is burnout a medical condition?
WHO includes burnout in ICD-11 as an occupational phenomenon, not a medical condition. Its definition concerns chronic workplace stress and three dimensions: exhaustion, distance or cynicism about the job, and reduced professional efficacy. People experiencing difficulties can still need health assessment and support.
Does the 2026 report describe 2026 experiences?
Its fieldwork took place on 3–5 November 2025, before publication in January 2026. Questions about the previous year refer to the period before those interviews. The report title and the date the data were collected should both remain visible.
Can these figures predict my recovery time?
No. These survey questions describe reported stress, time off and support. They do not follow an individual recovery pathway or provide a standard time to recover. A person’s circumstances and needs should be considered individually.
How the evidence was selected and presented
The core charts use Mental Health UK’s 2026 report, based on an online YouGov survey weighted to represent UK adults aged 18 and over. The total sample was 4,502, including 2,591 employed respondents. That total is not the sample size for every conditional question or age group.
The published results used here are rounded whole percentages. Confidence intervals and relevant subgroup bases were not supplied alongside these charts, so none have been estimated or invented. Rounded responses need not produce exact totals, and overlapping answers should not be added. The employer-support chart shows only categories with published numerical labels.
Self-report captures what respondents remember and perceive. Cross-sectional findings can describe patterns but cannot establish causes, diagnose individuals or demonstrate that a workplace intervention produced a particular outcome. The charts retain the question, population, fieldwork dates and original source so those limits remain visible when downloaded.
Share the findings.
Keep the context.
Six chart sets include SVG and PNG images, the underlying CSV data, source details and notes on each denominator. Retain the survey date and the question being measured when reusing a figure.
Mental Health First Aid Course (2026). Burnout Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/burnout-statistics
Sources
Original evidence and methodology. Checked 16 October 2026.
- Mental Health UK: The Burnout Report 2026Published 16 January 2026; November 2025 fieldwork. Printed pages 12–21 supply methods and chart values.
- Mental Health UK: 2026 report launch16 January 2026; findings and survey method.
- Mental Health UK: burnout reportsLatest edition checked 16 October 2026.
- World Health Organization: burnout in ICD-11Occupational phenomenon, its three dimensions and work-specific definition.
- NHS Staff Survey 2025: National Results BriefingPage 30, question 12 b; England NHS trust staff. Fieldwork September–November 2025; published 12 March 2026.
- NHS England: Staff Survey publicationConfirms the 12 March 2026 release date for the 2025 national results.
- Deloitte: 2024 mental health researchPublished 17 May 2024; burnout characteristics and broader employer-cost analysis.
- HSE: work-related stress, depression or anxietyGreat Britain, 2024/25; published 20 November 2025. Combined category, not burnout alone.
- CIPD: Health and wellbeing at work 20252025 employer survey; all-cause absence and long-term mental ill-health absence.
- AXA: 2023 economic cost modelPublished 2024; wider poor mind-health model, not a cost of burnout.
- Acas: supporting employees with work-related stressGreat Britain guidance, updated 16 January 2025.
- Acas: time off with stressContact during absence and planning a supported return; updated 16 January 2025.
- NHS: stressRecognising stress and seeking support; updated 6 March 2026.