
Anxiety Statistics UK: 2026 Facts, Data & Key Insights
Anxiety statistics UK
Clear evidence on anxiety disorders, everyday anxiety and access to treatment — with the people, periods and measures behind the numbers.

Met survey criteria for past-week GAD.
England · adults aged 16+ · APMS 2023/24Of adults identified with GAD reported medication or psychological therapy for a mental or emotional problem.
England · adults aged 16+ with GAD · APMS 2023/24Rated yesterday’s anxiety in the high band, 6–10 out of 10.
UK · adults aged 16+ · ONS, January–March 2026These headline figures have different denominators. GAD prevalence describes a survey-assessed condition; treatment is measured among people identified with GAD; the ONS rating describes how people felt on one day.
Three measures. Different questions.
Anxiety is an experience as well as part of several mental health conditions. A period of worry is not automatically a disorder. The distinction matters when reading a headline: an estimate of GAD, a measure of broader mental ill health and a rating of yesterday’s feelings each answers a different question.
The Adult Psychiatric Morbidity Survey (APMS) uses the Clinical Interview Schedule–Revised, or CIS-R. A structured interview and scoring rules identify conditions in a household sample. The resulting estimates include people who may never have received a clinical diagnosis, as well as those already receiving care.
Generalised anxiety disorder
GAD involves persistent, difficult-to-control worry across different situations. APMS assesses whether its criteria were met in the week before interview; its algorithm also includes a symptom-duration requirement of at least six months.
Common mental health conditions
The 20.2% APMS estimate for adults aged 16+ includes depression and several anxiety-related conditions. It is not an estimate of anxiety alone. Individual conditions can overlap, so their percentages cannot simply be added.
Anxiety yesterday
ONS asks people to rate how anxious they felt yesterday from 0 to 10. This captures a day’s wellbeing. A high response is not equivalent to meeting the criteria for an anxiety disorder.
The all-adult GAD estimate is 7.5%, with a 95% confidence interval of 6.7%–8.4%. It describes existing past-week prevalence among adults in England’s private households. It is not the percentage newly diagnosed each week, and it is not a UK-wide count.
GAD has become more common.
The comparable APMS series shows GAD prevalence among adults aged 16–64 increasing from 4.4% in 1993 to 8.5% in 2023/24. Estimates were broadly stable through 2007 before rising in the later surveys.
The same age range and England coverage are used in every wave. This matters because the earliest survey did not include people aged 65 and over. The current 8.5% trend endpoint therefore differs from the 7.5% estimate for all adults aged 16+.
Past-week GAD among adults aged 16–64 in England, 2023/24.
95% confidence interval: 7.5%–9.5%.
Generalised anxiety disorder over time
Met CIS-R survey criteria for GAD in the past week
| Group / survey | Estimate | 95% confidence interval |
|---|---|---|
| 1993 | 4.4% | 3.9–4.8% |
| 2000 | 4.7% | 4.2–5.3% |
| 2007 | 4.7% | 4.2–5.3% |
| 2014 | 6.6% | 5.9–7.4% |
| 2023/24 | 8.5% | 7.5–9.5% |
The columns represent five survey waves, not annual observations. No values have been filled in for the years between them.
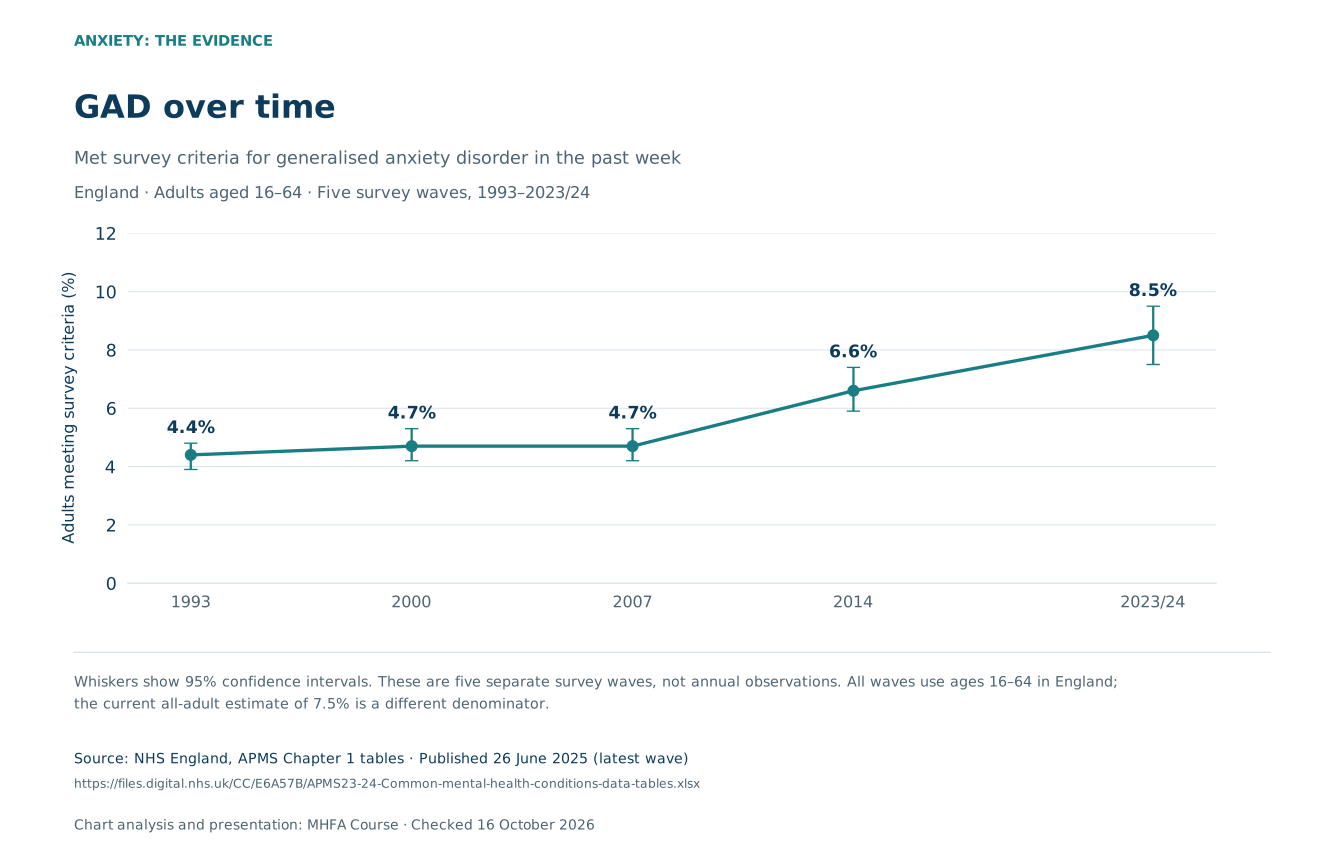
The pattern supports a long-term increase in this specific condition. It does not show how prevalence changed in every intervening year, or establish a single cause. Changes in social circumstances, reporting and survey participation may all matter when interpreting a population trend.
Anxiety across age and gender.
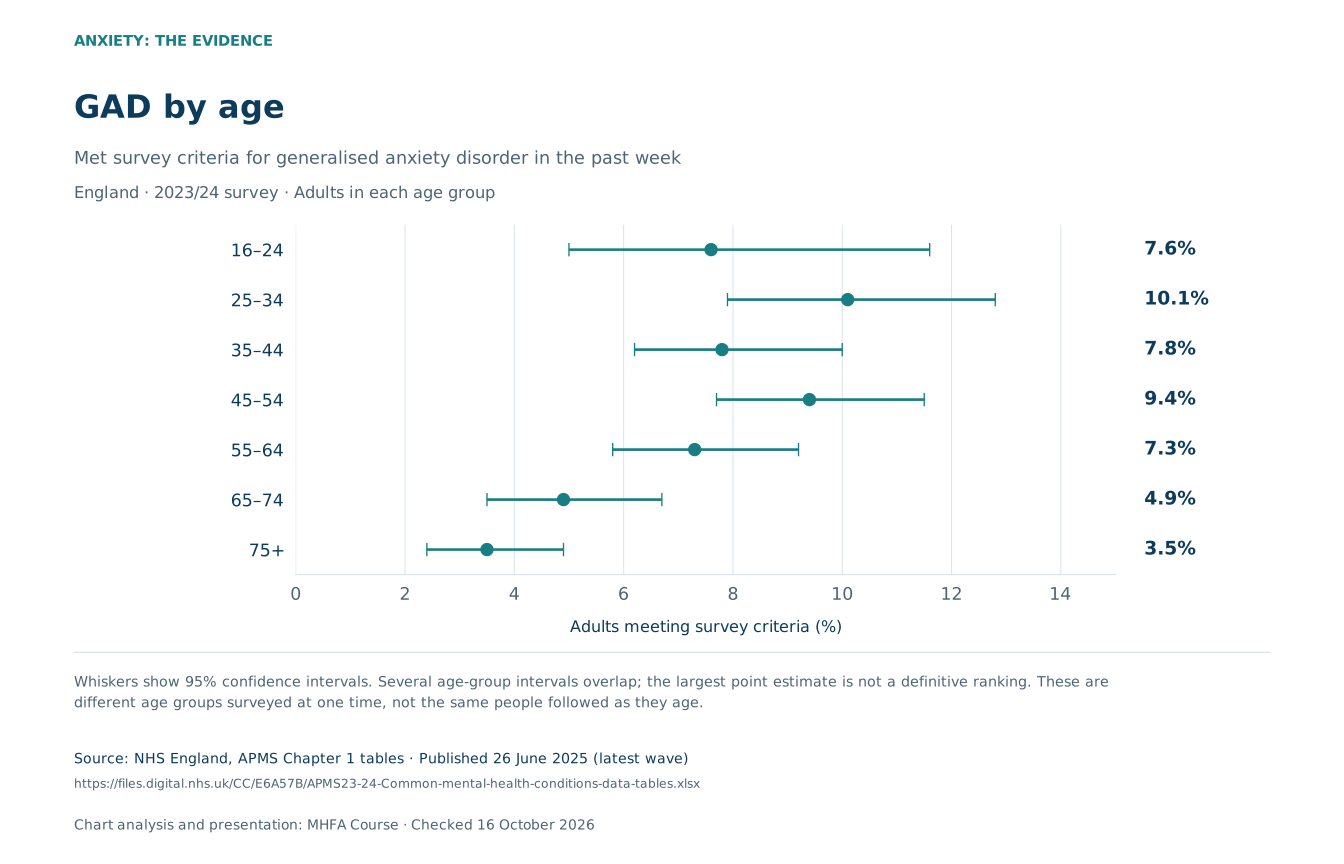
The latest survey provides a closer view of who met the criteria for GAD. These comparisons describe groups at one time; they do not follow the same individuals as they age or predict what will happen to a particular person.
GAD across age groups
Past-week prevalence · adults in each age group
Whiskers show 95% confidence intervals.
The youngest group has a smaller sample and a wider interval. Differences between point estimates are not automatically statistically significant.
GAD by gender
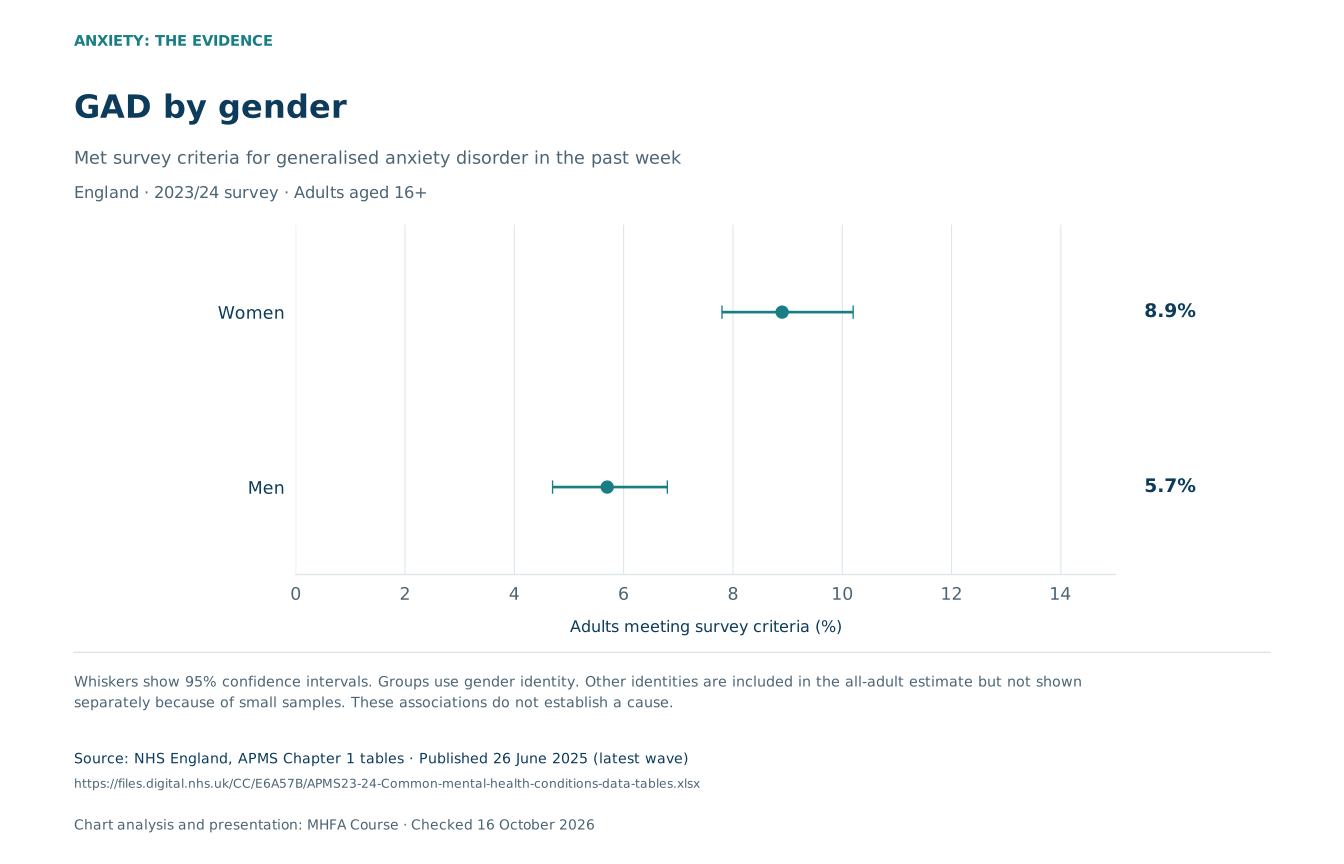
Past-week prevalence · self-reported gender identity
Whiskers show 95% confidence intervals.
What the differences mean
Women had higher GAD prevalence than men in the official analysis: 8.9% compared with 5.7%. This finding does not identify the reasons for that difference.
People with other gender identities are included in the total estimate. Separate figures are not published because their sample was too small for reliable, disclosure-safe reporting.
Adults aged 25–34 had the highest age-group point estimate, 10.1%, but several confidence intervals overlap. It would overstate the evidence to declare that group conclusively more affected than every other age group. The 3.5% estimate for people aged 75+ also concerns people living in private households; it does not describe older people in residential care.
View age and gender estimates with uncertainty
| Group / survey | Estimate | 95% confidence interval |
|---|---|---|
| 16–24 | 7.6% | 5.0–11.6% |
| 25–34 | 10.1% | 7.9–12.8% |
| 35–44 | 7.8% | 6.2–10.0% |
| 45–54 | 9.4% | 7.7–11.5% |
| 55–64 | 7.3% | 5.8–9.2% |
| 65–74 | 4.9% | 3.5–6.7% |
| 75+ | 3.5% | 2.4–4.9% |
| Women | 8.9% | 7.8–10.2% |
| Men | 5.7% | 4.7–6.8% |
What do the figures say about children and young people?
The adult GAD survey starts at age 16. The separate 2023 children’s survey in England found a probable mental disorder in 20.3% of children aged 8–16. That is a broader measure covering emotional, behavioural and other difficulties, not an anxiety-only estimate. Its different questionnaire and population mean it cannot be placed alongside adult GAD as one continuous age series.
A gradient in the estimates.
GAD and neighbourhood deprivation
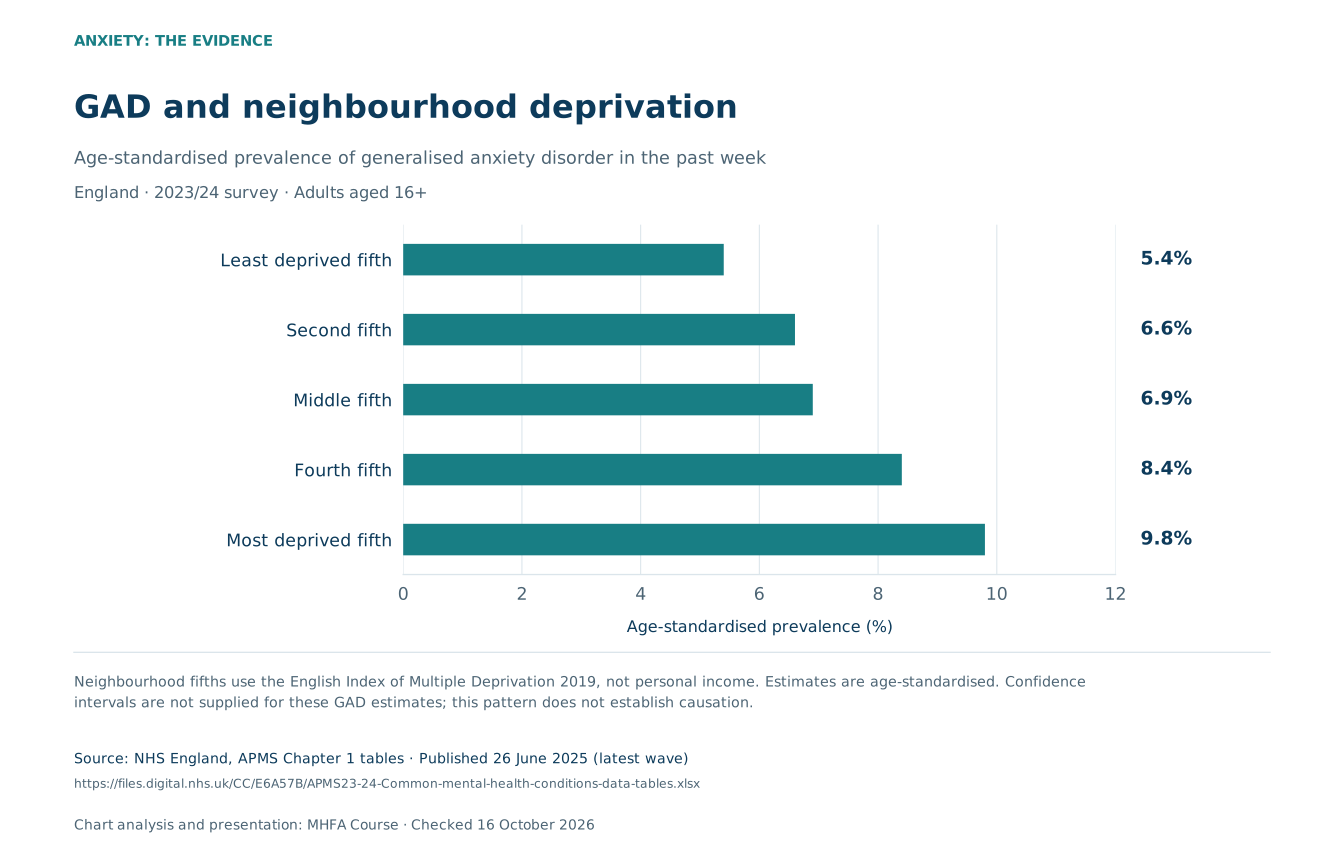
Age-standardised past-week prevalence · neighbourhood fifths
English Index of Multiple Deprivation 2019. Confidence intervals for these GAD estimates are not supplied in the published table.
A pattern across neighbourhoods
The age-standardised estimate rises from 5.4% in the least deprived fifth of neighbourhoods to 9.8% in the most deprived fifth.
Age standardisation allows for differences in the groups’ age profiles. It does not adjust for every difference between the people who live in those areas. The deprivation measure describes neighbourhoods, rather than the income of each respondent.
This is a pattern in survey estimates, not proof that living in a particular place caused someone’s anxiety. Health, financial and social circumstances can be connected in several directions. The chart is best used to understand how needs may vary across communities, without attaching a diagnosis to an address.
How anxious did people feel yesterday?
For a comparable view across all four UK countries, ONS’s Annual Population Survey asks a different question: how anxious did you feel yesterday? In January–March 2026, the UK average was 3.3 out of 10; 23.8% of adults gave a response in the high-anxiety band of 6–10.
These figures were published on 28 August 2026 and are the latest quarterly APS edition available at this guide’s check date. They represent interviews during those three months, not a measurement for the whole of 2026.
How anxious did adults feel yesterday?
Share choosing each response band on the 0–10 scale
Whiskers show 95% confidence intervals.
0 means not at all anxious; 10 means completely anxious. The bands describe reported feelings, not diagnoses.
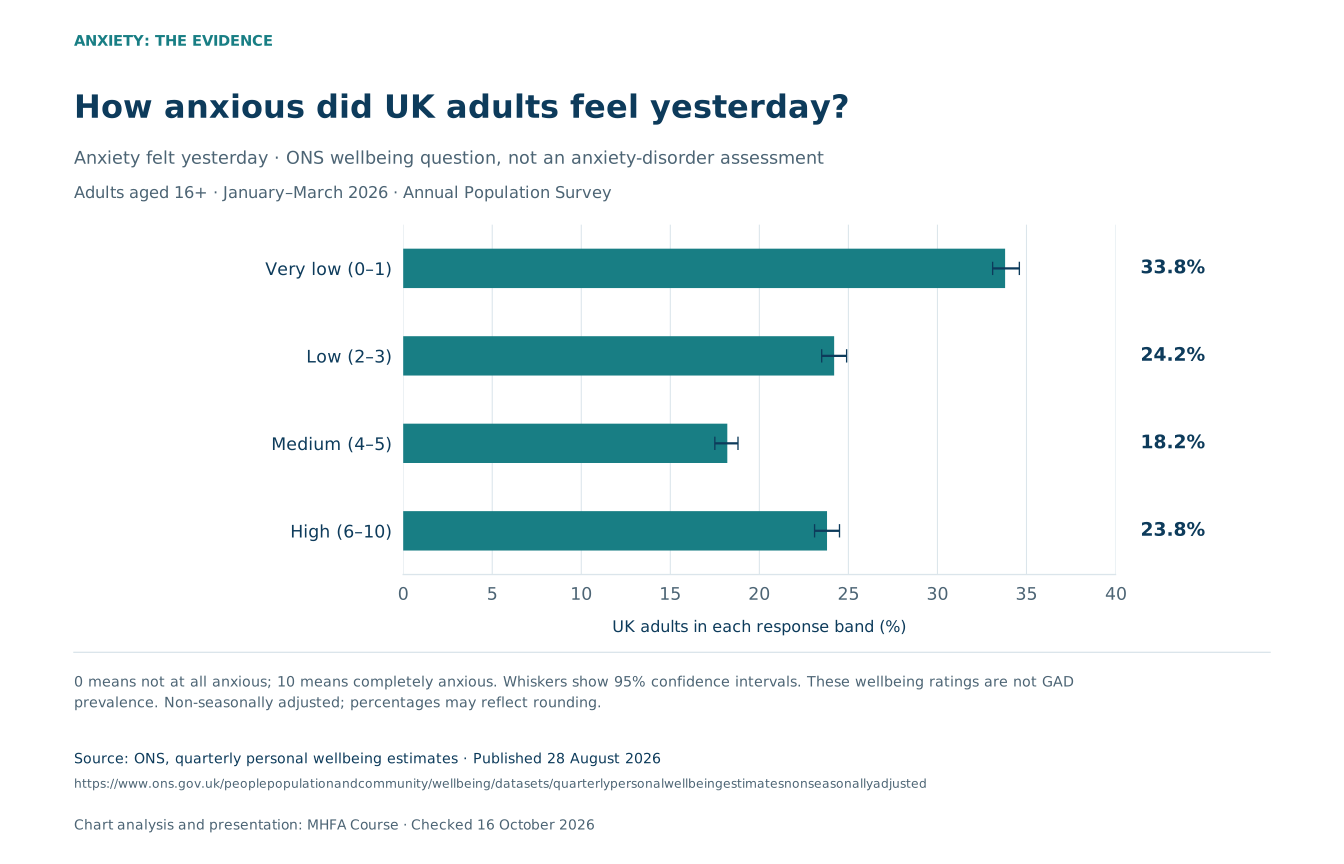
In the high-anxiety band, with a 95% confidence interval of 23.1%–24.5%.
A snapshot of everyday wellbeing
A daily rating can vary with recent events and circumstances. Someone can report a difficult day without meeting the criteria for GAD; someone receiving treatment for a disorder may report a less anxious day.
Subtracting the 7.5% APMS figure from this percentage would not reveal an “undiagnosed” population. The surveys cover different places, periods, questions and populations.
ONS’s separate Opinions and Lifestyle Survey uses another survey design. Its figures are not joined to this APS series.
Anxiety yesterday across the UK
Mean rating on a 0–10 scale · lower means less anxiety reported
Percentage rating yesterday’s anxiety 6–10 out of 10
Whiskers show 95% confidence intervals.
Countries are presented in the source’s geographical order, not ranked. The download chart shows average scores; the CSV includes both measures.
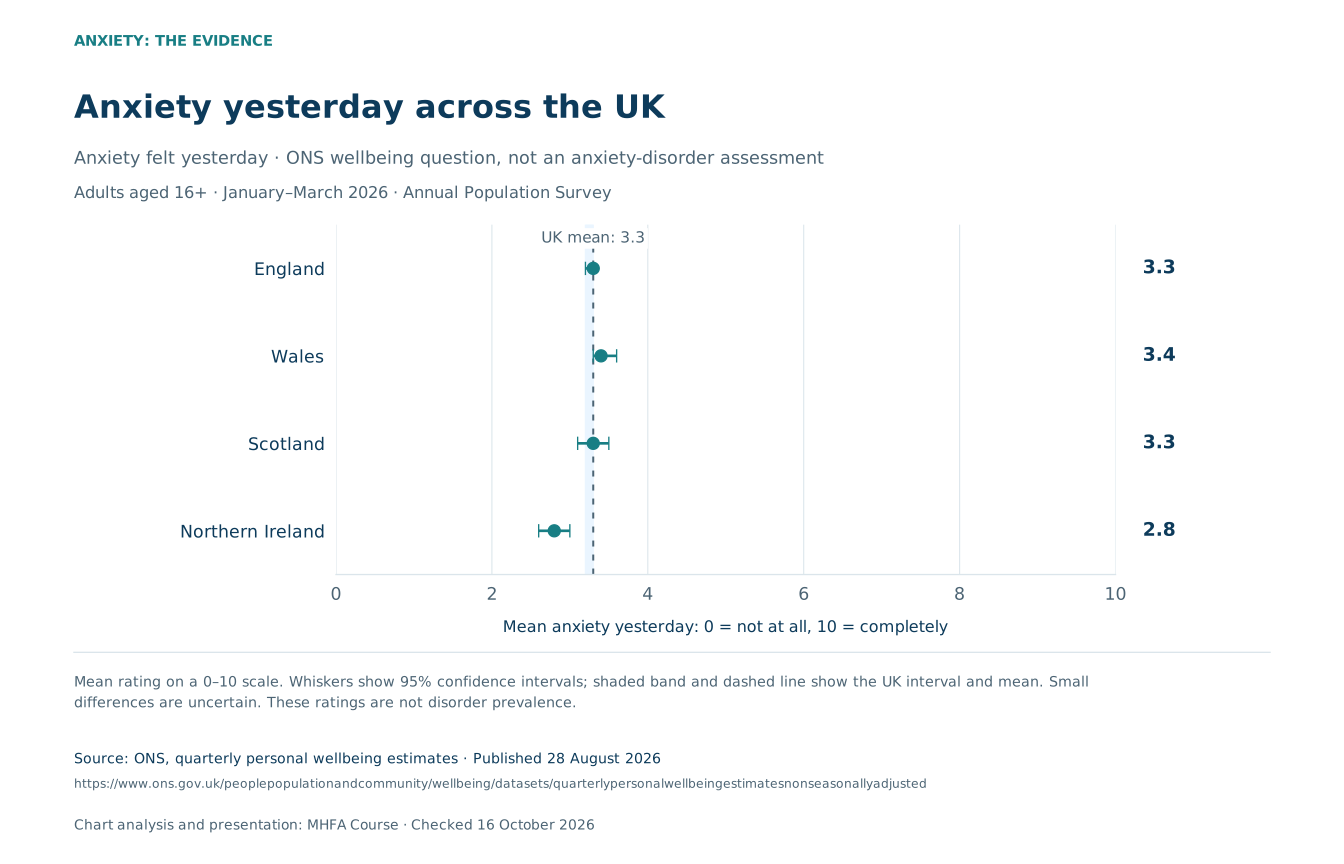
The country estimates share a survey, question and reference period. Even so, the small differences between England, Wales and Scotland should not become a league table: their intervals overlap. These are descriptive, non-seasonally adjusted estimates. Comparisons over time should use the same quarter in different years.
View country estimates, confidence intervals and sample sizes
| Country | Average (95% CI) | High anxiety (95% CI) | Sample, rounded |
|---|---|---|---|
| England | 3.3 (3.2–3.3) | 23.7% (22.9–24.5%) | 19,630 |
| Wales | 3.4 (3.3–3.6) | 26.1% (23.9–28.3%) | 2,640 |
| Scotland | 3.3 (3.1–3.5) | 25.5% (22.7–28.3%) | 1,360 |
| Northern Ireland | 2.8 (2.6–3.0) | 18.4% (15.6–21.2%) | 960 |
ONS rounds sample sizes to the nearest 10. The UK anxiety sample was 24,590. All four country mean estimates have a coefficient of variation of 5% or less; high-anxiety shares for Scotland and Northern Ireland have coefficients above 5% and up to 10%. The intervals are shown so the uncertainty stays visible.
What does access to treatment look like?
APMS found that 55.3% of adults identified with GAD reported current psychotropic medication, psychological therapy, or both. The question covered treatment for any mental or emotional problem, so it does not establish that every treatment was specifically for GAD.
This measure helps describe contact with treatment, but it cannot tell us whether an individual received the right care, enough care, or every form of support they wanted. The remaining percentage is not automatically a measure of unmet clinical need. Medication and therapy can overlap and should not be added together.
Survey treatment receipt is also different from a service outcome. NHS Talking Therapies reports activity and outcomes for referrals in England. A person can have more than one referral, and referrals received, starting treatment and completing treatment in a year are not all the same cohort.
Current medication or psychological therapy
Among adults aged 16+ identified with GAD.
Treatment could concern any mental or emotional problem. This is treatment receipt, not a recovery rate. A confidence interval was not supplied beside this estimate in the verified chapter.What do the latest NHS Talking Therapies results show?
For 2025/26, 57.4% of eligible completed referrals recorded with GAD moved below the service’s clinical symptom thresholds. The denominator is completed-treatment referrals after excluding those not at clinical caseness at the start. This is a service outcome, not the share of everyone with GAD who recovered or a measure of permanent cure.
The annual report, published on 24 September 2026, flags presenting-complaint data problems at six providers. The condition-specific outcome is therefore useful secondary context, with that quality limitation retained. It should not be used to rank treatments or disorders.
Increasing availability of talking therapies, reducing stigma around treatment-seeking, and training more Mental Health First Aiders can help bridge the treatment gap. Mental Health First Aid training equips individuals to recognise anxiety early and provide initial support, while also helping those experiencing anxiety feel less isolated.
Numbers are a starting point for support.
Recognising when to seek support
GAD can involve worry that is hard to control and affects everyday life, alongside sleep difficulties, restlessness or physical symptoms. A survey score is not a personal diagnosis. New or concerning physical symptoms should not simply be assumed to be anxiety.
A GP can assess persistent difficulties and discuss treatment. NHS options include talking therapies, commonly cognitive behavioural therapy, and medicines where appropriate. Adults aged 18+ in England can also self-refer to NHS Talking Therapies. Treatment can take time, and a GP can review care that is not helping.
Anxiety at work
HSE estimated 964,000 workers with work-related stress, depression or anxiety in Great Britain in 2024/25. This combined category cannot tell us how many workers had GAD or another anxiety disorder.
It is useful context for workplace support, while the population and wellbeing measures above explain different aspects of anxiety. None can predict an individual employee’s needs from their job title or industry.
Work-related anxiety stems from multiple sources: workload pressures, lack of control, poor line management, inadequate support, organisational changes, and conflict with colleagues. The transition to hybrid and remote working has created new anxieties around communication, isolation, and work – life boundaries. Organisations investing in mental health support through employee assistance programmes, mental health training, and workplace Mental Health First Aid courses see better outcomes for both employees and productivity.
Reading anxiety statistics with care.
How common is anxiety in the UK?
There is no single interchangeable figure. The latest APMS estimate is 7.5% for past-week GAD among adults aged 16+ in England. ONS’s UK-wide January–March 2026 survey found 23.8% rated yesterday’s anxiety in the high band. The first measures a specific condition; the second a feeling.
Is anxiety increasing?
The comparable England APMS series for ages 16–64 rose from 4.4% in 1993 to 8.5% in 2023/24, with increases after 2007. That supports a long-term rise in survey-assessed GAD. It does not establish a year-by-year trend in every anxiety condition or show a new increase during 2026.
Why do 7.5% and 8.5% both appear?
They use different age ranges within the same survey. The 7.5% figure includes everyone aged 16 and over; 8.5% covers ages 16–64 so that the latest results can be compared consistently with the earliest survey.
Does “past week” mean anxiety lasted only a week?
No. APMS assesses whether the condition was present in the week before interview, but the GAD algorithm also includes symptoms lasting at least six months. A short reference period describes prevalence at that point, not necessarily the duration of the condition.
How reliable are the estimates?
APMS interviewed 6,912 adults in its first phase. Its household response rate was 29.4%, compared with 57% in 2014. Weighting adjusts for selection and non-response, but it cannot remove every potential bias. People in many communal or institutional settings, temporary accommodation and those sleeping rough were outside its sampling frame.
The confidence intervals shown here describe sampling uncertainty. They do not include every possible measurement error or the effects of non-response. An overlap or gap should be read alongside the source’s own statistical analysis, rather than used as an automatic significance test.
The ONS charts use only its quarterly Annual Population Survey estimates. We do not join them to the separate Opinions and Lifestyle Survey, extrapolate them to a whole year, or convert them into a count of anxiety disorders. APMS’s full publication was expanded on 27 November 2025; that does not change the 2023/24 period of these findings.
Useful charts.
Context included.
Six downloadable charts include SVG and PNG versions, the underlying CSV data and notes on geography, dates and uncertainty. Keep the original source and measure with each figure when sharing it.
Mental Health First Aid Course (2026). Anxiety Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/anxiety-statistics
Mental Health First Aid for Anxiety
Mental Health First Aid (MHFA) training teaches you how to recognise signs of anxiety, have supportive conversations, and guide people toward professional help. MHFA Instructors provide evidence-based training on recognising anxiety symptoms, understanding anxiety triggers, and responding with empathy and competence. The training covers myths about anxiety, how to ask direct questions about worry and physical symptoms, how to listen without judgment, and practical steps for supporting someone seeking treatment. MHFA-trained individuals become valuable assets in workplaces, schools, communities, and families, helping reduce the stigma and isolation that often accompanies anxiety. APMS measures treatment across common mental health symptoms; it does not establish that over 70% of people with diagnosed anxiety receive no treatment.
Sources
Primary evidence and methodology. Checked 16 October 2026.
- NHS England: APMS common mental health conditions
2023/24 survey; GAD definition and results. Chapter first published 26 June 2025. - NHS England: APMS Chapter 1 data tables
Table A2: current estimates and confidence intervals; Table B2: trend; Table 1.9: deprivation. - NHS England: APMS methods
March 2023–July 2024 fieldwork; population, sample, weighting and response. - NHS England: interpreting APMS findings
Survey coverage, definitions, uncertainty and comparisons. - NHS England: assessment of disorders
Appendix A, F41.1; the GAD algorithm includes a six-month duration criterion. - NHS England: APMS treatment and service use
Chapter 2, section 2.3 and Table 2.2; current medication and/or psychological therapy. - GOV.UK: APMS Part 1 release
Confirmed first publication: 26 June 2025. - ONS: quarterly personal wellbeing, non-seasonally adjusted
January–March 2026 edition, published 28 August 2026; Annual Population Survey. - ONS: quality of quarterly personal wellbeing estimates
Confidence intervals, rounded sample sizes and coefficient-of-variation flags. - ONS: personal wellbeing quality and methodology
Anxiety-yesterday question and response bands; distinct from clinical assessment. - NHS: generalised anxiety disorder
Symptoms, clinical assessment, treatment and seeking support. - NHS England: Talking Therapies annual report 2025/26
Published 24 September 2026; presenting-complaint quality notice dated 25 September 2026. - NHS England: children and young people’s mental health, 2023
Probable mental disorder is a broader outcome than anxiety alone. - HSE: work-related stress, depression or anxiety
Great Britain, 2024/25; the category combines three conditions.