
ADHD Statistics UK: 2026 Facts, Data & Key Insights
ADHD statistics UK
A clearer view of screening, assessment referrals and prescribing—and what each can tell us.

Of adults screened positive on the six-item ASRS in APMS 2023/24.
England · adults aged 16+A positive screen is not a diagnosis.
Of adults reported ever receiving a professional ADHD diagnosis.
England · APMS 2023/24 · adults aged 16+A different question from screening.
Open MHSDS referrals included in the possible ADHD assessment proxy.
England · June 2026Not a complete list of people waiting without care.
Different figures describe different things.
ADHD is a neurodevelopmental condition involving difficulties with attention and/or hyperactivity and impulsivity that affect everyday functioning. A questionnaire result, a clinical diagnosis and an open referral each describe a different part of the picture.
An estimate of need
A model applies assumptions about prevalence to a population. It can include people who have not been diagnosed, but it is not a register of confirmed cases.
A positive screen
A screening questionnaire identifies symptoms that may warrant fuller assessment. It does not establish every requirement for an ADHD diagnosis.
A possible assessment referral
A service proxy can include referrals for other conditions or ongoing care. Being recorded in the data does not necessarily mean a person is waiting without contact.
NHS England’s August 2026 management information included an all-age modelled estimate of 2,478,000 people with ADHD in England, including 737,000 aged 5–24. It includes people without a diagnosis. The estimate is not a direct count of people on a clinical register.
The model also includes 144,000 children aged 0–4 as potential future diagnoses. That component represents potential future diagnoses, rather than confirmed diagnoses in children aged 0–4.
NHS England has announced that the modelled prevalence and community-paediatrics proxy measures will be removed from this publication from November 2026. They remain part of the August release reviewed here.
The figures should not be placed in a single funnel or subtracted to estimate an “undiagnosed gap”. They use different populations, periods and definitions. Their strengths become clearer when each is used for the question it can answer.
Positive screens have become more common.
In APMS 2023/24, 13.9% of adults aged 16 and over in England screened positive on the Adult ADHD Self-Report Scale (ASRS). The comparable published figures were 8.2% in 2007 and 9.7% in 2014.
The six-item questionnaire asks about symptoms over the previous six months. The chart follows the published face-to-face screening series, not a trend in confirmed clinical diagnoses.
Positive ADHD screens over time
How has the share of adults meeting the ASRS screening threshold changed?
| Group / measure | % | 95% interval |
|---|---|---|
| 2007 | 8.2% | 7.6–8.9% |
| 2014 | 9.7% | 8.9–10.6% |
| 2023/24 | 13.9% | 12.8–15.2% |
Positive screens are not confirmed diagnoses. Whiskers show published 95% confidence intervals. The same six-item face-to-face measure is used in each survey wave.
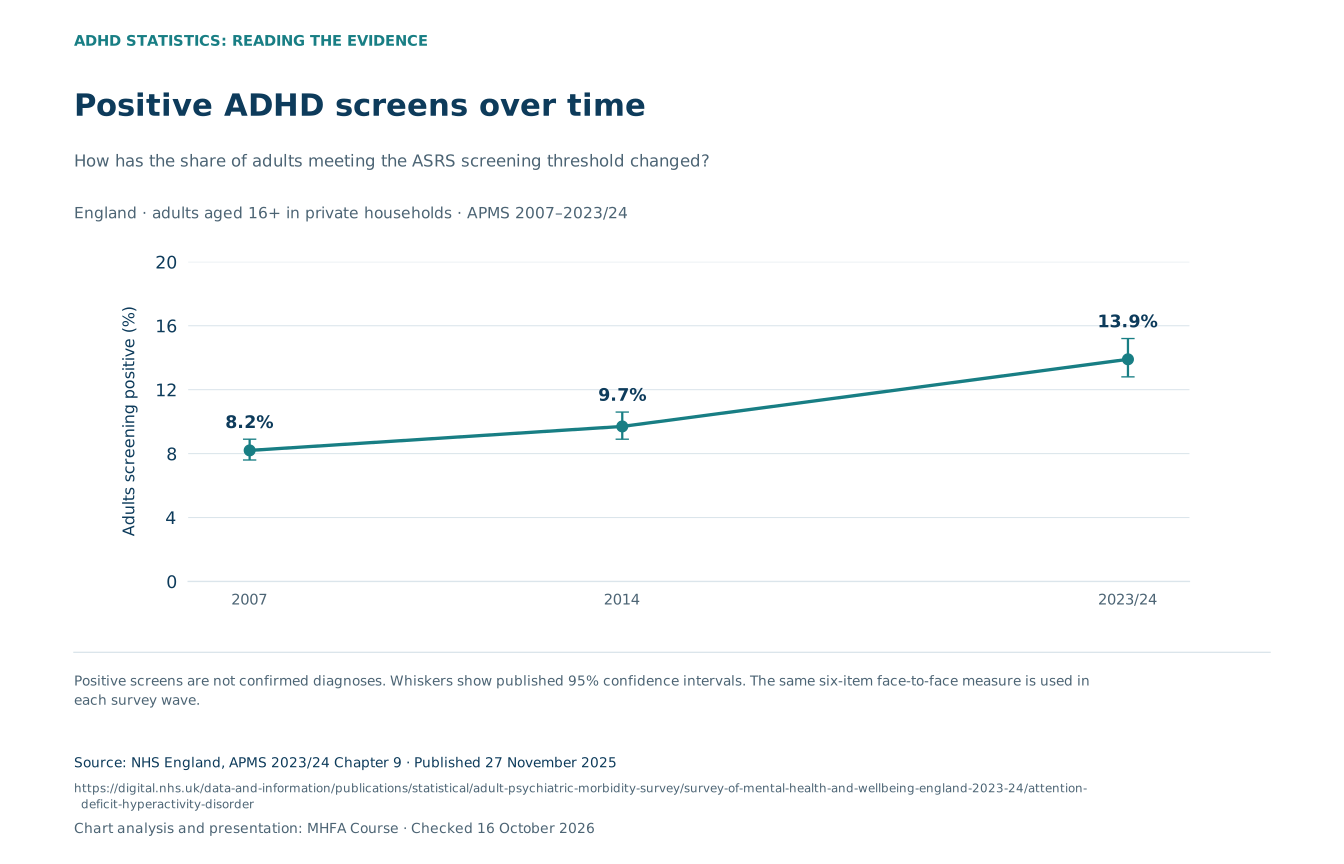
The confidence intervals show sampling uncertainty. The survey covers adults living in private households; it does not represent everyone in institutions or without a private-household address. Participation, recall and how questions are understood can also affect results.
Why the headline and trend confidence limits differ slightly
The published current-table confidence interval for the 13.9% headline is 12.8%–15.1%. The trend table gives 12.8%–15.2% for the same displayed estimate. This guide retains the interval supplied for each table rather than substituting one for the other.
The source does not establish a reason for the small difference in the overall interval. The chart and download use the trend table’s endpoints.
Screening is a starting point, not the diagnosis
The ASRS does not assess every diagnostic requirement, including childhood onset, impairment and symptoms across settings. APMS cautions that actual ADHD prevalence is likely to be considerably lower than the positive-screen rate.
Changes in responses can reflect more than one influence. The survey alone cannot establish how much underlying prevalence, awareness or recognition has changed, or explain why a particular person has difficulties.
Age patterns and reported diagnosis.
The positive-screen rate was 25.0% among adults aged 16–24 in APMS 2023/24. The age comparison helps describe how responses vary across the survey population.
These are age-group screening results. They should not be described as the proportion in each group with a confirmed ADHD diagnosis or used to predict the outcome of an individual assessment.
Positive ADHD screens by age
What proportion within each adult age group screened positive?
| Group / measure | % | 95% interval |
|---|---|---|
| 16–24 | 25% | 20.4–30.2% |
| 25–34 | 17.6% | 14.5–21.2% |
| 35–44 | 16.5% | 14.3–19% |
| 45–54 | 13.7% | 11.4–16.4% |
| 55–64 | 12.7% | 10.8–14.9% |
| 65–74 | 4.3% | 3.2–5.8% |
| 75+ | 3.7% | 2.5–5.5% |
Percentages are within each age group, not each group’s share of all positive screens. Whiskers show published 95% confidence intervals. Screening does not confirm ADHD.
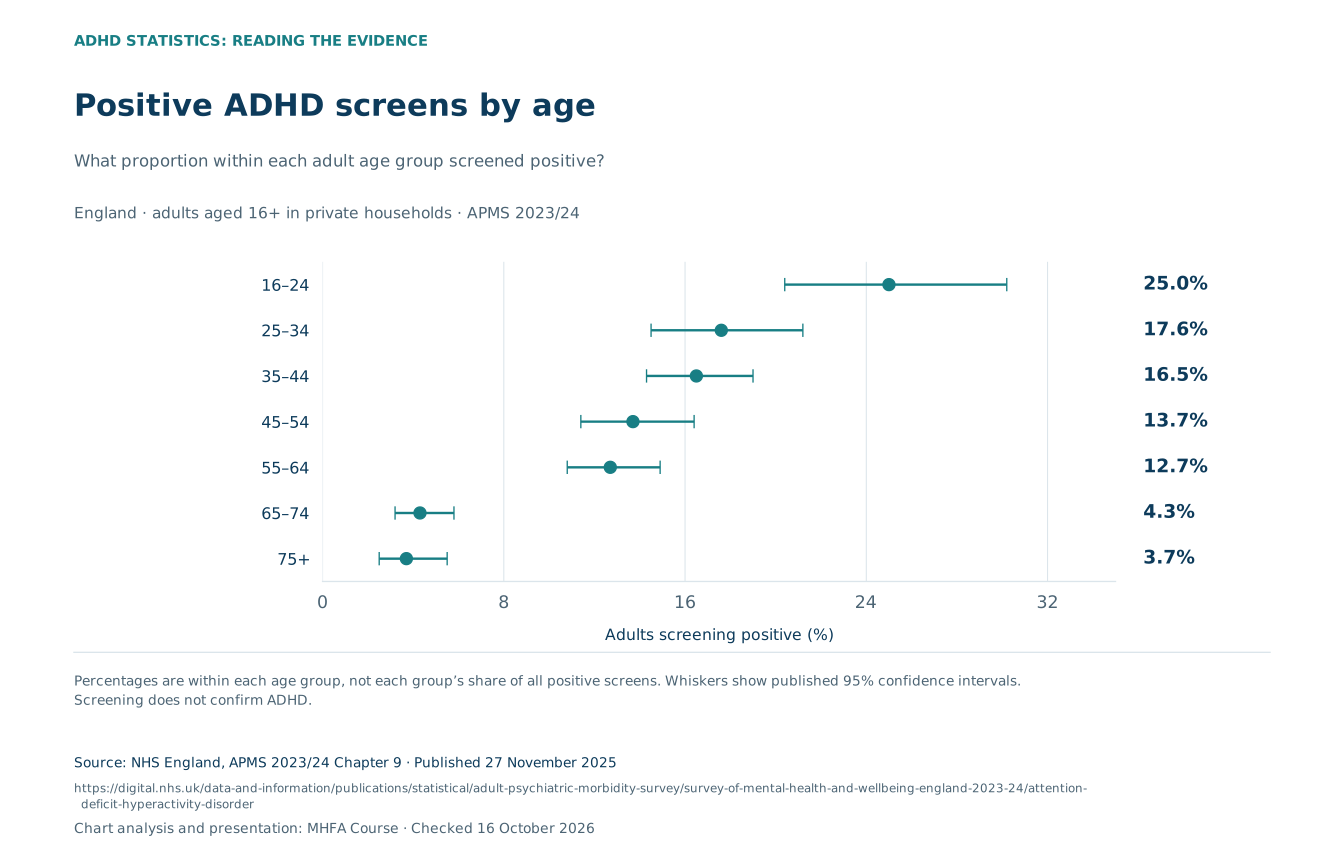
The current survey estimates were 14.9% for women and 12.4% for men. These describe the source’s current gender groups. The overall trend is kept separate from any attempted long-term comparison of historical sex categories with current gender categories.
Screening positive and reporting a diagnosis are different
In APMS 2023/24, 1.8% of adults reported ever receiving a professional ADHD diagnosis. Among adults who screened positive on the ASRS, 9.6% reported a diagnosis.
Because a positive screen is not equivalent to having ADHD, this does not mean that only one in nine people who actually have ADHD are diagnosed. Subtracting the screening percentage from a diagnosis percentage, or combining a GP-record sample with a separate population model, would not establish a reliable “undiagnosed gap”.
Recognition has developed over time, including awareness that ADHD can be missed in girls and women. That context is different from measuring a change in prevalence. People may seek an assessment when attention, organisation or impulsivity affects their everyday life, regardless of their demographic group.
A GP or appropriate specialist can discuss the next steps and support while someone is waiting for assessment.
Open referrals, duration and recorded contact.
NHS England recorded 780,430 open MHSDS referrals in its possible ADHD assessment proxy for June 2026. These are referral records within the dataset’s definition, not necessarily different people with a confirmed need for an ADHD diagnosis.
The proxy is designed to provide management information where a complete national diagnostic waiting-list measure is not available. It can include other conditions, ongoing care and incomplete submissions. Those limitations are part of the figure, rather than an optional footnote.
How long possible referrals had been open
How were the open MHSDS referral records distributed across duration bands?
| Group / measure | open referrals |
|---|---|
| Up to 13 weeks | 93,965 |
| 13–52 weeks | 234,980 |
| 52–104 weeks | 192,090 |
| 104 weeks or more | 259,395 |
Rounded referral counts, not necessarily unique people. Duration is time the referral has been open, not necessarily time without contact or care. The proxy can include other conditions and ongoing care.
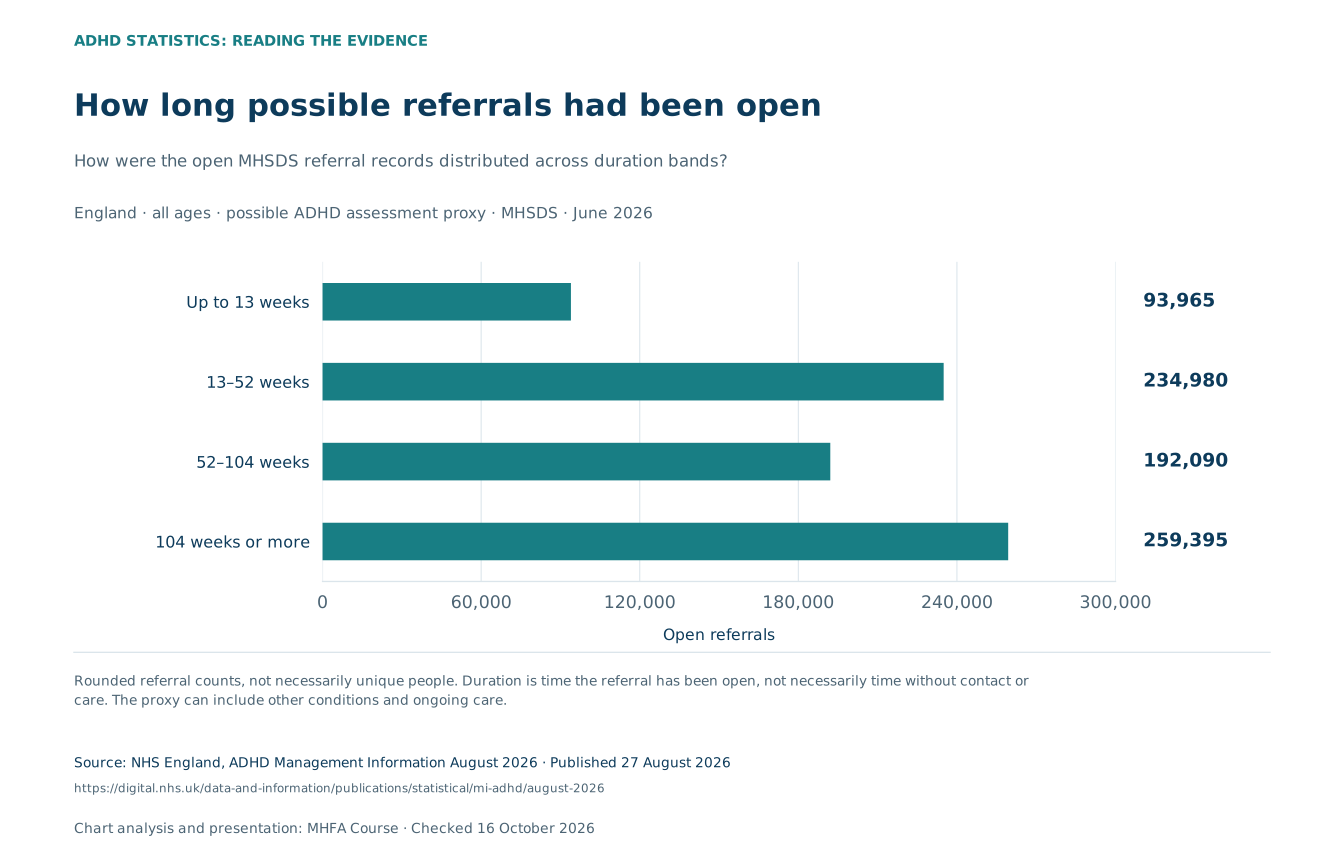
The published bands were 93,965 referrals open for up to 13 weeks, 234,980 for 13–52 weeks, 192,090 for 52–104 weeks and 259,395 for at least 104 weeks. Together, the two longest bands comprised 451,485 referrals open for at least 52 weeks.
These are durations of open referrals, not necessarily periods without an appointment, support or treatment. A long-running referral may include ongoing care, which is why duration and recorded contact are shown separately.
How long a referral has been open is not the same as time without contact
A recorded contact helps distinguish stages within the open-referral proxy. It does not establish that a diagnostic assessment has been completed or that all the person’s needs have been met.
Likewise, no recorded contact within this measure does not prove there has been no support through any other service. The definition and scope of the dataset remain important.
Open referrals and recorded contact
How many records had a first contact recorded within the measure?
| Group / measure | open referrals |
|---|---|
| No first contact recorded | 560,930 |
| First contact recorded | 219,500 |
Rounded counts of open referrals. A recorded contact is not a completed diagnosis; no recorded first contact does not prove there was no support elsewhere. These are not confirmed diagnostic waiting-list counts.
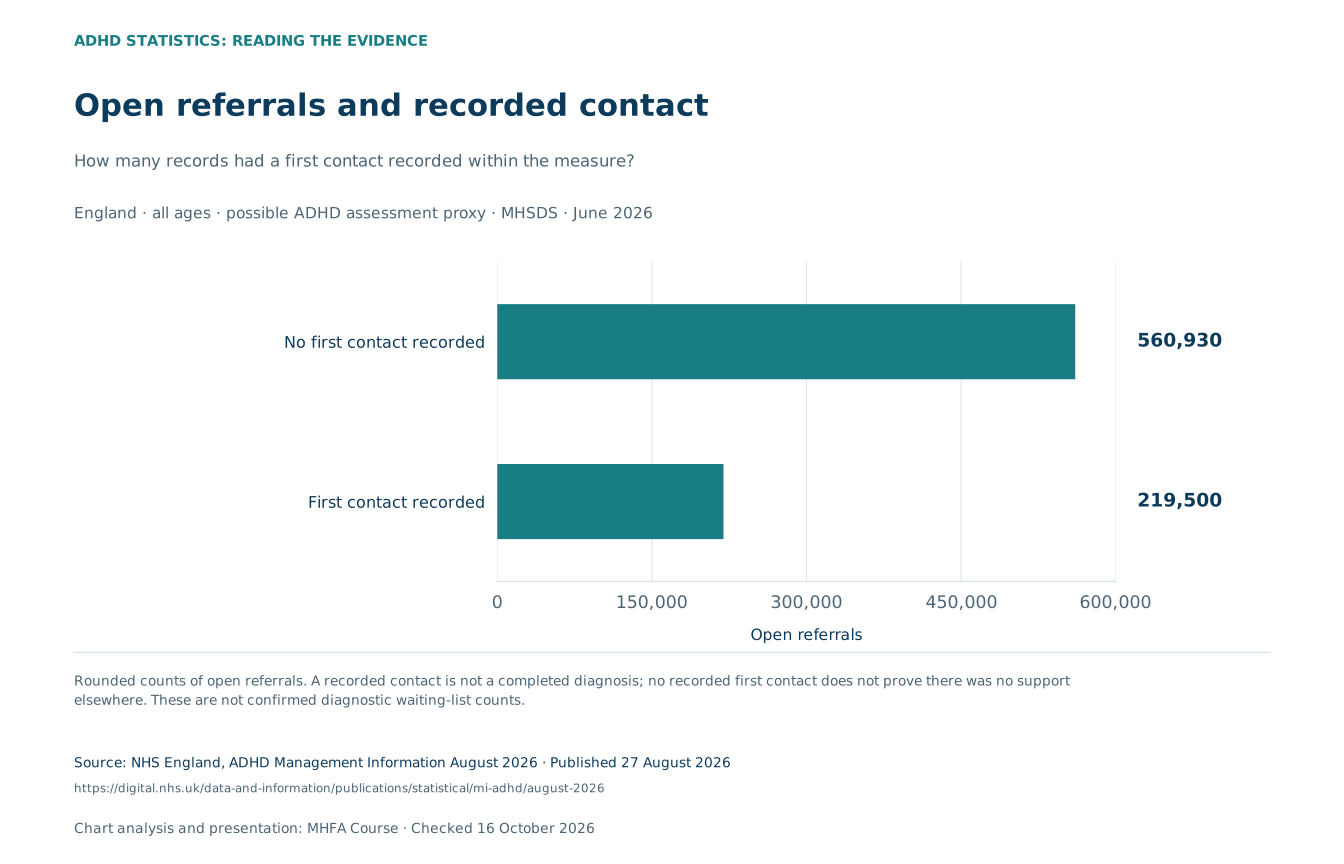
A recorded contact does not establish diagnosis or successful treatment, and an absent contact record does not prove that no support was received.
The wider total, age breakdown and new referrals
The release’s wider headline was up to 959,662 open referrals that may have been for ADHD assessment: the 780,430 MHSDS referrals plus up to 179,232 in community health waiting-list data. The component datasets have different coverage and limitations and cannot be deduplicated. The combined figure is not 959,662 unique people.
The MHSDS age breakdown contained rounded counts of 572,570 referrals for adults aged 18+ and 207,835 for children aged 0–17, calculated from the published age groups. A further 25 had unknown age.
Mental health services received up to 37,105 new possible ADHD assessment referrals in June 2026, reported as 46.7% more than in June 2025. These are recorded referrals, not a measure of change in underlying ADHD prevalence.
NHS England warns that submissions from February 2025 onwards are not directly comparable with earlier months because new independent-provider submissions increased recorded open referrals. Changes in coverage and reporting also matter when interpreting later movements.
Neither a referral total nor a duration band predicts how long an individual will wait for a diagnosis. Services can differ in their pathways, recording and coverage. A person’s clinical assessment, support needs and local arrangements matter alongside the national picture.
ADHD screening and mental health.
After age-standardisation, APMS found that 38.5% of adults with a common mental health condition screened positive for ADHD, compared with 7.2% of those without one.
This is an association between survey measures. Age-standardisation accounts for differences in the groups’ age profiles, but it does not make the groups alike in every other respect or establish which difficulties came first.
Screening and common mental health conditions
How do positive-screen rates differ between the two survey groups?
| Group / measure | % |
|---|---|
| With a common mental health condition | 38.5% |
| Without a common mental health condition | 7.2% |
The percentage screening positive for ADHD is calculated within each mental-health group. These are age-standardised associations, not causal effects. No confidence intervals were supplied for this comparison.
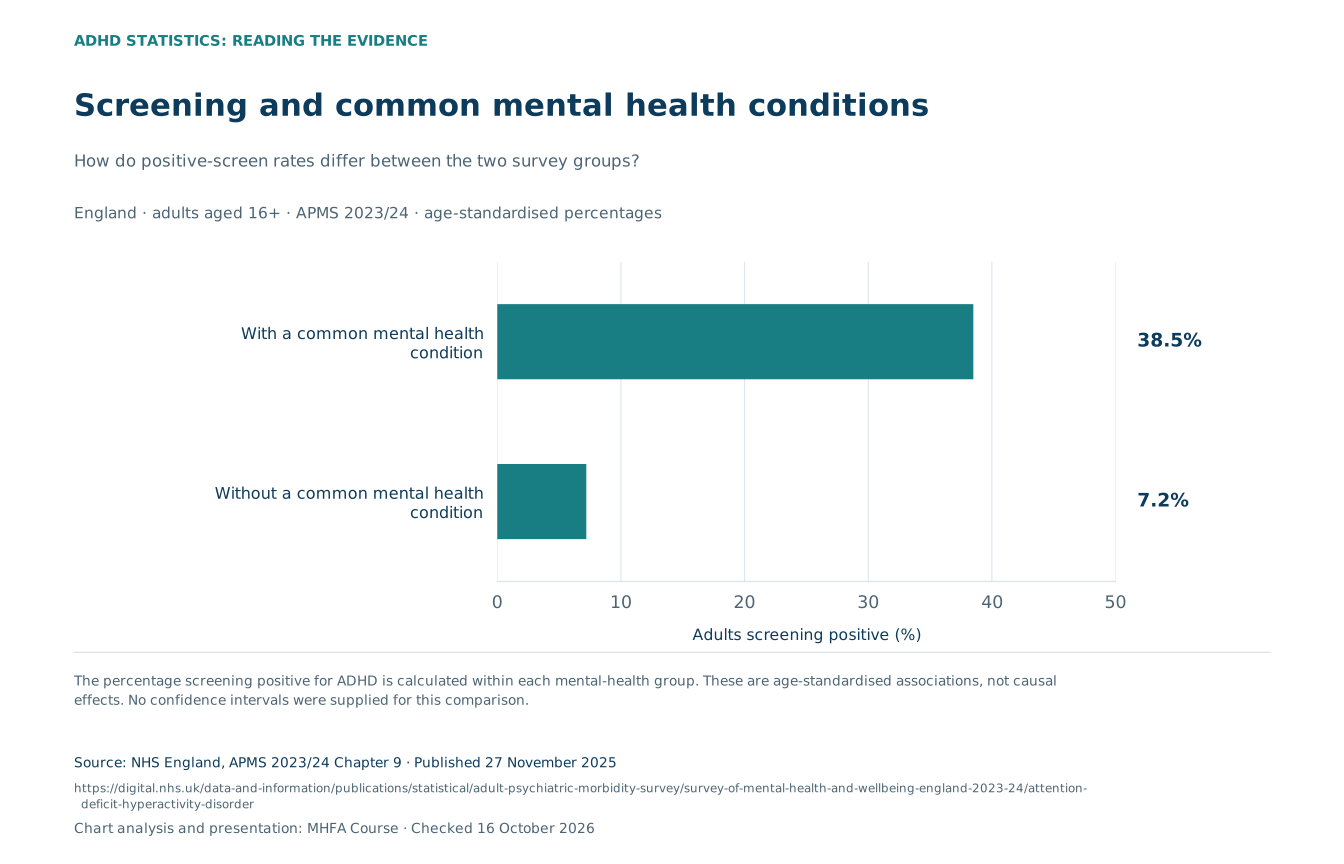
These adjusted percentages should not be compared as if they were raw counts or a diagnostic prevalence ratio. The source table does not provide confidence intervals for this comparison.
ADHD can coexist with depression or anxiety, and other conditions can share some symptoms. Assessment should consider the person’s wider circumstances rather than assuming that one questionnaire explains every difficulty.
Support at work or in education should reflect individual needs and preferences. These datasets do not establish a national rate for employer disclosure, the benefits of diagnosis or ADHD among all young people outside education and employment. Practical adjustments and clinical support should be considered individually.
What the prescribing figures capture.
NHSBSA reports on the prescribing group “CNS stimulants and drugs used for ADHD”. It includes medicines that can have other indications, so the identified-patient count is not a register of people diagnosed with ADHD.
The annual figures concern prescriptions issued in England and subsequently dispensed in the community. The chart keeps the measure consistent across financial years.
Identified patients in the prescribing group
How has the annual patient count changed for this defined group of medicines?
| Group / measure | identified patients |
|---|---|
| 2020/21 | 162,838 |
| 2021/22 | 192,105 |
| 2022/23 | 233,474 |
| 2023/24 | 277,640 |
| 2024/25 | 326,450 |
| 2025/26 | 426,504 |
BNF 4.4: CNS stimulants and drugs used for ADHD, including other indications. These are not confirmed ADHD diagnoses. Patient identification improved from 88.7% to 92.4% of items across the series, affecting the trend.
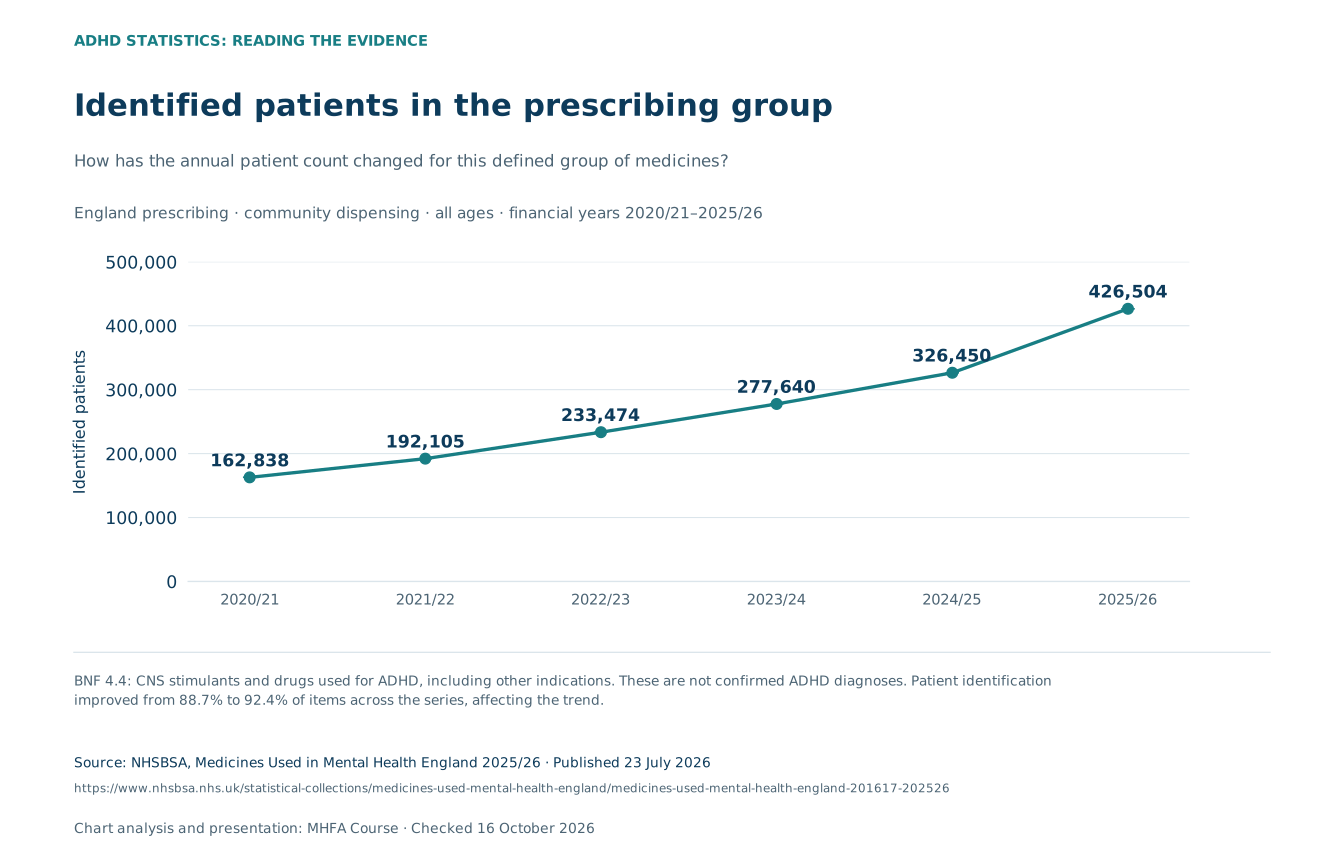
The share of prescription items linked to an identified patient rose from 88.7% in 2020/21 to 92.4% in 2025/26. Improved identification therefore affects the trend, alongside changes in prescribing.
Adults, children and the limits of the prescribing count
In 2025/26, NHSBSA recorded around 267,000 adult patients and 158,000 child patients in this prescribing group. The exact published counts were 266,853 and 158,394. These are people identified within the publication’s community-dispensing scope, not everyone with ADHD or everyone receiving care.
Age is measured at 30 September in the financial year. The source warns against adding patient breakdowns to reconstruct the overall unique-patient total.
Private prescribing and prescriptions issued and dispensed in hospitals or prisons are excluded. A medicine can be used for another condition, and patient identification depends on the records available.
Why the newer quarter is shown separately
The April–June 2026 quarterly release, published on 10 September 2026, reported around 395,000 identified patients and 1.3 million prescription items in this group.
A quarter covers a shorter period than the annual chart. Its unique-patient total cannot be directly compared with a full-year count, added across quarters or multiplied by four to estimate annual patients.
Prescribing is one aspect of care. A patient count does not show how well treatment worked, whether someone also received other support, or how many people have ADHD in the population. People can receive more than one prescription item.
These records also cannot establish a UK-wide cost of untreated ADHD. Estimates of healthcare spending, employment effects or wider economic costs need their own methods and definitions.
Making sense of the different numbers.
How many people have ADHD in the UK?
The modelled estimate discussed here concerns England, not the whole UK. It should not be treated as a count of confirmed diagnoses. Scotland, Wales and Northern Ireland have separate data systems, and the England datasets do not provide a combined UK total.
Does a positive ASRS screen mean someone has ADHD?
No. The screening questionnaire identifies symptoms that may warrant fuller assessment. It does not establish every diagnostic requirement, including childhood onset, impairment and symptoms across settings.
Does the rise in positive screens prove ADHD has become more common?
It shows a rise in positive responses to the survey’s screening measure. It does not by itself establish the reason for that rise or quantify a change in underlying clinical prevalence.
Are all open referrals people waiting for an ADHD diagnosis?
No. The figures are a possible-assessment proxy with limitations. They count referrals, can include other conditions or ongoing care, and do not provide a complete count of people waiting without contact.
Why are some of the latest figures from June 2026 or 2023/24?
Different publications have different schedules and reference periods. The August 2026 management-information release describes June service data; the APMS chapter published in 2025 describes survey fieldwork in 2023–24. The review date does not change those periods.
Do prescribing figures show how many people are diagnosed?
No. The drug group includes medicines with other uses, and the publication covers a defined prescribing and community-dispensing scope. Diagnosis, prescribing, clinical benefit and other forms of support are separate measures.
Methods, uncertainty and reuse
This guide is an original visual presentation of published evidence, not a new survey or an estimate of undiagnosed ADHD. The datasets remain separate: modelled prevalence, household screening, reported professional diagnosis, referral proxies and prescribing.
Published confidence intervals are shown where supplied. No intervals are invented for the adjusted comparison or administrative records. Missing intervals do not mean perfect certainty. Survey participation, question interpretation, coding and provider coverage all affect interpretation.
Charts start at zero. The data tables and CSVs retain source values, periods, bases and locators; compact chart labels may round for readability. Descriptive associations do not establish causes or predict an individual’s assessment or treatment.
ADHD charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the measure, population and period with each figure. Screening, assessment activity and prescribing should retain their separate labels.
Mental Health First Aid Course (2026). ADHD Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/adhd-statistics
Sources
Primary evidence and methodology. Checked 16 October 2026.
- NHS England: APMS ADHD chapter
- NHS England: APMS ADHD source tables
- NHS England: ADHD Management Information, August 2026
- NHS England: ADHD MI supporting information and limitations
- NHS England: August 2026 summary tables
- NHS England: August 2026 machine-readable data
- NHS England: ADHD MI data dictionary, version 1.3
- NHSBSA: Medicines Used in Mental Health, 2016/17–2025/26
- NHSBSA: CNS stimulants and drugs used for ADHD, annual source tables
- NHSBSA: CNS stimulants and drugs used for ADHD, annual narrative
- NHSBSA: background and methodology
- NHSBSA: April–June 2026 quarterly release
- NHS: ADHD in adults
- NICE NG87: ADHD diagnosis and management