
ACEs Statistics UK: 2026 Facts, Data & Key Insights
Adverse childhood experiences statistics UK
What research says about childhood adversity, adult wellbeing and support—and why an ACE count cannot predict a person’s future.

Reported at least one of four types of abuse before age 18.
England & Wales · adults aged 18+Year ending March 2024
Reported at least one of the eleven experiences in the Welsh survey.
Wales · adults aged 18–692017 survey · historical estimate
Reported four or more of those eleven experiences.
Wales · adults aged 18–692017 survey · not a clinical threshold
Childhood adversity is broader than a single score.
Adverse childhood experiences are potentially traumatic experiences before the age of 18. Research links childhood adversity with later health and social outcomes, but an ACE count does not determine an individual’s future.
ACEs research developed from studies of childhood adversity and adult health, including the original US ACE study. Different studies include different experiences, age ranges and questions. Their results should not automatically be treated as interchangeable prevalence estimates.
This guide keeps those definitions visible. Retrospective adult surveys describe what respondents report about their own childhoods. They are not a current census of children experiencing adversity or a record of every event.
ACE surveys
Researchers ask about specified experiences before adulthood. The number and wording of questions vary, so two ACE scores may not measure the same things.
Childhood abuse
A survey of abuse can add important evidence without covering every adversity in a household ACE questionnaire. Its prevalence is not the prevalence of all ACEs.
Current wellbeing
Adult feelings or health may be associated with earlier adversity. That is different from showing that one event caused a condition or predicting an individual’s future.
Which experiences can count as ACEs?
Common frameworks include physical, emotional and sexual abuse; physical or emotional neglect; and harmful household experiences. Household questions may cover domestic violence, substance-use problems, mental illness, parental separation or a household member’s imprisonment.
A particular study may use only some of those questions. The Welsh studies below measured nine experiences in 2015 and eleven in 2017. Their results need to be read with those definitions, rather than assumed to measure a fixed universal list.
Other frameworks include bullying, community violence, discrimination and further adversities. These experiences can matter even when they are absent from a particular questionnaire.
Poverty is a wider social condition that can shape exposure and access to support. It is not evidence that a family is necessarily abusive or neglectful.
How common are the experiences each survey measures?
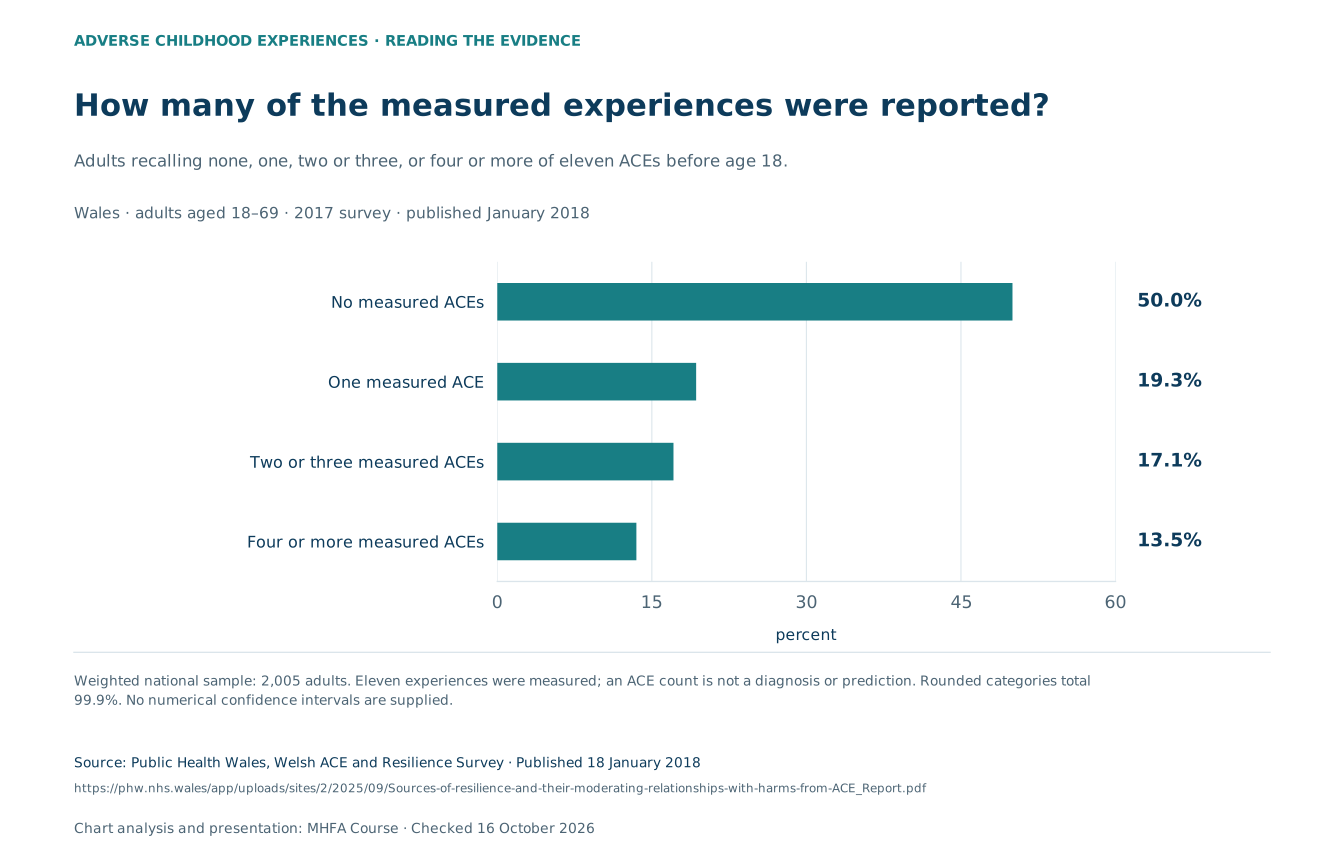
In the 2017 Welsh survey, 50.0% of adults reported at least one of the eleven measured adverse childhood experiences. 13.5% reported four or more.
The prevalence estimates represent the national sample of 2,005 adults aged 18–69. The wider study recruited additional respondents from areas with higher levels of Welsh spoken language, but the full recruited sample should not be substituted for the national prevalence denominator.
The distribution below describes reported childhood experiences in that adult sample. It is not an estimate for every part of the UK, nor a statement about the current childhoods of people born since the survey.
How many of the measured experiences were reported?
Adults recalling none, one, two or three, or four or more of eleven ACEs before age 18.
| Group / measure | percent |
|---|---|
| No measured ACEs | 50% |
| One measured ACE | 19.3% |
| Two or three measured ACEs | 17.1% |
| Four or more measured ACEs | 13.5% |
Weighted national sample: 2,005 adults. Eleven experiences were measured; an ACE count is not a diagnosis or prediction. Rounded categories total 99.9%. No numerical confidence intervals are supplied.
The original 2015 Welsh findings: 47% and 14%
The first Welsh ACE study found that 47% of adults reported at least one of its nine measured ACE categories, and 14% reported four or more. These are the historical findings often quoted in summaries of ACE research.
The 2017 survey used eleven measured experiences. Its 50.0% and 13.5% results should not be interpreted as a simple increase or decrease from the earlier study without accounting for the changed questions and samples.
Neither Welsh survey establishes prevalence in England, Scotland or Northern Ireland. A result close to half also does not establish that a majority of all UK adults have experienced ACEs.
Why “four or more” is not a diagnostic threshold
Grouping respondents with four or more measured ACEs helps researchers compare patterns. It is not a clinical cut-off, a safe-versus-unsafe boundary or a prediction that someone will develop illness.
A count does not capture the nature, timing, duration or context of an experience. It also does not describe all the protective relationships, resources and strengths in a person’s life.
Someone with a low count may have experienced serious harm, while someone with a higher count may have strong support and good wellbeing. Individual assessment cannot be replaced by a population category.
Why there is no UK country ranking here
Separate surveys exist for Scotland and Northern Ireland, but their questionnaires, age coverage and periods differ. They are not combined here into a UK prevalence estimate or a country ranking.
Scotland’s published 2019 survey used some different wording and response thresholds from the Welsh research. The Northern Ireland report published in February 2025 used a broader questionnaire that included experiences such as bullying and community violence. Its publication year should not be read as a verified survey fieldwork year.
A higher percentage from a broader questionnaire does not by itself show that one country has more adversity. Differences in what is asked need to be understood before comparing estimates.
What is included in the questions?
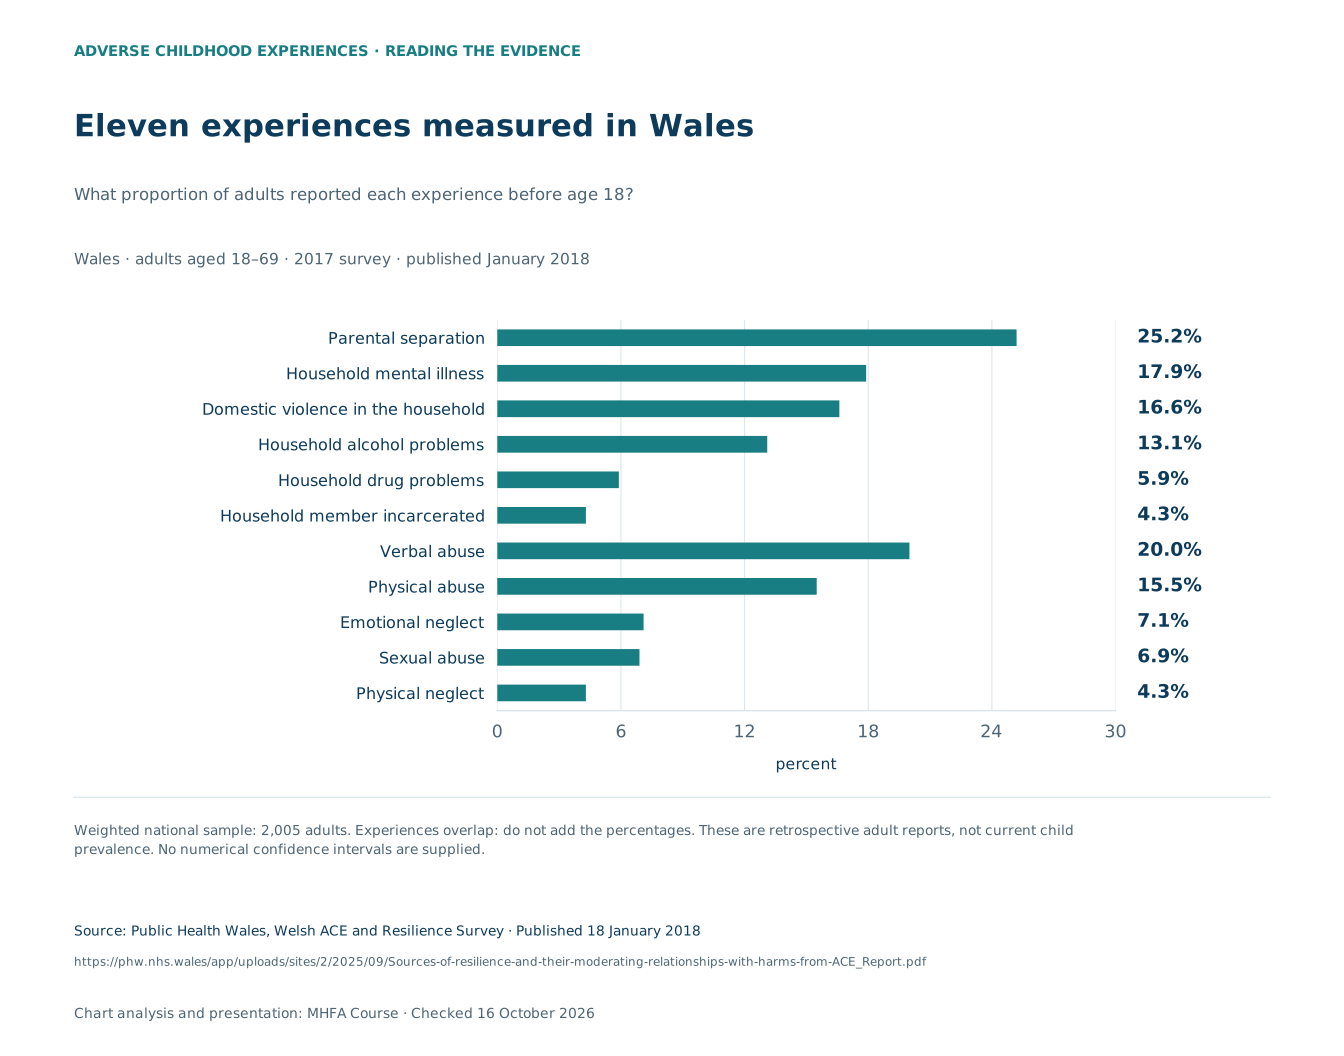
The prevalence of a count depends on what is counted. The Welsh chart shows the eleven experiences included in the 2017 survey; a respondent could report several.
These categories bring together different aspects of childhood. Their frequency does not rank how serious an individual experience was, and an experience absent from the list can still matter for a person’s wellbeing or support needs.
Eleven experiences measured in Wales
What proportion of adults reported each experience before age 18?
| Group / measure | percent |
|---|---|
| Parental separation | 25.2% |
| Household mental illness | 17.9% |
| Domestic violence in the household | 16.6% |
| Household alcohol problems | 13.1% |
| Household drug problems | 5.9% |
| Household member incarcerated | 4.3% |
| Verbal abuse | 20% |
| Physical abuse | 15.5% |
| Emotional neglect | 7.1% |
| Sexual abuse | 6.9% |
| Physical neglect | 4.3% |
Weighted national sample: 2,005 adults. Experiences overlap: do not add the percentages. These are retrospective adult reports, not current child prevalence. No numerical confidence intervals are supplied.
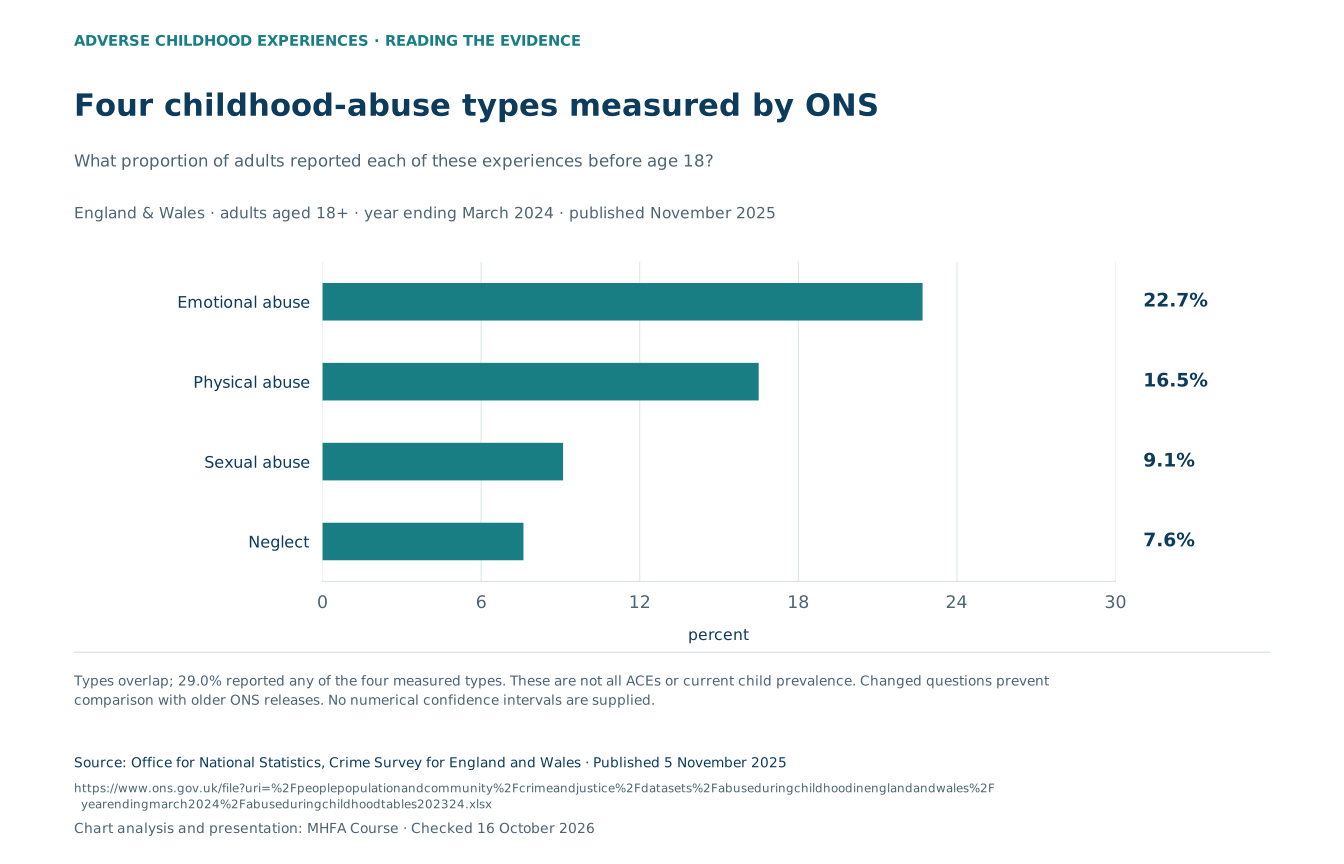
ONS’s newer survey provides a different perspective. 29.0% of adults aged 18 and over in England and Wales reported at least one of four measured types of abuse before age 18 in the survey for the year ending March 2024.
The four type percentages below overlap. They are not the prevalence of all ACEs and cannot be added to replace the overall 29.0% estimate.
Four childhood-abuse types measured by ONS
What proportion of adults reported each of these experiences before age 18?
| Group / measure | percent |
|---|---|
| Emotional abuse | 22.7% |
| Physical abuse | 16.5% |
| Sexual abuse | 9.1% |
| Neglect | 7.6% |
| Any of the four measured abuse types | 29% |
Types overlap; 29.0% reported any of the four measured types. These are not all ACEs or current child prevalence. Changed questions prevent comparison with older ONS releases. No numerical confidence intervals are supplied.
Overlapping experiences are not separate people.
The same respondent may report more than one experience. Adding category percentages would count some people more than once and would not produce the share with any adversity.
Wording, age coverage and response methods also matter. A newer abuse survey is useful evidence in its own right, but does not become an update to a different historical ACE questionnaire simply because both concern childhood.
How earlier experiences relate to adult wellbeing.
ONS compared wellbeing reported at interview among adults who reported any of the four measured childhood-abuse types and those who reported none. The comparison describes an association across groups.
For example, 8.4% of adults reporting childhood abuse had low life satisfaction, compared with 4.0% of those reporting none. Each percentage uses its own group as the denominator.
The charts use low scores of 0–4 out of 10 for life satisfaction, feeling that life is worthwhile and happiness. These are wellbeing measures, not diagnoses. The findings do not show that childhood abuse was the sole cause of a respondent’s score.
Childhood abuse and current adult wellbeing
How often were low wellbeing scores reported within each group?
| Group / measure | percent |
|---|---|
| Low life satisfaction — Any measured childhood abuse | 8.4% |
| Low life satisfaction — No measured childhood abuse | 4% |
| Low sense of worthwhile activities — Any measured childhood abuse | 6.2% |
| Low sense of worthwhile activities — No measured childhood abuse | 2.9% |
| Low happiness — Any measured childhood abuse | 9.4% |
| Low happiness — No measured childhood abuse | 4.3% |
Low means 0–4 out of 10 on each measure. Questions were asked of a quarter of the CSEW sample; bases differ. These are unadjusted associations, not diagnoses or causal effects. No numerical confidence intervals are supplied.
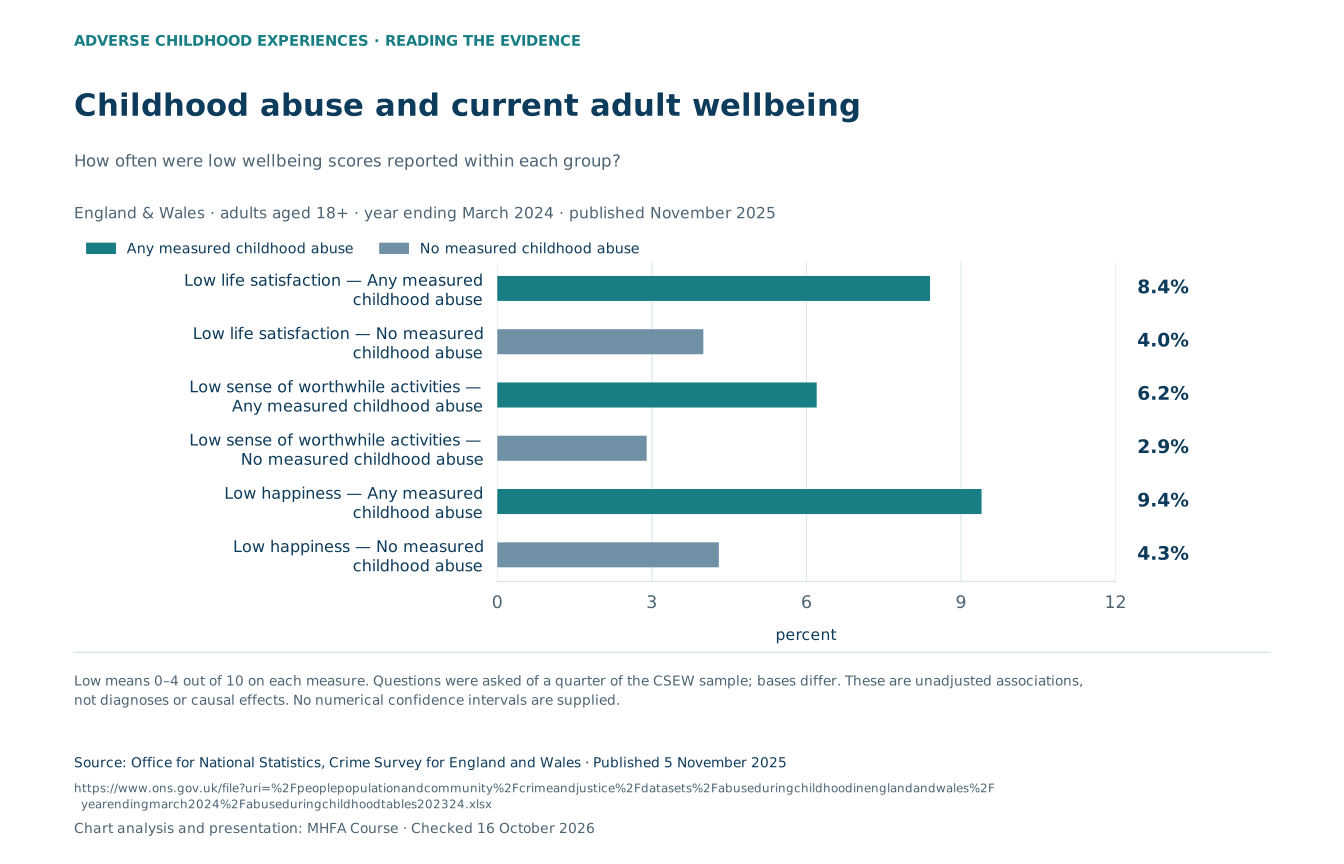
The wellbeing questions were asked of a quarter of the Crime Survey sample, and valid-answer bases differ by question. These findings should not be turned into an individual prediction or a claim that every person who experienced abuse will have low wellbeing.
No numerical confidence intervals are supplied for this comparison. The chart describes the published estimates without inventing precision or making a statistical-significance claim.
Mental-health conditions, screening and individual experience
Public Health Wales describes associations between ACE exposure and mental wellbeing, health-harming behaviours and some physical conditions. Depression and anxiety may be associated with childhood adversity, but an adjusted statistical model does not remove every possible influence or prove causation.
Childhood trauma can be relevant to PTSD. However, ACE exposure and PTSD are not interchangeable. APMS 2023/24 found that 5.7% of adults in England screened positive for PTSD. This is not an ACE-specific rate, a confirmed diagnosis or proof of the cause of symptoms.
Our PTSD statistics guide and suicide statistics guide explain the separate screening and mortality measures.
Self-harm and perinatal support should remain individual
Self-harm can occur in different circumstances and have different functions. A history of adversity may be relevant, but it is not appropriate to assume that everyone who self-harms had the same childhood experience or lacks coping skills. NICE recommends exploring the person’s reasons and needs.
A parent’s history of adversity may also be relevant to perinatal mental health and support. It should not be framed as an inevitable transmission of trauma to their child. Compassionate support can build on existing strengths and relationships without blame.
See our self-harm statistics guide for the distinct definitions and evidence.
Support matters alongside the statistics.
Protective relationships and access to support can help reduce the effects of adversity. The evidence should make room for those strengths alongside the experiences people report.
Support can address immediate safety and wider conditions, including housing, income security, relationships and access to care. It should not assume that every person with a similar ACE count needs the same intervention.
Living in a deprived area can be associated with a greater likelihood of multiple adversities. That does not mean low-income families lack supportive relationships, or that adversity occurs only in poverty.
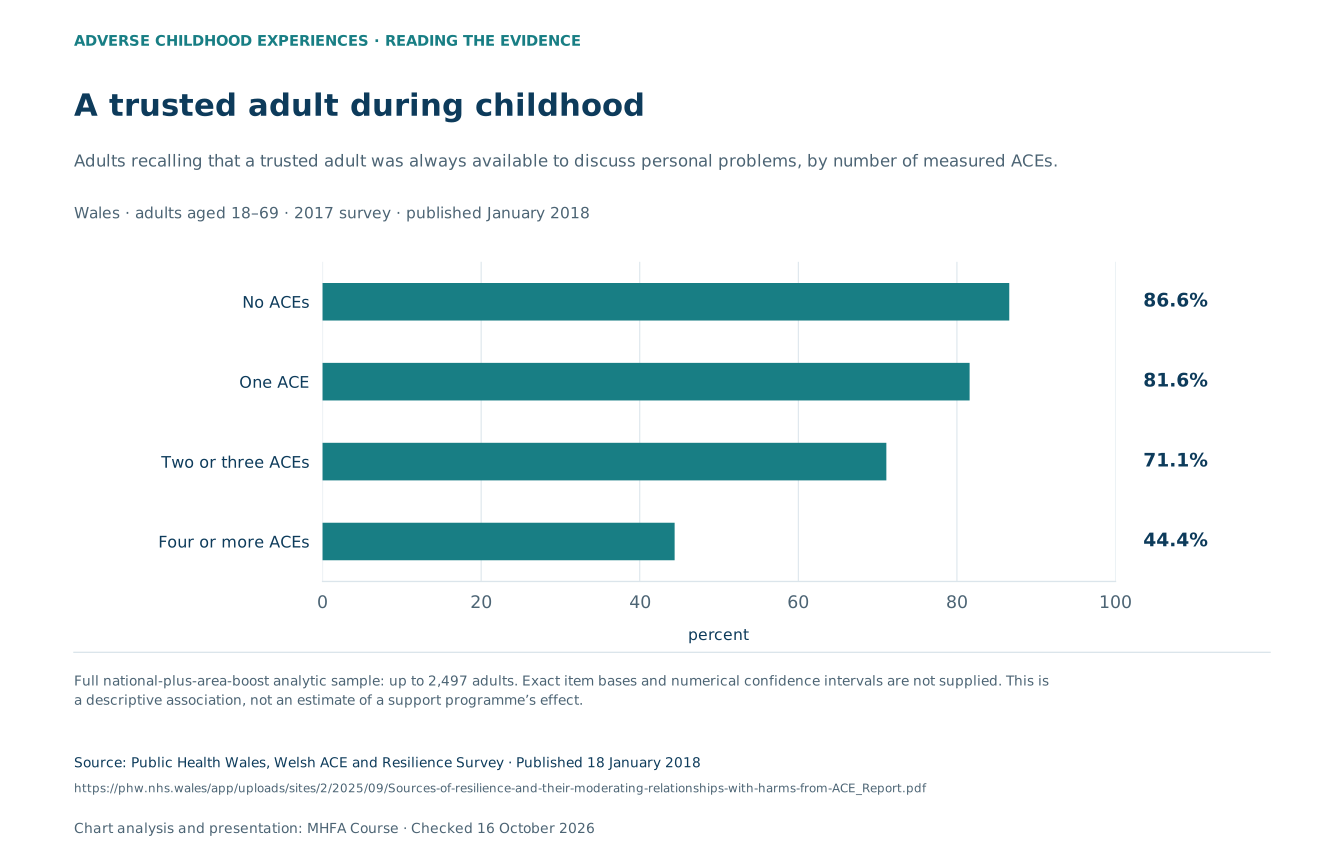
The Welsh survey also asked whether a trusted adult had always been available during childhood. The comparison below shows how that reported relationship differed across ACE-count groups. It describes an association; it does not measure the effect of a support programme.
Here, a trusted adult means someone aged 18 or over whom the respondent could trust and talk to about personal problems. The chart shows only the answer “Always”.
A trusted adult during childhood
Adults recalling that a trusted adult was always available to discuss personal problems, by number of measured ACEs.
| Group / measure | percent |
|---|---|
| No ACEs | 86.6% |
| One ACE | 81.6% |
| Two or three ACEs | 71.1% |
| Four or more ACEs | 44.4% |
Full national-plus-area-boost analytic sample: up to 2,497 adults. Exact item bases and numerical confidence intervals are not supplied. This is a descriptive association, not an estimate of a support programme’s effect.
Why this relationship chart uses a different sample
The relationship analysis includes the national sample and additional respondents from areas with higher levels of Welsh spoken language, with up to 2,497 participants. It is not the same national-prevalence base of 2,005 used in the earlier Welsh charts.
Exact valid-answer bases and numerical confidence intervals are not supplied for these plotted group estimates. They should not be used to calculate a treatment effect, an individual prognosis or the outcome of providing a particular service.
Poverty is a wider condition, not an ACE diagnosis
DWP estimated that 27% of UK children lived in relative low income after housing costs in 2024/25. This means income below 60% of the contemporary median after housing costs. It is not a measure of abuse or ACE exposure.
In England’s 2023 child mental-health survey, 26.8% of children aged 8–16 with a probable mental disorder had a parent who said they could not afford activities outside school, compared with 10.3% of those unlikely to have a disorder.
That is a separate affordability association, not proof that an inability to pay caused a mental-health condition or that a low-income family is unsafe. Relationships, material circumstances and access to services all deserve consideration without blame.
Start with the person, not an ACE score.
Trauma-informed practice recognises that adversity may influence how someone feels or responds to services. It emphasises safety, trust, choice and collaboration.
A respectful approach seeks to avoid distressing or retraumatising interactions. It asks what the person needs and what strengths and relationships they can draw on, without requiring them to recount traumatic experiences or complete an ACE score.
This approach complements appropriate professional assessment, safeguarding and treatment. It does not establish a diagnosis or replace specialist care when that is needed.
Offer choice and clarity.
Explain what will happen and why. Give people space to decide what they want to share, rather than assuming disclosure is necessary for every supportive conversation.
Keep support individual.
Consider current circumstances, safety, needs and existing resources. A numerical score cannot tell a practitioner everything that matters about a person’s life.
Claims of a particular saving or guaranteed outcome require evaluation of the intervention itself. Different programmes, settings and people cannot be assumed to have the same results.
Our Mental Health First Aid courses incorporate trauma-informed principles, helping practitioners across settings to respond to distress with understanding rather than judgment.
Reading ACE statistics without overinterpreting them.
How common are ACEs in the UK?
These sources do not provide a single combined UK estimate. The 2017 Welsh survey found 50.0% of adults aged 18–69 reported at least one of its eleven measured ACEs. The newer ONS estimate of 29.0% covers four types of childhood abuse among adults 18+ in England and Wales. Those are different measures.
Is the 47% figure out of date?
It is a historical finding from the first Welsh study, which measured nine ACE categories. It remains valid in that context, but should not be presented as a new 2026 estimate or a prevalence figure for every UK country.
Does having four or more ACEs mean someone will develop mental illness?
No. It is a research grouping, not a diagnosis or prediction. A person’s circumstances, experiences, strengths and support cannot be captured by a count alone.
Can the percentages for different experiences be added?
No. The same person can report more than one experience. Adding the percentages would count some respondents more than once.
Does poverty mean that a child has experienced abuse?
No. Poverty is a wider social condition, and an income statistic is not a measure of abuse. It must not be used to label a family as abusive or neglectful.
Should trauma-informed support require an ACE score?
A supportive approach should consider the person’s needs and allow choice about disclosure. It should not require someone to recount traumatic experiences or rely on a numerical score instead of appropriate assessment and support.
Methods, uncertainty and reuse
This guide presents published evidence visually; it is not a new survey. Each chart retains the source’s geography, ages, experiences and reporting period. A survey asking adults about childhood is different from measuring current adversity among children.
Retrospective recall, response patterns and survey coverage can affect estimates. Associations do not establish that one childhood experience caused a particular adult outcome. Study-specific relative risks need the outcome and comparison group attached.
Where confidence intervals are available, they are shown or retained in the data. Missing intervals are not invented. All axes begin at zero, and overlapping experiences are not added.
The download includes source locations and method notes. Keep that context with a chart, especially when sources measure different lists of adversities.
Childhood adversity charts.
With the context to use them.
Download SVG and PNG charts, the underlying CSV data and methodology. Keep the population, measured experiences, period and limitations with every figure.
Mental Health First Aid Course (2026). Adverse Childhood Experiences Statistics UK. Evidence checked 16 October 2026. https://www.mentalhealthfirstaidcourse.co.uk/blog/aces-statistics-uk
Sources
Primary evidence and methodology. Checked 16 October 2026.
- Public Health Wales: Welsh ACE and Resilience Survey, published 2018
- Public Health Wales: full 2017 Welsh survey report
- ONS: Abuse during childhood in England and Wales, year ending March 2024
- ONS: Childhood-abuse data tables, released 5 November 2025
- Public Health Wales: definitions and historical 2015 Welsh findings
- Public Health Wales: ACEs and mental wellbeing, 2016
- Public Health Wales: evidence and options for action, 2023
- DWP: Household income statistics, 2024/25
- NHS England: Child mental health survey, 2023
- NHS England: APMS PTSD chapter, 2023/24
- NICE: Individual assessment after self-harm, NG 225
- OHID: Working definition of trauma-informed practice
- Home Office: Trauma-informed practice learning report, 2024
- Public Health Wales: Adverse childhood experiences and engagement with healthcare services
- Scottish Government: ACEs research
- Scottish Health Survey content review: ACE measurement comparability
- Queen’s University Belfast: The prevalence and impact of adverse childhood experiences in Northern Ireland
- Northern Ireland Department of Justice: Landmark study of childhood trauma